View Point Vol. 5 No. 1 (2021): International J Health Systems and Implementation Research
Neonatal Tetanus among Nomadic Populations in India: An Insight into Socio-political Roadblocks and Pitfalls in Healthcare
Downloads
Topics
Keywords:
- Neonatal Tetnus
- Health Care Seeking Behaviour
- Social Determnants
- Health Care Access
Abstract
India achieved elimination status in 2015. Immunization coverage still continues to be low among its nomadic populations and there is a large lacuna in data related to them. Death of a nomadic due to neonatal tetanus in South India in December 2018, was investigated to examine the five major inter-linked pathways which could lead to the neonatal tetanus case in this community. Social determinants of health forms a major factor influencing health seeking behavior as well as health care access. When seen in the light of Maslow’s hierarchy of needs, the lack of basic facilities, social isolation and economic vulnerability makes it impossible to focus on progress to a higher state of well-being. Filling the gaps in the health of indigenous populations will be central to the achievement of global initiatives like Universal Health Coverage and Health for All.
Full text
This web version was prepared from the published PDF, which is the version of record. Please cite and quote from the PDF.
Introduction
Tetanus was identified as a disease of global public health importance in the 1980s when its elimination was put forth as an important goal in the 42nd World Health Assembly in 1989 and the World Summit for Children in 1990 [1,2]. At the time, tetanus was the cause of 6.7 neonatal deaths out of 1000 live births worldwide [1,2]. Subsequently, sustained efforts were taken up by countries around the world with a focus on maternal and neonatal immunization, and an elimination target of less than one case of neonatal tetanus per 1000 live births in every district or similar administrative unit in every country per year [3]. As of December 2020, only 12 countries are yet to achieve the elimination status [3]. India achieved the same in 2015 [2].
The Neglected Group
The term indigenous population is conventionally used vaguely to describe the large groups of people across the world with a wide range of social, cultural and political characteristics, making a common definition difficult [4]. Lancet, in a series of articles on the health of these populations, drew up a panel of criteria as a common point of identification including, among others – historical continuity, distinct culture and strong links to natural resources [5]. Immunization coverage continues to be lower among indigenous populations in first world countries as well as in India, proving to be potential hidden pockets for various vaccine preventable diseases including tetanus [6,7]. Yet, the population remains largely hidden from the mainstream and there is a large lacuna in data related to them.
Indian Scenario
Similar to the many indigenous groups worldwide is the nomadic population of India, which stood at an estimated one million in 1982 [8]. They continue to be a neglected population with limited access to education, mainstream opportunities and healthcare due to various factors [4]. Of these, the social determinants encompassing a wide range of inter-linked factors such as social and economic status, education and literacy, social support networks, social capital, cultural practices, and the level of access to health services form the cornerstone of neonatal deaths in these communities.
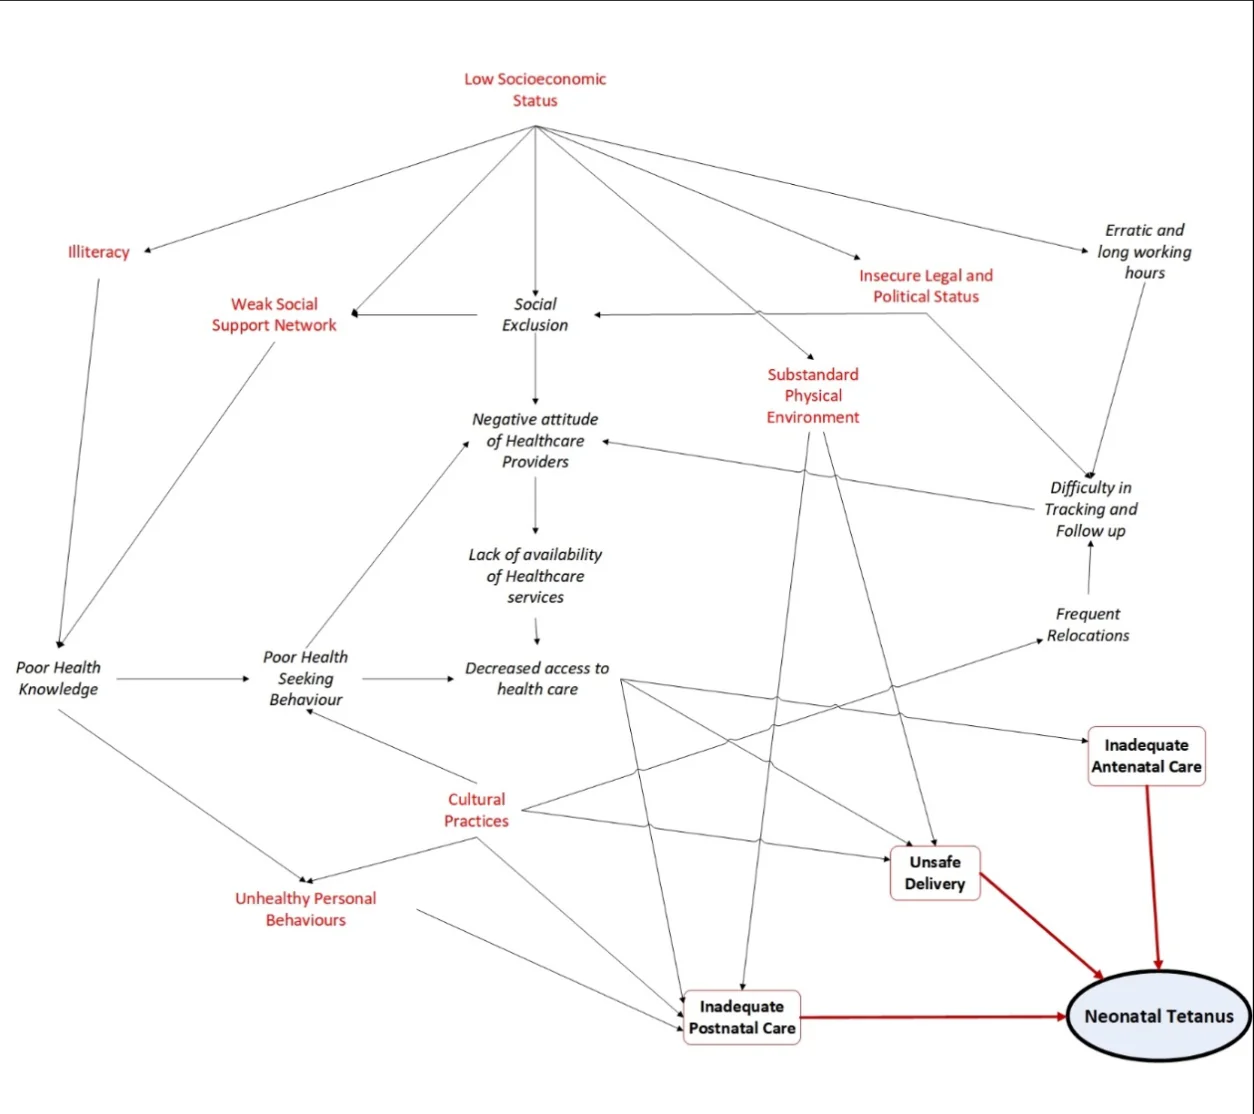
A neonatal tetanus (NT) death case was reported in a tertiary care hospital of Puducherry, South India in December 2018. The baby hailed from a nomadic community of rural Tamil Nadu, a neighboring state. The baby was delivered at home and subjected to traditional norms surrounding childbirth including withholding of breastfeed and poor umbilical cord hygiene. There were multiple delays in seeking healthcare as well. The detailed clinical aspects of the case are described elsewhere [9]. An investigation was undertaken and we found failures at multiple levels which contributed to the occurrence of tetanus. These include poor healthcare access, inadequate antenatal and post-natal care, exposure to unhygienic environments and living conditions, difficulty in tracking of the community, and a lack of ownership from the healthcare system. In this perspective, we examined the five major inter-linked pathways which could lead to the development of tetanus in nomadic neonates. (Figure 1)
Roadblocks and Pitfalls
The Socio-Cultural Pathway
The social status of an individual or a community is the standing or importance it has with respect to others in the society [10]. It is quite often linked with occupation and income levels. Higher income and higher social status are linked to better health [11]. In the case of nomadic populations, their social status is ascribed at birth to be very low in the social ladder. The lack of opportunities for economic progress makes this standing static. The centuries-old legacy of low socio-economic status paves way for social exclusion and isolation from the larger fabric of society around them. This in turn limits the reach and strength of social support networks they are able to form, which reduces the exposure of individuals to health-related information from the mainstream society. However, indigenous societies are also seen to have a strong kinship relationship [4]. When networking is limited, social capital is largely drawn from bonding among the members of the community rather than bridging, leading to re-enforcement and strengthening of existing cultural and social norms within their own community and resisting external opportunities for change. Culture acts as an overarching factor that shapes food choices, health values and patterns of healthcare behavior to a large extend which may be altered to varying degrees by individual experiences and preferences [4]. Personal behavior remains influenced by norms to a large extent, including health-related behavior. Thereby, culturally accepted methods of delivery and child-care thus continue to prevail even in the face of evidence-based medicine.
The Economic-Environmental Pathway
A poor economic status translates to poor environmental conditions as well. The physical environment has two components, the one at home and at the workplace. The families are deprived of necessary provisions such as safe water and sanitation due to the lack of permanent habitation and inadequate public infrastructure, especially in rural areas. This leads to poor personal hygiene. The work environment is also often hazardous, with long working hours and intense physical labor. Manual labor in unorganized settings usually is accompanied by lack of provisions for personal protection or liabilities in case of accident. Many women resume work in the immediate post-natal period and bring the child along to the workplace. Exposure to unsafe environments, both in the home and work environment, in the immediate post-natal period exposes both the mother and child to tetanus.
The Health Literacy Pathway
Literacy is an important determinant of health as it directly influences the person’s exposure to and ability to understand and apply health information. Illiteracy directly leads to poor health knowledge which translates to unhealthy personal behaviors and poor health seeking behavior. Poor health seeking behavior becomes a component of decreased access to healthcare.
The Healthcare Pitfall Pathway
There are two major pitfalls in the current healthcare delivery system which leads to inadequate health care access for the nomadic population. One is the inability of the system to cope up with the unique needs of the nomadic population in terms of follow up across erratic timings and locations. The long working hours which extend beyond the scope of that of the field level health workers form an important basis for the drop in the number of follow up visits. The frequent change of habitat also poses a risk to the viability of follow up. The second pitfall is the stigma and lack of ownership expressed by the health personnel towards the nomadic community. The existent pattern of social exclusion strengthens this negative attitude.
Conclusion
All the different pathways are in no way distinct and lead towards reinforcing the deprivation that the nomadic tribes are subjected to. All of them stem from a paucity of security in terms of basic social and economic needs. When seen in the light of Maslow’s hierarchy of needs, this lack of basic facilities, social isolation and economic vulnerability makes it impossible to focus on progress to a higher state of well-being. Therefore, social security needs to be addressed first. It is possible to integrate indigenous populations with the mainstream society in terms of economic capabilities, job opportunities and health access, even while retaining their cultural distinctiveness, as observed in many societies around the world. However, the most important aspect would be concerted efforts for relevant data generation with respect to these communities which can influence policies and political will. Filling the gaps in the health of indigenous populations will be central to the achievement of global initiatives like Universal Health Coverage and Health for All.
References
- World Health Organization. Tetanus [Internet]. WHO. [cited 2021 Mar 29]. Available from: http://www.who.int/immunization/diseases/tetanus/en/
- World Health Organization. Protecting All Against Tetanus. Switzerland: WHO; 2019. [Google Scholar]
- World Health Organisation. Maternal and Neonatal Tetanus Elimination (MNTE) [Internet]. [cited 2021 Jun 1]. Available from: https://www.who.int/initiatives/maternal-and-neonatal-tetanus-elimination-(mnte)
- Detels R, Gulliford M, Karim QA, Tan CC. Oxford Textbook of Global Public Health. 6th ed. Oxford, United Kingdom: Oxford University Press; 2015. P 1382-91. [doi:10.1093/med/9780199661756.001.0001]
- Gracey M, King M. Indigenous health part 1: determinants and disease patterns. The Lancet. 2009 Jul;374(9683):65–75. doi: 10.1016/S0140-6736(09)60914-4
- Mathew JL. Inequity in childhood immunization in India. Indian Pediatrics. 2012;49: 203-223. [doi:10.1007/s13312-012-0108-3]
- Menzies R, McIntyre P. Vaccine preventable diseases and vaccination policy for indigenous populations. Epidemiological Review. 2006; 28:71-80. [doi:10.1093/epirev/mxj005]
- Misra PK, Malhotra KC, editors. Nomads in India: proceedings of the national seminar. Anthropological survey of India; 1982. [Google Scholar]
- Surendran G, Rehman T, Eliyas S, Kalaiselvy A, Sarkar S. Neonatal tetanus in a nomadic population in South India: A clinic social case study. Indian Journal of Community Medicine. 2020 Jul 1;45(3):384. doi: 10.4103/ijcm.IJCM_306_19
- Social status - Definition of social status in English by Oxford Dictionaries [Internet]. Oxford Dictionaries English. [cited 2021 Mar 17]. Available from: https://en.oxforddictionaries.com/definition/social_status
- World Health Organization. The determinants of health [Internet]. WHO. [cited 2021 Mar 17]. Available from: https://www.who.int/hia/evidence/doh/en/
- Ministry of Social Justice and Empowerment. National Commission for De-notified Nomadic and Semi-Nomadic Tribes. Report - Volume 1. New Delhi: Government of India; 30 June 2008. [Google Scholar]
- Radhakrishna M. Dishonoured by History:" Criminal Tribes" and British Colonial Policy. Orient Blackswan; 2001. [Google Scholar]
- Bajrange D, Gandee S, Gould W. Settling the Citizen, Settling the Nomad:‘Habitual offenders’, rebellion, and civic consciousness in western India, 1938–1952. Modern Asian Studies. 2020 Mar;54(2):337-83. [Google Scholar]
- Ministry of Social Justice and Empowerment. National Commission for De-notified Nomadic and Semi-Nomadic Tribes. Commission Report. New Delhi: Government of India; December 2017. [Google Scholar]
- Renke SB. National Commission for Denotified, Nomadic and Semi-Nomadic Tribes, vol. I. Ministry of Social Justice and Empowerment, Government of India. 2008 Jun;30. [Google Scholar]
- Voice for Change. My father is not a thief: A report by the Ground Level Panel of Denotified and Nomadic Tribes on their Status with Respect to the Sustainable Development Goals. India: Praxis Institute of Participatory Practices; June 2017. [Google Scholar]
- Ministry of Social Justice and Empowerment. National Commission for De-notified Nomadic and Semi-Nomadic Tribes. Draft List of De-notified Tribes, Nomadic Tribes and Semi-nomadic Tribes of India. New Delhi: Government of India; 2017. [Google Scholar]
- Ministry of Social Justice and Empowerment. National Commission for De-notified Nomadic and Semi-Nomadic Tribes. Voices of the DNT/NT Communities in India. New Delhi: Government of India; 2017. [Google Scholar]

Published
Article metrics
- Views
- 1,261
- Downloads
- 672
Based on this site's usage statistics.