Original Article Vol. 8 No. 1 (2024): International J Health Systems and Implementation Research
Prevalence and Correlates of Gastroesophageal Reflux Disease (GERD) amongst undergraduate Students in a city of North India
GERD among undergraduate Students in North India
Downloads
Topics
Keywords:
- GERD, Heartburn, Regurgitation, Stress, Students
Abstract
Gastroesophageal Reflux Disease (GERD) is a chronic gastrointestinal situation with the indications of heartburn and regurgitation. This study aimed to assess the prevalence and its correlates among undergraduate students from a medical college, an engineering college, and a college teaching nonprofessional courses in Chandigarh, a northern city in India. The study was cross-sectional in design and the data was collected using a GerdQ questionnaire. The sample size was 705 students studying in medical, engineering, and non-professional streams in different colleges of the city. The study duration comprised two months. The prevalence of GERD was found to be 11.02% in medical students, 20.09% in engineering students, and 15.74% in students studying non-professional courses. Important risk factors were stress, midnight snacks, tobacco use, and ordering food from restaurants. The prevalence of GERD in all streams was found similar to the prevalence in the Indian population. Lifestyle modifications are recommended in the form of removal of risk factors among students to maintain healthy patterns and balance between study & life.
Full text
This web version was prepared from the published PDF, which is the version of record. Please cite and quote from the PDF.
Introduction
Gastroesophageal Reflux Disease (GERD) is defined a situation that grows when the reflux of stomach contents shows disturbing symptoms and/or complications, such as heartburn, regurgitation, dyspepsia, bloating, belching, Barrett’s esophagus, strictures, asthma, sleep disorders, etc. [1–7]. The disease occurs due to many factors like alcohol, smoking, foods high in fat, spicy foods, chewing tobacco, NSAIDS, carbonated drinks, and so on[8–11].
The frequency of GERD is higher in Western developed countries as compared to Asian countries [11,12]. However, current literature shows an increasing trend in the Indian subcontinent too [10,13]. Two studies conducted in the Southern part of India reported the frequency of GERD in medical students as 14.4% and 5% respectively [14,15]. There were some studies focused specifically on the student population but those were not able to find the difference in the prevalence of GERD among students studying various courses [14,16]. The basis for such an idea is that medical and engineering courses are the most sought-after and the most competitive fields in India [17,18]. Also, it is said that professional students have more stress in comparison to non-professional students.
There is a high level of stress in medical students of India with constant stressors of the vast syllabus, lack of recreational activities, and fear of poor performance or failing exams [18–20]. There have been numerous reports of significant levels of stress in the medical field and there is a paucity of studies that aim to find out about the prevalence of GERD in these student groups [21,22]. Various studies have claimed a significant association between stress and GERD and stress is the cause as well as an aggravator of symptoms of GERD [23–25].
Most of the studies are available for the general population rather than a target population for students. Therefore, this study aims to find out the prevalence and correlates of GERD in various student groups and if there is any significant difference in prevalence and risk factors between students studying medical, engineering, and non-professional courses. This is the first time such a study has been conducted to compare prevalence and risk factors among three student groups, viz. medical, engineering, and non-professional courses. Such an idea stems from the fact that these courses are completely different from each other and provide a different environment for the students.
Methodology
The participants for the study were undergraduate students of a medical college, an engineering college, and a college teaching non-professional courses in the city. The present study was cross-sectional and was conducted using a semi-structured questionnaire and GerdQ questionnaire for symptomatic assessment of GERD.
The sample size calculated before the start of this study was 210 from each of the colleges which was calculated by a prevalence of 16.2%, a confidence interval of 95%, and an absolute precision of 5%[16]. The sample drawn from medical college was 236, from engineering college 234, and from a non-professional course college was 235. Hence, the total sample size ultimately consisted of 705 students. The total period of the study was two months.
The participants were recruited by simple random sampling. The study was well described to the students and then a written consent was taken from those who agreed to be a part of the study. Names of the students were taken from the muster roll of the class/batch and participants were chosen randomly. The questionnaire comprised basic information to account for sociodemographic factors, dietary habits, physical exercise, usage of medicines, diseases in the family and to assess any associated medical conditions like asthma. For the symptomatic assessment of GERD, the GERDQ questionnaire was used which was developed and validated by Jones R et al. in 2009 comprising four positive predictors of GERD: heartburn and regurgitation (the two characteristic symptoms of GERD, sleep disturbance, and use of Over the Counter (OTC) medication [26]. Two negative predictors of GERD, epigastric pain and nausea are also considered. The students were asked to grade their symptoms varying from 0 to 3 (for positive predictors) and from 3 to 0 (for negative predictors) based on how many days in a week they have these symptoms. The GerdQ score was computed as the sum of these scores, giving a total score varying from 0 to 18. A score more than or equal to 8 would be considered a student having GERD which has been validated by various studies [26–28].
Prior permission was taken from the heads of the respective institutions for conducting the study. The project was approved by the Institutional Ethics Committee (IEC) vide no. (GMCH/IEC/2019/339).
Statistical analysis
SYSTAT software version 13.2 for Windows (San Jose, CA: Inpixon Inc) was used to analyze the data. Continuous data was presented as mean and standard deviation whereas qualitative data was represented as frequency and proportions. The association between nominal variables is calculated by the Chi-square test. For the comparison of means, a T-test and ANOVA were used. A forward stepwise (likelihood ratio) binary logistic regression was applied to compute the strength of the association between risk factors and GERD diagnosis by the GerdQ questionnaire. P-value less than 0.05 (p<0.05) was considered significant.
Results
There were a total number of 705 students with 490 (69.5%) males and 215 (30.5%) females. GERD prevalence was 15.6%, highest among engineering students (20.09%), 11.02% in medical students, and 15.74% in students studying non-professional courses. Table 1 and Table 2 show the gender differences and stream-wise distribution concerning anthropometric parameters.
| Variable | Male (n=490) | Female (n=215) | P-value* |
|---|---|---|---|
| Age | 18.89 ± 1.23 | 18.83 ± 1.28 | 0.556 |
| Weight | 68.064 ± 13.24 | 54.56 ± 11.33 | 0.001# |
| Height | 1.66 ± 0.12 | 1.57 ± 0.07 | 0.001# |
| BMI | 24.68 ± 5.10 | 21.99 ± 4.58 | 0.001# |
*Independent t-test, #statistically-significant
| Factor | Medical (n=236) | Engineering (n=234) | Non-professional (n=235) | P-value* |
|---|---|---|---|---|
| Age | 19.42±1.41 | 18.75±1.00 | 18.46±1.12 | <0.001 |
| Body weight | 65.79±13.76 | 68.17±12.87 | 57.88±13.69 | <0.001 |
| Height | 1.61±0.12 | 1.66±0.13 | 1.65±0.10 | <0.001 |
| BMI | 25.40±4.89 | 24.94±4.84 | 21.26±4.55 | <0.001 |
*One Way ANOVA
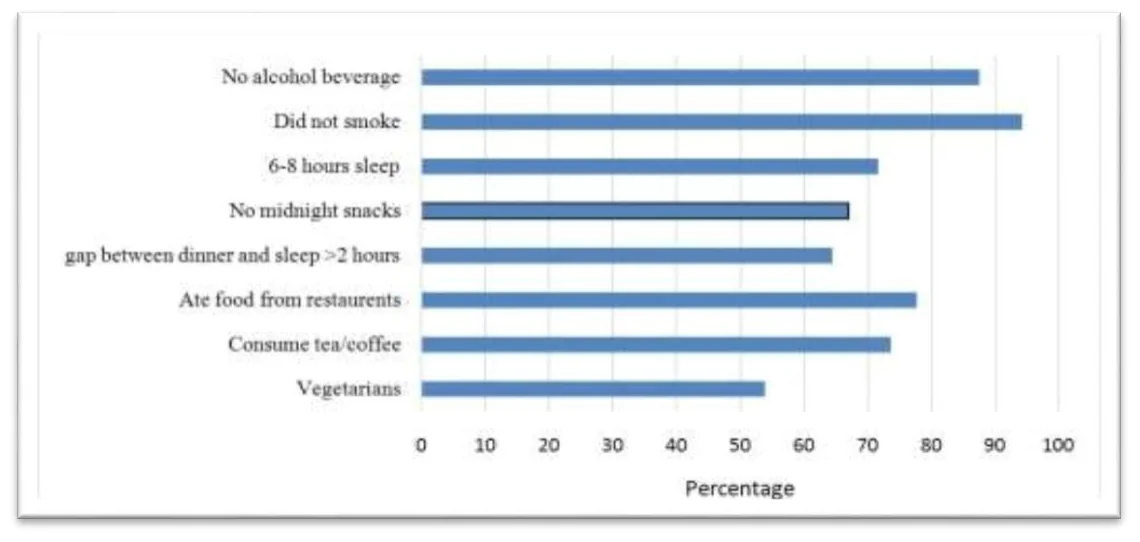
The dietary characteristics are shown in Figure 1. 71.9 % of the participants did some form of physical exercise and the frequency of exercise among these were daily (33.9%), 5 times a week (32.5%), and less than 5 times per week (33.6%). 30.6 % of respondents complained of symptoms of heartburn and regurgitation. Among those with these complaints, 83.1% of them had these occasionally, 13.3% weekly, and 3.6% daily. 70.7% of respondents said that the symptoms resolved on their own, and 14% took medication for the same. 92.1 percent of the students did not have a history of anyone with similar problems of GERD in the family and 7.9% of them had some family member with a GI disease.
| Group | Risk factors | P-value | Odds Ratio (CI= 95%) |
|---|---|---|---|
| Medical | Consumption of a non-vegetarian diet | 0.047 | 0.667 (0.44-0.99) |
| Heartburn/Regurgitation | 0.001 | 0.057 (0.02-0.19) | |
| Engineering | Gap between dinner & sleep | 0.006 | 2.830 (1.35-5.93) |
| Midnight snack | 0.025 | 0.465 (0.24-0.91) | |
| Chewing of tobacco | 0.105 | 8.315 (0.64-107.77) | |
| Heartburn/Regurgitation | 0.000 | 0.173 (0.08-0.36) | |
| Use of antacids | 0.018 | 0.418 (0.20-0.85) | |
| Non-professional | Consumption of non-veg diet | 0.009 | 1.519 (1.11-2.08) |
| Food from restaurants and online apps | 0.059 | 1.988 (0.97-4.06) | |
| Physical exercise | 0.007 | 3.249 (1.38-7.66) | |
| Heartburn/ Regurgitation | 0.004 | 0.281 (0.12-0.67) | |
| Use of antacids | 0.000 | 0.128 (0.05-0.31) |
Regarding risk factors for GERD, different risk factors were found significant in different streams with heartburn/regurgitation being the common factor in all streams. Table 3 displays the univariate association between GERD and risk factors in different streams. On statistical analysis, Hosmer–Lemeshow goodness of fit statistic indicated the appropriateness of the forward stepwise (likelihood ratio) binary logistic regression model. Among the engineering students, chewing tobacco had an 8.31 times chance of suffering from GERD which was not statistically significant. Similarly, in non-professional students, consumption of a non-vegetarian diet was associated with 1.5 times the chance of GERD which was statistically significant.
Discussion
In the current study, the frequency of GERD in students pursuing engineering was the highest (20.09 %), followed by non-professional course students (15.74%) and the medical group of students (11.02%). The frequency of GERD in our study is more than reported by a study done on medical students [15]. This could be accredited to the higher levels of awareness amongst medical students concerning the disease.
In the study conducted among medical students in Puducherry (India), authors reported consumption of carbonated drinks and tea/coffee as significant factors but we could not find any significance of these risk factors in the present study[15]. Another study by Locke et al. where respondents were mailed questionnaires had increased odds of frequent reflux symptoms with positive family history, alcohol consumption, and tobacco use[8]. There was no association found between NSAID intake and coffee consumption, whereas in our study we found an association between painkiller intake with GERD in the non-professional group of students.
In a study among university students in Saudi Arabia, the risk factors found were similar to our study which were high BMI, food from restaurants, family history of GERD, and less time between sleep and dinner [29]. Another study by Jansson C et al. found that fatty food, fried, sour, spicy, and sweet food had significant odds of producing GERD[25]. This finding was similar to our study where food ordered from restaurants had a significant bearing on students pursuing non-professional courses. A gap between dinner and sleep (<two hours) and midnight snack was found significant in the Nagahama Study [5]. Another study among medical students in Chennai found a significant family history of GERD, alcohol consumption, and smoking for reflux symptoms [14].
The number of risk factors in the engineering and non-professional group of students was higher than in the medical group which also explains why the prevalence is higher in them rather than the latter groups. Also, the risk factors common in all groups were the presence of heartburn and regurgitation which again proves the Montreal consensus statement right [1]. The factor common to medical and non-professional students was the consumption of non-vegetarian food. The factor common in engineering and non-professional students is the use of antacids. So, initially, we had thought that the frequency of GERD would be larger in the medical group than in the other two groups but this turned out to be false. The model we have used to make these deductions has a validity of 83% in the medical group, 79.9% in the engineering group, and 83.1% in the non-professional group.
This study is limited by the point that we were not able to analyze posture and head position during sleep, classifying food tastes of students (sour, spicy, sweet), and late dinner time. These factors have been found significant in other studies as discussed above. Also, the study had a small sample size and small study duration. However, this study could be used to predict risk and diagnose GERD which may lead to early intervention and reduction in costs arising due to the impediments of GERD.
The outcomes of the study would help assess the prevalence of GERD and its variations in various student groups based on the course they are pursuing. It may also help the policymakers in formulating relevant changes in the different curricula of various medical and non-medical courses and changes in student lifestyle too. This could lead to mitigation of the risks that aid in the development of disease and hence prevent any usage of drugs or invasive procedures to curb the illness. The current study has been able to identify the risk factors that may be important in diagnosing GERD in various groups of students belonging to different streams.
Conclusion
The prevalence of GERD among students is high with varying risk factors responsible for it. For a primary care physician who is the first one to come in contact with these patients, lifestyle modification is the first point to be stressed which includes controlling weight, increasing the time gap between dinner and sleep, and avoiding a midnight snack. These are already part of public health and would bolster the argument for more spending on primary healthcare. This also brings us to an important link between lifestyle modifications and non-communicable diseases
Acknowledgments
The authors acknowledge the financial support of the Indian Council of Medical Research (ICMR) for their financial support in the form of a Short-Term Studentship (STS) scholarship.
References
- Vakil N, Van Zanten SV, Kahrilas P, Dent J, Jones R. The Montreal definition and classification of gastroesophageal reflux disease: a global evidence-based consensus. Am J Gastroenterol. 2006;101:1900–1920. [doi:10.1111/j.1572-0241.2006.00630.x]
- Badillo R, Francis D. Diagnosis and treatment of gastroesophageal reflux disease. World J. Gastrointest Pharmacol Ther. 2014,5:105-112. [doi:10.4292/wjgpt.v5.i3.105]
- Fennerty MB. The continuum of GERD complications. Cleve Clin J Med. 2003,70:33–50. [doi:10.3949/ccjm.70.suppl_5.s33]
- Harding SM. Gastroesophageal reflux and asthma: insight into the association. J Allergy Clin Immunol. 1999, 104:251-259. [doi:10.1016/s0091-6749(99)70360-x]
- Murase K, Tabara Y, Takahashi Y, Muro S, Yamada R, Setoh K. et al., Gastroesophageal reflux disease symptoms and dietary behaviors are significant correlates of short sleep duration in the general population: the Nagahama Study. Sleep. 2014 , 37:1809–1815. [doi:10.5665/sleep.4176]
- Song EM, Jung HK, Jung JM. The association between reflux esophagitis and psychosocial stress. Dig Dis Sci. 2013,58:471-477. [Google Scholar]
- Kim SY, Kim HJ, Lim H, Kong IG, Kim M, Choi HG. Bidirectional association between gastroesophageal reflux disease and depression: two different nested case-control studies using a national sample cohort. Nature. 2018,8:1-8. [doi:10.1038/s41598-018-29629-7]
- Locke GR, Talley NJ, Fett SL, Zinsmeister AR, Melton LJ. Risk factors associated with symptoms of gastroesophageal reflux. The Am J Med. 1999, 106:642–649. [doi:10.1016/s0002-9343(99)00121-7]
- Jarosz M, Taraszewska A. Risk factors for gastroesophageal reflux disease: the role of diet. Prz Gastroenterol. 2014, 9:297-301. [Google Scholar]
- Koul RK, Parveen S, Lahdol P, Rasheed S, Shah NA. Prevalence and risk factors of gastroesophageal reflux disease (GERD) in adult Kashmiri population. Int J Pharm Pharm Sci. 2018, 10:62-66. [doi:10.22159/ijpps.2018v10i8.25894]
- Jung HK. Epidemiology of gastroesophageal reflux disease in Asia : a systematic review. J Neurogastroenterol Motil. 2011, 17:14–27. [Google Scholar]
- Goh KL. Emerging gastrointestinal and liver diseases in Asia Pacific: implications to health care in the region (world gastroenterology organization: Asian Pacific association of gastroenterology distinguished global lecture 2015). J Clin Gastroenterol. 2017, 51:479–485. [Google Scholar]
- Gaddam S, Sharma P. Shedding light on the epidemiology of gastroesophageal reflux disease in India a big step forward. Ind J Gastroenterology. 2011, 30:105-107. [Google Scholar]
- Karthik RC, Balaji SM, Balaji A, Sriram RM, Ezhilvanan M. Prevalence of gastro esophageal reflux disease among medical students in Chennai, South India. Ind J Forensic Community Med. 2017, 4:199-203. [Google Scholar]
- Arivan R, Deepanjali S. Prevalence and risk factors of gastro-esophageal reflux disease among undergraduate medical students from a southern Indian medical school: a cross-sectional study. BMC Res Notes. 2018, 11:1-5. [doi:10.1186/s13104-018-3569-1]
- Sharma PK, Ahuja V, Madan K, Gupta S, Raizada A, Sharma MP. Prevalence, severity, and risk factors of symptomatic gastroesophageal reflux disease among employees of a large hospital in northern India. Indian J Gastroenterol. 2011, 30:128–134. [Google Scholar]
- Bordbar G, Bolandnazar NS. Gastroesophageal reflux disease (GERD): prevalence and association with psychological disorders among medical sciences students. Int J Pharm Tech Res. 2015, 8:120-130. [Google Scholar]
- Shukla A, Joshi R. Academic stress among professionals and non – professional students. The Int J Ind Psycho. 2017, 4:182-188. [Google Scholar]
- Anuradha R, Dutta R, Raja JD, Sivaprakasam P, Patil AB. Stress and stressors among medical undergraduate students: a cross-sectional study in a private medical college in Tamil Nadu. Indian J Community Med. 2017, 42:222-225. [doi:10.4103/ijcm.ijcm_287_16]
- Supe AN. A study of stress in medical students at Seth G.S. Medical College. J Postgraduate Med. 1998, 44:1-6. [Google Scholar]
- Jafri SAM, Zaidi E, Aamir IS, Aziz HW, Imad-ud-Din, Shah MAH. Stress level comparison of medical and non-medical students: across-sectional study done at various professional colleges in Karachi, Pakistan. Acta Psychopathologica. 2017, 3:1-6. [Google Scholar]
- Al-Dabal BK, Koura MR, Rasheed P, Al-Sowielem L, Makki SM. A comparative study of perceived stress among female medical and non-medical university students in Dammam, Saudi Arabia. Sultan Qaboos Univ Med J. 2010, 10:231-240. [doi:10.18295/2075-0528.1192]
- Saeed AA, Bahnassy AA, Al-Hamdan NA, Almudhaibery FS, Alyahya AZ. Perceived stress and associated factors among medical students. J Family Community Med. 2016, 23:166-171. [doi:10.4103/2230-8229.189132]
- Bradley LA, Richter JE, Pulliam TJ, Haile JM, Scarinci IC, Schan CA. et al., The relationship between stress and symptoms of gastroesophageal reflux: the influence of psychological factors. Am J Gastroenterol. 1993, 88:11–19. [doi:10.1097/00001610-199312000-00015]
- Jansson C, Nordenstedt H, Wallander MA, Johansson S, Johnsen R, Hveem K. et al., Severe gastro oesophageal reflux symptoms in relation to anxiety, depression and coping in a population based study. Alimentary Pharm Ther. 2007, 26:683-691. [Google Scholar]
- Jones R, Junghard O, Dent J, Vakil N, Halling K, Wernersson B. et al., Development of the GerdQ, a tool for the diagnosis and management of gastro-oesophageal reflux disease in primary care. Aliment Pharm & Ther. 2009, 30:1030-1038. [doi:10.1111/j.1365-2036.2009.04142.x]
- Junghard O, Wiklund I. Validation of a four-graded scale for severity of heartburn in patients with symptoms of gastroesophageal reflux disease. Value in Health. 2008, 11:765–770. [doi:10.1111/j.1524-4733.2007.00313.x]
- Bai Y, Du Y, Zou D, Jin Z, Zhan X, Li ZS. et al., Gastroesophageal reflux disease questionnaire (GerdQ) in real-world practice: a national multicenter survey on 8065 patients. J Gastroenterol Hepatol. 2013, 28:626-631. [Google Scholar]
- Alrashed AA, Aljammaz KI, Pathan A, Mandili AA, Almatrafi SA, Almotire MH. et al., Prevalence and risk factors of gastroesophageal reflux disease among Shaqra University students, Saudi Arabia. J Family Med Prim Care. 2019, 8:462-467. [doi:10.4103/jfmpc.jfmpc_443_18]

Published
Article metrics
- Views
- 870
- Downloads
- 426
Based on this site's usage statistics.
Issue
Section
How to Cite
More in this topic: NCDs & mental health
View Point · 2025
From Screens to Sips: Social Media's Impact on Adolescent Alcohol Use