Short Article Vol. 1 No. 1 (2017): Int J Health Systems and Implementation Research
Swine Flu (H1N1) Descriptive Epidemiology for year 2016, in Punjab: Public and Private Sector Medical Institutions Preferred Equally for Treatment
Swine Flu Epidemiology 2016, Punjab
Downloads
Topics
Keywords:
- IDSP
- AR
- CFR
- H1N1
Abstract
Introduction: Seasonal influenza is an acute viral infection that spreads easily from person to person. It can affect people in any age group and is a serious public health problem. To initiate effective control measures, existing local data of state of Punjab was analyzed with the objective to study descriptive epidemiology of H1N1 cases reported in Punjab in year 2016.
Methodology: Data from the Directorate of Health and Family Welfare, Punjab was analyzed to see the age, sex, district wise and hospital wise distribution.
Results: Study showed maximum number of cases reported in adult and old age; higher percentage of urban and female cases. Maximum percentage of cases was reported from district Ludhiana. Public and private sector medical institutions were preferred equally for admissions.
Discussion: Case distribution is as per the previous reported pattern. There are gaps in reporting details that prohibit assessment of Case fatality rate and seasonality of disease. It is recommended to include following data in line list of H1N1cases: Date of admission in hospital, symptoms, history of vaccination, date of positive test report, date of discharge and outcome of case.
Full text
This web version was prepared from the published PDF, which is the version of record. Please cite and quote from the PDF.
Introduction
Seasonal influenza is an acute viral infection that spreads easily from person to person through droplets and fomites. It can affect people in any age group and is a serious public health problem. It can cause severe illness or death especially in people at high risk. Influenza epidemics can affect all populations, but highest risk of complications occur among pregnant women, children aged 6–59 months, the elderly, and individuals with specific chronic medical conditions. Influenza vaccination is the most effective way to prevent disease. Antiviral drugs are available for treatment, though but viruses can develop resistance to the drugs.1
The first confirmed case of A (H1N1) in India was reported on 16th May, 2009. The patient was a passenger who travelled from USA to Hyderabad.2 Thereafter; transmission was reported from many parts of country.3 The states reporting the highest number of cases and deaths are Rajasthan, Gujarat, Madhya Pradesh, Maharashtra, Delhi, and Telangana.4 Punjab has shown lot of fluctuation in reported number of H1N1 cases and deaths annually in years 2010 to 2015 reported so far.5 H1N1 data for the year 2016 was analyzed with the following objective to study the descriptive epidemiology of influenza H1N1 cases reported in Punjab in year 2016.
Methodology
Surveillance system for H1N1 functions in Punjab through IDSP. Data were procured from the Directorate of Health and Family Welfare, Punjab, and was analyzed. As per national guidelines, pharyngeal or nasopharyngeal swabs are collected from suspected cases and their close contacts for detection of virus using real-time-polymerase chain reaction (RT-PCR) assay. A suspected case of influenza like illness (ILI) and laboratory confirmed influenza A had been defined.6
Results
There were 166 H1N1 positive tested cases reported in Punjab in Year 2016. All these cases were of type C.
The mean age of 166 confirmed cases of H1N1 found was 43.07 ± 16.4 years. Among these cases, the minimum age was 3 months and the maximum was 80 years. Table 1 is showing age wise distribution. It shows that maximum number of cases 84 (50.6%) was reported in 21 to 50 years of age followed by 67 (40.4%) in age > 50 years. The minimum 1 (0.6%) case was reported in 0 to 1 year age. The difference in the number of cases in different age groups was found highly significant statistically. (p<0.01). (Table 1)
| Age in years | No. | Percent |
|---|---|---|
| 0-1 | 4 | 2.4 |
| 2-5 | 7 | 4.2 |
| 6-10 | 1 | 0.6 |
| 11-20 | 3 | 1.8 |
| 21-50 | 84 | 50.6 |
| > 50 | 67 | 40.4 |
| Total | 166 | 100.0 |
Sex wise distribution shows that there were 81 (48.8%) males and 85 (51.2%) females. The difference in the number of cases in males and females was found insignificant statistically (Table 2).
| Sex | No. | Percent |
|---|---|---|
| Male | 81 | 48.8 |
| Female | 85 | 51.2 |
| Total | 166 | 100.0 |
There were 101 (60.8%) cases in urban areas and 65 (39.2%) in rural areas. The difference between rural and urban areas was found highly significant statistically.(p<0.01) (Table 3)
| Area | No. | Percent |
|---|---|---|
| Urban | 101 | 60.8 |
| Rural | 65 | 39.2 |
| Total | 166 | 100.0 |
Table 4 is showing the district wise distribution. Maximum number of cases 33, (19.9%) were reported from district Ludhiana, which is the largest district of Punjab, population wise and area wise. No case was reported from district Kapurthala and district Pathankot. Minimum number of cases 1(0.6%) was reported from districts, Hoshiarpur, Ropar, Shahid Bhagat Singh Nagar and Tarn Taran. The number and percentage of cases reported from other districts is given in table 4.
| District | No. | Percent |
|---|---|---|
| Ajitgarh | 11 | 6.6 |
| Amritsar | 6 | 3.6 |
| Barnala | 6 | 3.6 |
| Bathinda | 18 | 10.8 |
| Faridkot | 13 | 7.8 |
| Fatehgarh Sahib | 2 | 1.2 |
| Fazilka | 2 | 1.2 |
| Firozpur | 9 | 5.4 |
| Gurdaspur | 3 | 1.8 |
| Hoshiarpur | 1 | 0.6 |
| Jalandhar | 5 | 3.0 |
| Ludhiana | 33 | 19.9 |
| Mansa | 9 | 5.4 |
| Moga | 9 | 5.4 |
| Muktsar | 13 | 7.8 |
| Patiala | 8 | 4.8 |
| Ropar | 1 | 0.6 |
| Sangrur | 15 | 9.0 |
| Shahid Bhagat Singh Nagar | 1 | 0.6 |
| Tarn Taran | 1 | 0.6 |
| Total | 166 | 100.0 |
The difference between the districts was found highly significant statistically. Bar diagram showing the district wise distribution is shown in figure 1.
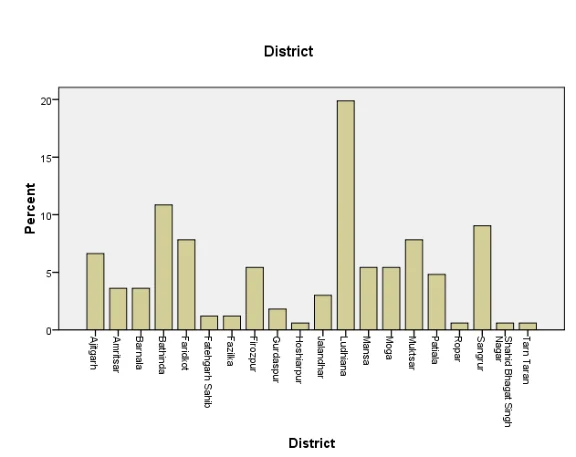
Table 5 shows hospital wise distribution of H1N1 cases of Punjab, admitted in Punjab and Chandigarh hospitals. H1N1 cases were admitted in government and private hospitals. Among government hospitals there are medical education institutions and civil hospitals where patients were admitted. Government medical education institutions comprised of Government Medical College Hospital (GMCH), Amritsar, Government Medical College Hospital (GMCH), Patiala, Guru Gobind Singh Medical College Hospital (GGSMCH), Faridkot, Post Graduate Institute of Medical Sciences and Research Hospital (PGIMERH), Chandigarh and Government Medical College Hospital (GMCH), Chandigarh. In the government institutions of medical education, 53 (31.9%) patients were admitted while in Government Civil Hospitals of Punjab only 7(4.2%) cases were admitted.
| Hospital | No. | Percent |
|---|---|---|
| GMCH Amritsar* | 2 | 1.2 |
| GMCH Patiala* | 4 | 2.4 |
| GGSMCH Faridkot* | 13 | 7.8 |
| PGIMERH Chandigarh* | 29 | 17.5 |
| GMCH Chandigarh* | 5 | 3.0 |
| Govt. Civil Hospitals** | 7 | 4.2 |
| DMCH Ludhiana† | 31 | 18.7 |
| CMCH Ludhiana† | 22 | 13.3 |
| SGRDH Amritsar† | 3 | 1.8 |
| AMCH Bathinda† | 3 | 1.8 |
| Other Private Hospitals†† | 47 | 28.3 |
| Total | 166 | 100.0 |
* = Government Medical College Hospital/ PGIMER Hospital ** = Govt. Civil Hospitals **= Private Medical College Hospitals †† = Other Private Hospitals
Among private hospitals there are medical education institutions and other private hospitals where patients were admitted. Among private medical education institutions there are Dayanand Medical College Hospital (DMCH), Ludhiana, Christian Medical College Hospital (CMCH), Ludhiana, Sri Guru Ram Das Hospital (SGRDH) Amritsar and Adesh Medical College Hospital (AMCH) Bathinda. In these private institutions of medical education 59 (35.5%) cases were admitted while in other private Hospitals of Punjab only 7(4.2%) patients were admitted.
Maximum number of H1N1 cases, 31(18.7%) were admitted in DMCH Ludhiana followed by PGI Chandigarh
Discussion
Previous studies have shown that number of H1N1 cases and deaths has fluctuated a lot in the past years. In 2010, there were 139 cases and 14 deaths from H1N1 in Punjab. In 2011, there were 46 cases and 14 deaths. In 2012 this number decreased further to 13 cases and 4 deaths. Year 2013 showed increase to 183 cases and 42 deaths. It again decreased in 2013 to 42 cases 3 deaths. There were 300 cases and 61 deaths in 2015 5
In this study, maximum number of cases 84 (50.6%) reported in adult and old age groups resembled the previous studies.6,7 Higher percentage of cases found in the urban areas is like the previous study.7 Little higher percentage of female cases but with insignificant difference is just like the previous study 13 but contrary to another study. 6
Our analysis shows that medical institutes are preferred for admissions compared to general hospitals. There is not much difference in selection of government (32% admissions) or private institutions ( 35% admissions). Govt. civil hospitals (4%) and private hospitals (4%) also did not differ much. Considering that private sector is generally preferred for treatment of acute illnesses, this study shows that public sector is competing well with the private sector for management of H1N1. This may be because, due to global threat and high case fatality, there is high alert in the states and epidemic preparedness is done on war footings.
Case fatality rate could not be calculated as the deaths of cases had not been recorded in the data. Seasonality of the disease also could not be assessed as the dates and months of occurrence of cases were not recorded in the data. Hence it is recommended that for preparing the more effective State Action Plans to prevent and control H1N1 cases in state, following data should be included in the line list of H1N1 cases and discussed with the district surveillance officers: Date of admission in hospital, symptoms, especially fever, running nose and respiratory distress, history of vaccination, date of positive test report, date of discharge and outcome of case (Recovered/died/discharged).
Limitations
The study included H1N1 cases confirmed in designated laboratories. Thus there is under-reporting of cases due to lesser availability of laboratory facilities and underestimate of the cases as the cases reported were the patients admitted in Government, Private Medical Colleges of Punjab, PGI and some private hospitals only.
Acknowledgements
Acknowledge the thanks of Directorate of Health and Family Welfare, Punjab for supply of data.
Conflict of interest
Nil
Source of funding
Self
Ethical clearance
Not needed as the study is a part of the ongoing Integrated Disease Surveillance Project (IDSP).
References
- WHO. Fact sheet on influenza: November 2016. [Google Scholar]
- John TJ, Moorthy M. 2009 pandemic influenza in India. Indian Pediatrics. 2010;47:25-31. [doi:10.1007/s13312-010-0007-4]
- Mukherjee A, Roy T, Agrawal AS, Sarkar M, Lal R, Chakrabarti S, et al. Prevalence and epidemiology of pandemic H1N1 strains in hospitals of Eastern India. J Public Health Epidemiology. 01/2010;2(1):171-4. [Google Scholar]
- 2015 Swine Flu toll at 485, more than two-fold jump over 2014. Economic Time (New Delhi). 2015 Feb 13. Retrieved 2015 Feb 17. [Google Scholar]
- Seasonal Influenza (H1N1) State/UT-wise, Year- wise number of cases and deaths from 2010 to 2017 (till 12th November 2017)[Internet]. New Delhi: Ministry of Health and Family Welfare, Government of India, [Google Scholar]
- Inc.;2009 [updated 2017 Nov 13; Cited 2017 Nov 20]. Available from: http://idsp.nic.in/showfile.php?lid=3908
- Mahajan SL. Descriptive epidemiology of H1N1 cases in district Amritsar from year 2009 to 2014. Indian Journal of Public Health Research & Development. 2016 April-June; 7(2):193-9. [Google Scholar]
- Mahajan SL, Devgun P, Raj D, Gill KP, Brar APS. Epidemiological of H1N1 cases in district Amritsar in year 2015. Indian Journal of Public Health Research & Development. 2017 April-June; 8 (2):29-33. [Google Scholar]
Published
Article metrics
- Views
- 1,052
- Downloads
- 881
Based on this site's usage statistics.