Original Article Vol. 3 No. 2 (2019): Int J Health Systems & Implementation Research
The Design, Operations, and Feasibility of Primary Healthcare service Delivery through Mobile Medical Units
A Way for Equitable Health Access and Achieving Universal Health Coverage in Low Resource Settings
Downloads
Topics
Abstract
Background: Mobile medical units supplement and complement the existing public and private health sector in provision of basic primary healthcare services by reaching the last mile. They serve the underserved populations having accessibility challenges in rural and peri-urban areas. However, little evidence exists regarding experiences with such programs. This paper describes the design, operations, and feasibility of running a doctor-led mobile medical unit program in low-resource settings in India. Methodology: Program documents and routinely collected data over four years (July 2015 to May 2019) were analyzed. We present a private sector supported mobile medical unit program model, scope of services, routine operations, and distribution of health morbidities among program beneficiaries in two north-eastern states of India. Findings: Mobile medical units are designed to provide preventive, basic diagnostic, curative, and referral services. Close coordination with government frontline health workers, ensuring uninterrupted doctors availability, supply chain management of drugs and consumables, and information technology-driven data capture are the core program elements. A total of 113,966 beneficiaries (Males 43%; Females 57%) made 206,976 visits (first time visits 55%; repeat visits 45%) during the reference period. Of all visits, young beneficiaries (<19 years) utilized the program services the most (34%), and elderly (≥60 years) the least (12%). Program beneficiaries sought consultations for non-communicable disease (45%), minor ailments (40%), communicable diseases (9%), and reproductive and child health-related conditions (6%). Non-communicable disease-related consultations were higher (48%) in Assam compared to Arunachal Pradesh (35%) (p=0.03). Conclusions: Delivery of basic primary healthcare services through the mobile medical platform is feasible in low resource settings. Such platforms improve health access and equity to bridge the last-mile health service delivery gaps, especially for people suffering from common illnesses. Recommendation: Careful economic evaluations of mobile medical unit based services are required before scaling them elsewhere.
Key Words: Mobile Medical Unit, Primary Care, SPARSHA
Full text
This web version was prepared from the published PDF, which is the version of record. Please cite and quote from the PDF.
Introduction
The rural population in Northeast (NE) India have challenges to access affordable and quality primary healthcare services. Lack of adequate health infrastructure, acute shortage of qualified human resources, including medical doctors, and difficult hilly and riverine terrain are some of the reasons for the widespread health inequities [1]. For example- in Assam, there is 50% shortage of community health centers (CHCs), 41% health sub-centers (HSCs) lack government buildings. Nearly 17% HSCs and 40% of the primary health centers (PHCs) are located beyond 3 and 10 Kilometers radius to any nearest village respectively [1–4].
Compared to international norms (1 doctor per 1000 population and 2 nurses per 1000 population) NE region has a shortfall of 23,000 doctors and has only 0.7 nurses per 1000 population [5]. Although in-position general medical doctors at the PHCs are more than the requirement, there is an acute shortage of specialist doctors in the CHCs of Assam. Similarly, health workers at HSCs level are more than required numbers but with unequal distribution within the districts. State of Assam in NE region has the lowest number of health workers (158) per 100,000 population whereas the standardized availability of health professionals is 343 health workers per 100,000 population in India (health workers include all categories: doctors, specialists, paramedics, laboratory technicians, pharmacists and so on) in both the private and public sectors) [5–8]. Similarly, other NE states are no different in terms of availability of doctors and paramedic staff at the PHCs/ CHCs.
Hence, a weak rural healthcare system in the region contributes to poor health outcomes at the population level. The key health indicators like crude birth rate, infant mortality rate, rate of institutional delivery and immunization in Assam and Meghalaya are well below the national averages [9–11]. The situation highlights the challenge of universal access to basic health services for poor, marginalized and vulnerable populations in NE region [12].
To ensure primary healthcare services, the Government of India recommends running mobile medical units (MMUs) in low resource settings, including the NE region [13]. Evidence from the western world and few studies in India suggest that well equipped MMUs, loaded with adequate drugs and point of diagnostics, serve the purpose of reaching underserved populations in provisioning quality primary healthcare services [14–17].
Piramal Swasthya Management and Research Institute (PSMRI)-a national NGO, has experience and expertise in implementing the MMU programs nationally. The organization implements MMU programs of state governments (public-private partnership) and private companies (private-private partnership) on no-profit and no loss basis. One of the public-private partnership programs of PSMRI, funded through Oil India Limited CSR initiative, operates in remote rural locations of Arunachal Pradesh and Assam state. The program is known as “SPARSHA” – meaning in English “to touch,” provides basic primary healthcare services to the inaccessible and vulnerable population where the public health services are either non-existent or weak.
Considering limited evidence and documentation of MMU programs in India, it gives us an opportunity to study the MMU program design and its implementation in the rural areas of Arunachal Pradesh (Changlang and Namsai districts) and Assam (Charaideo district). Specifically, we describe the SPARSHA program scope, operational elements, key findings, and feasibility of running the program in a low resource setting context.
Methodology
Study design
This is a descriptive cross-sectional study. We describe the MMU program, its design (services), operations and feasibility in one of the low resource settings in rural India.
Program Settings
Assam and Arunachal Pradesh are the two largest states in NE India, sharing their international borders with Bhutan, China, Myanmar, and Bangladesh. The population of Assam is 49 million while Arunachal Pradesh has a population of 1.3 million. Assam’s infant mortality rate (IMR) of 44 per 1000 live births and Arunachal Pradesh’s IMR of 42 per 1000 live births are higher than the national average of 33 per 1000 live births [10]. Sivasagar (now named as Charaideo) district of Assam has 90% rural population. Oil and tea industry is the main economic driver in the district. In Arunachal Pradesh, 77% of the population lives in rural areas and has a high birth rate (18.3 per 1000 population) and infant mortality rate (42 per 1000 live births).
Data Collection and Analysis
We studied the program related documents (MMU service agreement, operational manual) and analyzed the routinely collected program data for four years (July 2015 to May 2019). Document review intends to highlight the design, scope of services and operational aspects of the program. Secondary data analysis reveals the key program operational matrices (service days, type of visitors, socio-demographic factors of the program beneficiaries, and visit pattern) and kind of consultations rendered during the reference period.
Findings
Document Review
SPARSHA Program Model-The Design and Scope
The SPARSHA program provides preventive (screening for diabetes and hypertension through random blood glucose and blood pressure monitoring), promotive (counseling on life-style related, and locally prevalent diseases), diagnostic (urine albumin, haemoglobin and malaria testing), curative (treatment for minor ailments, injuries, including illnesses such as diarrhoea and acute respiratory infections) and referral services (for complicated and high risk cases) to the beneficiaries. The beneficiaries do not have to pay anything either in cash or kind for the services offered.
At present, the program covers the tea estate community in four blocks of Charaideo district, Assam, while in Arunachal Pradesh, it operates in twelve blocks in selected districts (7 in Changlang and 5 in Namsai).
All 16 blocks in the two states are remote, and the population lacks access to basic primary care services. Figure 1 depicts the program model.
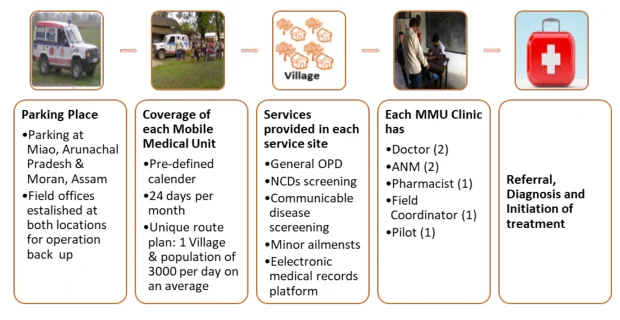
Essentially, SPARSHA program service has two elements, viz. physical and operational elements.
Physical Elements
Manpower
The program has two MMUs running in two states, and each MMU has a six-member team (2 doctors, 2 nurses, 1 pharmacist, and 1 field coordinator). Besides, accredited social health activists (ASHA)-from the state health department, Anganwadi workers (AWW) from women and child development department, and or key community leaders play the role of non-incentivized field volunteers at each service site supporting the MMU team for community mobilization. For operational issues, a base coordinator is stationed at each district headquarters, to ensure smooth functioning of the MMU including fuel and routine MMU vehicle maintenance. The base coordinator reports to zonal Manager, who is responsible for overall program operations, including planning camp schedules and village route.
Equipment & Consumables
The medical equipment in the MMU includes blood pressure measuring machine, thermometer, weighing and height meter scale, eye charts, torchlights, and point of care diagnostics (Blood Sugar, Hemoglobin, Urine, ECG etc.) and teaching aids. Kiosks are placed outside the MMUs for guiding the walk-in beneficiaries. The Government of Assam supplies generic medicines and other consumables on monthly basis.
Data Capture and Management
A computer software application installed on a tablet captures the beneficiary data. The application has different sections including vitals, anthropometry measurements, doctors advise, medicine dispensed, etc. Field coordinator, who keeps the tablet, is responsible to enter the beneficiary data. The data is synchronized daily through a centrally maintained server for further archiving and analysis.
Operational Elements
The zonal manager creates a monthly route plan for each MMU. Each van conducts 24 service camps at different service sites in a month on a fixed day basis. As per schedule and route map, the MMU goes to the designated villages from Monday to Friday (10.00 am to 5:00 pm). The MMU delivers health services to the people approaching the identified service site. Each MMU serves on an average 120-150 beneficiaries per day.
Due to low population density in the operational district of Arunachal Pradesh, each village is covered twice per month. During the rainy season, the MMU team stays for a week in the service areas as the areas usually get flooded and inundated, making it extremely difficult to drive the MMUs. Box 1 highlights the narrative of service flow at a service site.
| Program Parameter/Variable | Assam | Arunachal Pradesh | Total |
|---|---|---|---|
| Service Start Date (DD-DD-YYYY) | 05-07-2015 | 06-08-2015 | - |
| Service Close Date (DD-MM-YYYY) | 30-05-2019 | 30-05-2019 | - |
| No of service days | 1119 | 1077 | 2196 |
| Total Visits (A+B) | N=140572 (68%) n (%) | N=66404 (32%) n (%) | N=206976 (100%) n (%) |
| New or First Time Visits (A) | 79817 (57) | 34149 (51) | 113966 (55) |
| Male | 34806 (44) | 14460 (42) | 49266 (43) |
| Female | 45011 (56) | 19689 (58) | 64700 (57) |
| Old or Repeat Visits (B) | 60755 (43) | 32255 (49) | 93010 (45) |
| Male | 25728 (42) | 13320 (41) | 39048 (42) |
| Female | 35027 (58) | 18935 (59) | 53962 (58) |
| Total Visits (A+B) | 140572 | 66404 | 206976 |
| Male | 60534 (43) | 27880 (42) | 88314 (43) |
| Female | 80038 (57) | 38624 (58) | 118662 (57) |
| Age-wise Distribution of Beneficiaries (On total visits) | |||
| 0-4 years | 10798 (8) | 6161 (10) | 16959 (8) |
| 5-19 years | 37574 (27) | 15419 (23) | 52993 (26) |
| 20-39 years | 44906 (32) | 20078 (30) | 64984 (31) |
| 40-59 years | 31713 (22) | 15365 (23) | 47078 (23) |
| >=60 years | 15581 (11) | 9381 (14) | 24962 (12) |
| Average new beneficiaries per day | 71 | 32 | 52 |
| Average old beneficiaries per day | 54 | 30 | 42 |
| Average total beneficiaries per day (New+Old) | 125 | 62 | 94 |
Box 1: Case narrative illustrating SPARSHA services flow on a routine service day
After suffering from fever from the past two days, Pashotlei Devi (35 years) comes to attend a SPARSHA camp at Hingrijan service point, Assam.
She comes after hearing her husband free medical check-up and medicines distribution at the camp.
On the day of camp, after waiting a few minutes in the queue, Devi gets an outpatient card. Then the nurse at the first counter records her medical history and takes anthropometric information (height, weight) on the outpatient card. She next moves to the second counter, where the field coordinator enters Devi’s details into a computer software application and generates a unique ID. The field coordinator then directs her to meet the doctor at the third counter. The doctor examines Devi and based on her clinical history, he either prescribes medicines or if required advises Devi to meet another nurse at the fourth counter to undergo investigations (random blood sugar, temperature, blood pressure). The Nurse at the fourth counter conducts the investigations and sends Devi back to doctor at counter three with the investigation report. The doctor then prescribes medicines to Devi, following which Devi comes to the fifth counter (pharmacist counter) to receive free medicines. The pharmacist dispenses the medicine, updates the drug stock register and asks Devi to bring her outpatient card in subsequent visits.
Finally, Devi leaves the camp.
Figure 2 describes the services flow at various counters once a patient decides to avail the MMU services.

Secondary Data Analysis
A total of 113,966 newly or first-time registered beneficiaries (57% Assam; 51% Arunachal Pradesh) made 206,976 total visits (68% Assam; 32% AP) during the reference period. The proportion of female beneficiaries (57%) was significantly higher than males (43%). The proportion of repeat visits was higher in Arunachal Pradesh (49%) compared to Assam (43%). Out of all visits, young beneficiaries (>19 years) and beneficiaries in 20-39 years age group utilized the program services the most-34% and 31%, respectively. The average per day total beneficiary caseload was 94 cases (125 Assam; 62 AP) (Table 1).
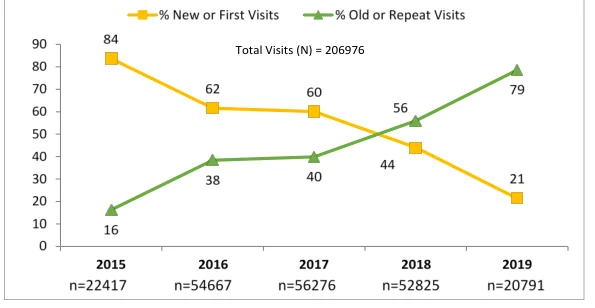
As the program matured (from 2015-2019 until closure), the proportions of new registrations decreased (84% to 21%), and likewise, the repeat visits increased significantly (16% to 79%) (Figure 3).
Non-communicable diseases (45%), minor ailments (40%), communicable diseases (9%) and reproductive and child health conditions were the broad consultation categories for which beneficiaries sought the program services (Table 2).
| Consultation Types | Assam n (%) | Arunachal Praadesh n (%) | Total N (%) |
|---|---|---|---|
| Reproductive & Child Health | 13436 (6) | 6375 (8) | 19811 (6) |
| Communicable Diseases | 22495 (10) | 5284 (6) | 27779 (9) |
| Minor ailments | 84805 (36) | 40895 (51) | 125700 (40) |
| Noncommunicable Diseases | 113779 (48) | 28247 (35) | 142026 (45) |
| Total | 234515 (100) | 80801 (100) | 315316 (100) |
Noncommunicable Diseases: Anemia, Anxiety, Arthritis, Asthma, Diabetes, Epilepsy, Hypertension, Peptic Ulcer, Vitamin A deficiency, Vitamin B deficiency; Communicable Diseases: Acute Respiratory Tract Infections, Diarrhoea/ Dysentery, Helminthiasis, Malaria, Sinusitis, Skin Infection, Tuberculosis; Reproductive and Child Health: Antenatal Care, Postnatal care; Minor ailments: Other than RCH, CDs, & NCDs. Note: The total in this table will not match to total visits in table 1 because a beneficiary may have multiple health conditions in each visit
Discussion
The SPARSHA mobile medical units program is a non-emergency basic primary care service delivery program. The program extends the benefit of primary healthcare to marginalized and vulnerable populations in resource-constrained health settings. The program complements the local government's efforts in areas where public health care delivery systems are weak and unable to deliver quality healthcare services.
The core element of the program design is stakeholder management, which effectively engages the community, frontline health workers, and health authorities at various levels. Meticulous route planning, regular inventory, and supply chain management, and timely monitoring and supportive supervision aid into the operational excellence of the program.
The results of secondary data show interesting statistics. It is evident that the rural population has routine seasonal illnesses but disproportionately suffers from lifestyle-related diseases. A high daily caseload at the service sites itself suggests the importance of providing basic primary care services to vulnerable and marginalized groups. Likewise, a high number of NCD consultations reflects unmet need for NCD care at the grass-root level.
Considering the epidemiological transition in India and increasing prevalence of NCDs in rural India [18–20], the MMU services in low-resource areas seem promising. A growing body of literature supports that MMUs offer an innovative model for health care delivery that could help alleviate health disparities and strengthen the otherwise weak health systems [21].
This article joins a small but consistent body of Indian literature, indicating that MMUs facilitate access to health care. Moreover, we fill an important gap in literature to highlight the design, operational elements, know-how and service outputs of MMUs.
Despite increasing access to quality healthcare services, MMU based service delivery platforms have their own limitations and challenges. For example, providing patient privacy for examination, especially when dealing with pregnant and lactating mothers is an operational but important challenge. Besides, challenging geography, tough terrain and annual flooding in the selected program areas is a constant fight to be able to provide uninterrupted services.
Additionally, it is important to note that MMU service in low resource settings could solve the health issues of rural population from health equity perspective. Vulnerable and marginalized populations, because of geographical or topographical challenges, do need regular healthcare services as required by other population subgroups in urban or semi-urban areas. On the other hand, high proportion of female beneficiaries utilizing the MMU program services can be a step further reducing the gender-related health disparities. Considering the MMUs role in improving health access, MMU based services may be expanded in similar geographical regions after careful economic evaluations.
Conclusion
Carefully designed and implemented MMUs based health programs improve healthcare access in low resource settings. Such programs could be a tool to organize primary healthcare services to vulnerable and marginalized subgroups in advancing the universal health coverage agenda in inaccessible areas and in low resource settings.
Ethical Approvals
Piramal Swasthya Management and Research Institute’s research ethics committee approved the study on 15-07-2019 (Letter no: PSMRI/2019/03). We did not interact with program beneficiaries directly. Anonymous beneficiary data and program documents were accessed therefore there was no need to obtain informed consent. However, we obtained administrative and project level approvals from concerned program managers for data use.
Conflict of Interest
None declared.
Acknowledgement
All field staff who successfully run the program. Devika Chadda for leading and guiding the field activities. Oil India for funding this program.
References
- Saikia D, Das KK. Access to Public Health-Care in the Rural Northeast India. NEHU J. 2014;XII(2):77–100. [Google Scholar]
- Rajbangshi PR, Nambiar D, Choudhury N, Rao KD. Rural recruitment and retention of health workers across cadres and types of contract in north-east India: A qualitative study. WHO South-East Asia J public Heal. 2017; [doi:10.4103/2224-3151.213792]
- International Institute for Population Sciences. District Level Household and Facility Survey-3 Fact Sheets India. 2010. [Google Scholar]
- International Institute for Population Sciences (IIPS) and ICF. District Level Household and Facility Survey-4 Fact sheets India (2012-13). 2014; [Google Scholar]
- State of Affairs. The Past and Future of North East Healthcare. Healthc Exec. 2019; [Google Scholar]
- Sundara T. Munich Personal RePEc Archive Quantity and Quality of Human Resources in Health Care : Shortage of Health Workers in India. 2018;(84332). [Google Scholar]
- Saikia D. Health Care Infrastructure in the Rural Areas of North-East India : Current Status and Future Challenges. J Econ Soc Dev. 2014;X(1):83–99. [Google Scholar]
- Pallikadavath S, Singh A, Ogollah R, Dean T, Stones W. Human resource inequalities at the base of India’s public health care system. Heal Place. 2013;23:26–32. [doi:10.1016/j.healthplace.2013.05.003]
- Sinha S. Health and development in NE India. Mittal Publications, New Delhi; 2014. [Google Scholar]
- International Institute for Population Sciences (IIPS) and ICF. Assam: NFHS 4 (2015 -16). 2015; [Google Scholar]
- International Institute for Population Sciences (IIPS) and ICF. Arunachal Pradesh: NFHS 4 (2015 -16). 2015; [Google Scholar]
- Kumar Jr. Role of public health systems in the present health scenario: Key challenges. Indian J Public Health. 2013;57(3):133. [doi:10.4103/0019-557x.119808]
- Family Welfare M of H. Operational Guidelines for Mobile Medical Units. 2011;(November). [Google Scholar]
- Hill C, Zurakowski D, Bennet J, Walker-White R, Osman JL, Quarles A, et al. Knowledgeable neighbors: A mobile clinic model for disease prevention and screening in underserved communities. Am J Public Health. 2012;102(3):406–10. [Google Scholar]
- Guruge S, Hunter J, Barker K, McNally MJ, Magalhães L. Immigrant women’s experiences of receiving care in a mobile health clinic. J Adv Nurs. 2010; [doi:10.1111/j.1365-2648.2009.05182.x]
- Binepal G, Agarwal P, Kaur N, Singh B, Bhagat V, Verma RP, et al. Screening difficult-to-reach populations for tuberculosis using a mobile medical unit, Punjab India. Public Heal Action. 2015;5(4):241–5. [doi:10.5588/pha.15.0042]
- Kumar A, Khattar P, Tiwari VK, Shivdasani JP, Dhar N, Nandan D. An assessment of functioning of mobile medical units in Jharkhand. Indian J Public Health. 2009;53:157–60. [Google Scholar]
- Joshi R, Cardona M, Iyengar S, Sukumar A, Raju CR, Raju KR, et al. Chronic diseases now a leading cause of death in rural India—mortality data from the Andhra Pradesh Rural Health Initiative. Int J Epidemiol [Internet]. 2006 Dec 1 [cited 2019 Nov 13];35(6):1522–9. Available from: http://academic.oup.com/ije/article/35/6/1522/660009/Chronic-diseases-now-a-leading-cause-of-death-in
- Swaminathan K, Veerasekar G, Kuppusamy S, Sundaresan M, Velmurugan G, Palaniswami N. Noncommunicable disease in rural India: Are we seriously underestimating the risk? The Nallampatti noncommunicable disease study. Indian J Endocrinol Metab [Internet]. 2017 [cited 2019 Oct 3];21(1):90. Available from: http://www.ncbi.nlm.nih.gov/pubmed/28217505
- Dandona L, Dandona R, Kumar GA, Shukla DK, Paul VK, Balakrishnan K, et al. Nations within a nation: variations in epidemiological transition across the states of India, 1990–2016 in the Global Burden of Disease Study. Lancet [Internet]. 2017 Dec 2 [cited 2019 Nov 13];390(10111):2437–60. Available from: https://www.thelancet.com/journals/lancet/article/PIIS0140-6736(17)32804-0/fulltext
- Yu SWY, Hill C, Ricks ML, Bennet J, Oriol NE. The scope and impact of mobile health clinics in the United States: A literature review. Int J Equity Health. 2017;16(1):1–12. [doi:10.1186/s12939-017-0671-2]
- List and number all bibliographical references in 9- point Times, single-spaced, at the end of your paper. When referenced in the text, enclose the citation number in square brackets, for example [1], [3-7]. [Google Scholar]

Published
Article metrics
- Views
- 1,690
- Downloads
- 1,375
Based on this site's usage statistics.