Original Article Vol. 8 No. 2 (2024): International Journal of Health Systems and Implementation Research
Non-Adherence to Anti-Tuberculosis Treatment among Newly Diagnosis Tuberculosis Patients Treated under DOTS in District Raipur, Chhattisgarh
Non-Adherence among Tuberculosis Patients
Downloads
Topics
Keywords:
- DOTS, Knowledge, Non-Adherence, Raipur, RNTCP, Tuberculosis
Abstract
Chhattisgarh is currently facing several challenges with communicable and non-communicable diseases. Tuberculosis is one of the most common communicable diseases in Chhattisgarh. The non-adherence to anti-tuberculosis treatment (ATT) among tuberculosis patients is a big concern in Chhattisgarh. Objective: This study identifies the reasons for non-adherence to anti-tuberculosis treatment among newly diagnosed patients. Methods: The study was a cross-sectional descriptive community-based exploratory study, conducted in selected The DOTS centres had been selected according to convenience and accessibility DOTS centers in Raipur district, Chhattisgarh, from January to April 2018. A total of 47 non-adherent patients were interviewed and data was collected using a self-structured questionnaire. Data was entered and analyzed by using an Excel worksheet and SPSS version 20.0 statistical software. Results: A total of 47 non-adherent patients were interviewed, a total of 47 participants, 91.5% were males and 8.5% were females out of them 91.5% were males and 8.5% were females. The mean age of participants was 40.44 years. 76.6% of non-adherent patients heard about tuberculosis before diagnosis. The main source of information about TB was health workers (42.6%), majority of the patients 75.5% said that Tuberculosis is an infectious disease. About the mode of transmission of disease, a maximum of 25.5% of patients replied as coughing and sneezing. The most important reasons for non-adherence to ATT were side effects of drugs 27.7% followed by alcohol consumption 23%, feel better 21.3%, do not believe in government hospitals 6.4%, co-morbidity 4.3%, migration 8.5%, do not have a disease 6.4%, and accident 2.1%. One of the most contributing factors for non-adherence is the existence of anti-tubercular side effects. Conclusions: The present study revealed that most patients have heard of tuberculosis (TB), however, there is a considerable knowledge gap among TB patients about disease transmission, preventive measures, and duration of the treatment. The most common regions for stopping anti-tuberculosis treatment were adverse effects of anti-tubercular drugs, alcohol consumption, feeling better after a few months of treatment, and migration of patients either to their native place or hunting for new work.
Full text
This web version was prepared from the published PDF, which is the version of record. Please cite and quote from the PDF.
Introduction
TB was the world's second biggest cause of mortality from a single infectious agent, behind coronavirus disease (COVID-19), and it killed nearly twice as many. People with HIV/AIDS. According to the World Health Organization (WHO) Global Tuberculosis Report 2023, there were an estimated 10 million new tuberculosis cases worldwide, of which 5.8 million (55%) were males, 3.5 million (33%) were females and 1.3 million (12%) were children. 6.3% of People living with HIV of all new tuberculosis cases worldwide in 2022. Eight countries accounted for more than two-thirds of the new cases: India, Indonesia, China, the Philippines, Pakistan, Nigeria Bangladesh, and the Democratic Republic of the Congo [1]. Though the Government of India (GoI) has taken several steps towards TB elimination, the disease continues to be a major public health problem in the country [2]. World Health Organization (WHO) has recommended a Directly Observed Treatment Short Course (DOTS) strategy for global tuberculosis control which is accepted worldwide. DOT is the best method to improve the cure rate of tuberculosis. This strategy includes the delivery of a standard short course of drugs, lasting 6 months for new patients and 8 months for previously treated patients who are diagnosed with TB. The delivery of therapy includes the direct observation of either by a health worker or by someone nominated by the health worker for this purpose [3].
The Revised National Tuberculosis Control Program (RNTCP) based on DOTS was launched in 4 districts of Chhattisgarh on August 15, 2002, and achieved statewide coverage in the year 2004. A total of 27 District Tuberculosis Centers (DTCs), 152 Treatment Units (TUs), and 551 Designated Microscopic Centers (DMCs) are providing diagnostic and treatment services in the state. Tuberculosis suspects examined per lakh population has increased from 452/lakh in the year 2013 to 652/lakh in the year 2015 [4]. Decentralizing the diagnostic services for Drug-Resistant Tuberculosis, the Cartridge Nucleic Acid Amplification Test (CBNAAT) is installed in almost all districts of the state.
Chhattisgarh is currently facing several challenges with communicable and non-communicable diseases. Tuberculosis is one of the communicable diseases which is most prevalent in Chhattisgarh. The non-adherence to anti-tuberculosis treatment among patients with tuberculosis is the common reason for an increasing number of Multi-Drug Resistant (MDR) and Extensively Drug Resistant (EDR) tuberculosis, and decreasing cure rate in the state. Patients who interrupted the anti-tuberculosis treatment (ATT) for more than 30 consecutive days were considered non-adherent. Hence this study assessed the knowledge about tuberculosis among non-adherent tuberculosis patients and identified the reasons for non-adherence to anti-tuberculosis treatment among newly diagnosed tuberculosis patients registered under the Revised National Tuberculosis Program (RNTCP) in Raipur district, Chhattisgarh.
Materials and Methods
Setting
This study was conducted at the selected DOTS Directly Observed Therapy Short-course centers in Raipur district, Chhattisgarh India. The DOTS centers had been selected according to convenience and accessibility including 8 Treatment Units (TUs) and 18 Designated Microscopic Centers (DMCs). When the patient is diagnosed with TB, is referred to the DOTS center closer to their residence. The patient is registered at the DOTS center and a treatment card and a patient identity card are provided. A positively diagnosed tuberculosis patient is categorized into two categories new and previously treated. The treatment for both categories of patients consists of two phases; namely intensive and continuous phases. The patient comes to the DOTS center once a week, receives one dose under the supervision of a health worker, and carries home the remaining doses for the week. A patient who did not return for treatment for more than 30 consecutive days was identified from treatment cards at DOTS centers.
Study Population
All newly diagnosed tuberculosis patients (≥18 years) registered under the Revised National Tuberculosis Control Program (RNTCP) who were receiving a DOTS regimen within six months before the starting date of the study and interrupted their treatment for 1 month or more.
Study Design
A cross-sectional descriptive community-based exploratory study design was adopted to find out the factors that influence adherence to anti-tuberculosis treatment. This study was conducted over 4 months from January to April 2018.
Sample Size and Sampling Technique
A convenience sampling method was preferred to access the non-adherent patients. Assistance was given by the health workers and community volunteers (ASHAs) to reach the non-adherent patients. Out of a total of 50 DMCs, it was possible to cover only 18 DMCs and a total of 8 TUs. Overall, 47 non-adherent Tuberculosis patients were included.
Inclusion Criteria
All newly diagnosed non-adherent tuberculosis patients registered under the Revised National Tuberculosis Control Program (RNTCP), and all TB patients≥18 years of age who were listed and receiving anti-tuberculosis treatment at the various DOTS centers.
Exclusion Criteria
All TB patients below the age of 18 years, and all previously treated MDR and XDR tuberculosis patients.
Survey Tool
A pre-tested self-structured questionnaire was prepared for the collection of data. Respondents were identified through patient’s treatment cards at various DOTS centers. The interviews were conducted at their residence through home visits and data was collected over one month between February’ to March 2018.
A written informed consent was taken before data collection and a combination of open and close-ended questions was used to elicit the following information:
- Identification details,
- Demographic details,
- Types of treatment and hospital (Clinical characteristics),
- Knowledge and awareness about tuberculosis, and
- The main reason for missing doses.
Statistical Analysis
The data has been entered into Microsoft Excel sheet and analysis was performed using Excel worksheet and IBM SPSS version 20.0 statistical software. Data were summarized in percentage and frequency distribution tables, and association was tested using the chi-square test, p-value, and graphical data display methods. IBM Corp. Released 2011. IBM SPSS Statistics for Windows, Version 20.0. Armonk, NY: IBM Corp was used for the analysis.
Results
Socio-demographic characteristics of respondents
A total of 47 non-adherent TB patients were interviewed, out of them 91.5% (43) were males and 8.5% (4) were females. The mean age of the total respondents was 40.44 years. The majority of the patients, 42.6% (20) were in the age group of 31-45 years followed by 36.2% (17) of 18-30 years, whereas 21.3% (10) patients were in the age group of more than 50 years. Of the total 47 non-adherent TB patients, 80.9% (38) were married and 19.1% were unmarried. Among 47 respondents, 6.4% (3) had a family size of 1-3 members in a household, 83% had 4-8 members, and 10.6% (5) had more than 6 members in a household.
Out of the total of 47 non-adherent TB patients, a maximum of 89.4% (42) were Hindus, 6.4% (3) were Muslims and only 4.3% (2) were Sikh. Most of them, 59.6% (28) were illiterate and around 40.4% (19) were literate. Of the total 47 non-adherent TB patients, 36% (17) patients were unemployed, and 64% (17) patients were employed. The occupations of employed patients were labor work 19.1% (9), farmer 10.6% (5), business 8.5% (4), students 6.4% (3), homemaker (housewife) 4.3% (2), and other 14.9% (7). About 78.7% (37) of patients were occupants of the urban area while the remaining 21.3% (10) were from the urban area. (Table-1)
| Characteristic | Variables | Frequency (N = 47) | Percentage (%) |
|---|---|---|---|
| Gender | Male | 43 | 91.5 |
| Female | 4 | 8.5 | |
| Age | 18-30 | 17 | 36.2 |
| 31-50 | 20 | 42.6 | |
| >50 | 10 | 21.3 | |
| Marital status | Unmarried | 9 | 19.1 |
| Married | 38 | 80.9 | |
| Family size | 1-3 | 3 | 6.4 |
| 4-8 | 39 | 83 | |
| >8 | 5 | 10.6 | |
| Religion | Hindu | 42 | 89.4 |
| Muslim | 3 | 6.4 | |
| Sikh | 2 | 4.3 | |
| Literacy | Literate | 28 | 59.6 |
| Illiterate | 19 | 40.4 | |
| Occupation | Students | 3 | 6.4 |
| Farmer | 5 | 10.6 | |
| Business | 4 | 8.5 | |
| Labor work | 9 | 19.1 | |
| Homemaker | 2 | 4.3 | |
| Unemployed | 17 | 36.2 | |
| Other | 7 | 14.9 | |
| Residence | Rural | 10 | 21.3 |
| Urban | 37 | 78.7 |
Clinical characteristics of respondents
Of the total 47 non-adherent TB patients, 76.6% (36) were smear positive whereas 23.4% (11) were smear negative. About 61.7% (29) of patients stopped their Anti-Tuberculosis Treatment (ATT) during the intensive phase and around 38.3% (18) during the continuation phase. The majority of the patients, 34% (16) interrupted the anti-tuberculosis treatment during the 3rd month, followed by 10.6% (5) during the 1st month, 32% (15) during the 2nd month, and 23.4% (11) month, 32% (15) during the 2nd month, and 23.4% (11) after the 3rd month. A total of 27.7% (13) patients were taking anti-tubercular drugs from Community Health Centers (CHCs) and 27.7% (13) from Urban Primary Health Centers (UPSCs) followed by District Tuberculosis Center (DTC) 23.4% (11), District Hospital 8.5% (4), AIIMS 4.3% (2), Medical College 4.3% (2) and Primary Health Centers (PHCs) 4.3% (2).
The present study reveals that there is no significant association between socio-demographic parameters (gender, age, literacy, and residence) and phases of treatment interruption and the p-values are 0.567, 0.692, 0.658, and 0.901 respectively. (Table- 2).
| Variables | Phases of treatment interruption (N, %) | Total (47) | X2(df) | P | |
|---|---|---|---|---|---|
| Intensive (N=29) | Continuation (N=18) | ||||
| Male | 26 (60.5) | 17 (39.5) | 43 | 0.32(1) | 0.567 |
| Female | 3 (75) | 1 (25) | 4 | ||
| Age | |||||
| 18-30 | 11 (64.7) | 6 (35.3) | 17 | 0.73(2) | 0.692 |
| 31-50 | 13 (65) | 7 (35) | 20 | ||
| >50 | 5 (50) | 5 (50) | 10 | ||
| Literacy | |||||
| Literate | 18 (64.3) | 10 (35.7) | 28 | 0.19(1) | 0.658 |
| Illiterate | 11 (57.9) | 8 (42.1) | 19 | ||
| Residence | |||||
| Rural | 6 (60) | 4 (40) | 10 | 0.01(1) | 0.901 |
| Urban | 23 (62.2) | 14 (37.8) | 37 | ||
Knowledge about tuberculosis among respondents
Of the total 47 non-adherent TB patients, a maximum of 76.6% (36) heard about tuberculosis before diagnosis of the disease and 23.4% (11) of patients did not hear about the disease. Most of the patients replied that they got information about tuberculosis from health workers 42.6% (20), followed by family members 6.4% (3), media 27.7% (13), and neighbors 4.3% (2). About the infectivity of the disease, 75.5% (35) said yes, it is an infectious disease while 25.5% (12) said as didn’t know. When the patients were asked about the mode of the mode of transmission of disease, 25.5% (12) replied that coughing and sneezing, followed by sharing feeding materials 10.6% (5), through air 23.4% (11), through contact with patient 2.1% (1), and 38.3% (18) answered as do not know.
When the patients were asked about the preventive measures for the spreading of disease, 36.2% (17) of them answered that they didn’t know and another 36.2% (17) answered that covering their mouth and noses while coughing followed by avoiding sharing dishes 12.8% (6), isolate from family members 12.8% (6), whereas only 2.1% replied that they avoid handshaking.
Regarding the availability of the treatment or curability of the disease, most of the patients 89.4% (42) answered yes 6.4% (3) answered as don’t know, and 4.3% (2) answered as no. Regarding treatment options, about 87.2% (41) of patients replied that Allopathic (Government medicines), followed by Ayurveda 2.1% (1), and about 10.5% of patients replied as don’t know (5). About the duration of ATT, most of the patients 63.8% (30) replied that 6 months followed by <6 months 12.8 (6), > 6 months 4.3 (2), and 19.1 (9). (Table-3).
| Characteristics | Variables | Frequency (N=47) | Percentage (%) |
|---|---|---|---|
| Heard about TB before diagnosis | Yes | 38 | 80.9 |
| No | 9 | 19.1 | |
| Source of informationon disease | Health workers | 20 | 42.6 |
| Family members | 3 | 6.4 | |
| Neighbours | 2 | 4.3 | |
| Media | 13 | 27.7 | |
| Infectivity of disease | Yes | 35 | 75.5 |
| No | 12 | 25.5 | |
| Modes of spread of disease | Air | 11 | 23.4 |
| Cough and sneezing | 12 | 25.5 | |
| Sharing food | 5 | 10.6 | |
| Contact with patient | 1 | 2.1 | |
| Don’t know | 18 | 38.3 | |
| Preventive measures of spreading of disease | Cover mouth and nose while coughing | 17 | 36.2 |
| Avoid sharing dishes | 6 | 12.8 | |
| Avoid handshaking | 1 | 2.1 | |
| Isolate from family | 6 | 12.8 | |
| Don’t know | 17 | 36.2 | |
| Availability of the treatment | Yes | 42 | 89.4 |
| No | 2 | 4.3 | |
| Don’t know | 3 | 6.4 | |
| Treatment option | Allopathic | 41 | 87.2 |
| Ayurveda | 1 | 2.1 | |
| Don’t know | 5 | 10.6 | |
| Duration of treatment | <6 months | 6 | 12.8 |
| 6 months | 30 | 63.8 | |
| >6 months | 2 | 4.3 | |
| Don’t know | 9 | 19.1 |
Discussion
In the present study, we found most of the non-adherent patients were male in the age group of 31-50 years and illiterate. Similar findings have been documented by Kulkarni P et al also found that the majority of non-adherent patients were males between 15-49 years [5]. The present study reveals that the maximum number of non-adherent patients 80.9% were married and Hindu (89.4%). Similar findings were observed by Suparna Bagchi et al, in their study where 65% were married and 78% were Hindu. Chhaya Mittal et al also reported that the maximum number of non-adherent patients were Hindu (15.9%) [6][7].
We found a significant number of non-adherent patients 61.3% interrupted ATT during the intensive phase because some of the patients felt better after a few weeks of treatment and some of them were not aware of the total duration of treatment, which is close to the findings of another study done by Kulkarni P et al reported that 51.3% of non-adherent patients were interrupted ATT during intensive phase due to similar reasons which we found [5].
The majority of the patients (34%) stopped their treatment during the 3rd month, followed by 32% during the 2nd month because one of the most common reasons was they felt better and relieved from symptoms after a few months of treatment and considered as they cured. The second most common reason was they did not know about the duration of treatment. A similar pattern of treatment interruption has been also reported by other studies. Sweta Gupta et al found that 72% of patients stopped taking medicine during the 3rd month and a maximum of 30.28% interruptions were found between the 2nd and 3rd months [8].
The study shows that the majority of the TB patients, 80.9% had heard about tuberculosis before diagnosing it and the major sources of information were health workers (42.6%) followed by mass media (27.7%). A study conducted by Das R et al revealed a similar fact where 92.3% heard about tuberculosis before diagnosis and got information from the community (35.9%) followed by health workers (32.3%) [9]. another study conducted by Pramanik D et al also found that most of the patients, 52% had heard about tuberculosis and the major source of information was health workers (26%) [10].
We found that about three-quarters (75.5%) of the respondents knew that tuberculosis was a communicable or infectious disease. Similar findings were also reported in the study conducted by Mukhtar A. et al where 78.7% of patients were aware TB that is a communicable disease [11].
The study shows that nearly half of the studied patients (49%) knew the modes of transmission of the disease. Similar findings have been reported by Mahendra Singh Rathore et al in their study conducted in Udaipur (Rajasthan), they found that about 66.95% of patients knew about the transmission of the disease [12] Knowledge regarding the prevention of transmission of disease, the maximum 36.2% of TB patients replied that cover their mouth and noses while coughing. Similar findings were also observed by Das R et al reported that the majority of the TB patients (53.60%) replied as avoiding uncovered coughing [9].
The current study shows that the majority of TB patients (63.8%) correctly knew about the total duration of anti-tuberculosis treatment and some of the patients were still unaware of the total duration of course. Pramanik D and Ghosh JR reported a similar fact that most of the patients knew the duration of the course [10].
While assessing the main reasons for the Interruption of ATT, we observed that the most common reason for the interruption of ATT among tuberculosis patients was the side effects of drugs, reported by 27.7% of patients. Similar facts were also found in Chhaya Mittal et al demonstrated that side of drugs (43.2%) was the main reason for interrupting ATT among TB patients [13] (Table- 4)(Graph- 1).
| Characteristics | Variables | Frequency (N = 47) | Percentage (%) |
|---|---|---|---|
| Addiction | Yes | 35 | 74.5 |
| No | 12 | 25.5 | |
| Types of addiction | Alcohol | 16 | 34 |
| Smoking | 5 | 10.6 | |
| Chewing Tobacco | 11 | 23.4 | |
| Other | 3 | 6.4 | |
| Side effects | Yes | 24 | 51.1 |
| No | 23 | 48.9 | |
| General weakness | 8 | 17.1 | |
| Restlessness | 5 | 10.6 | |
| Nausea or vomiting | 7 | 14.9 | |
| Burning sensation in abdomen | 4 | 8.5 |
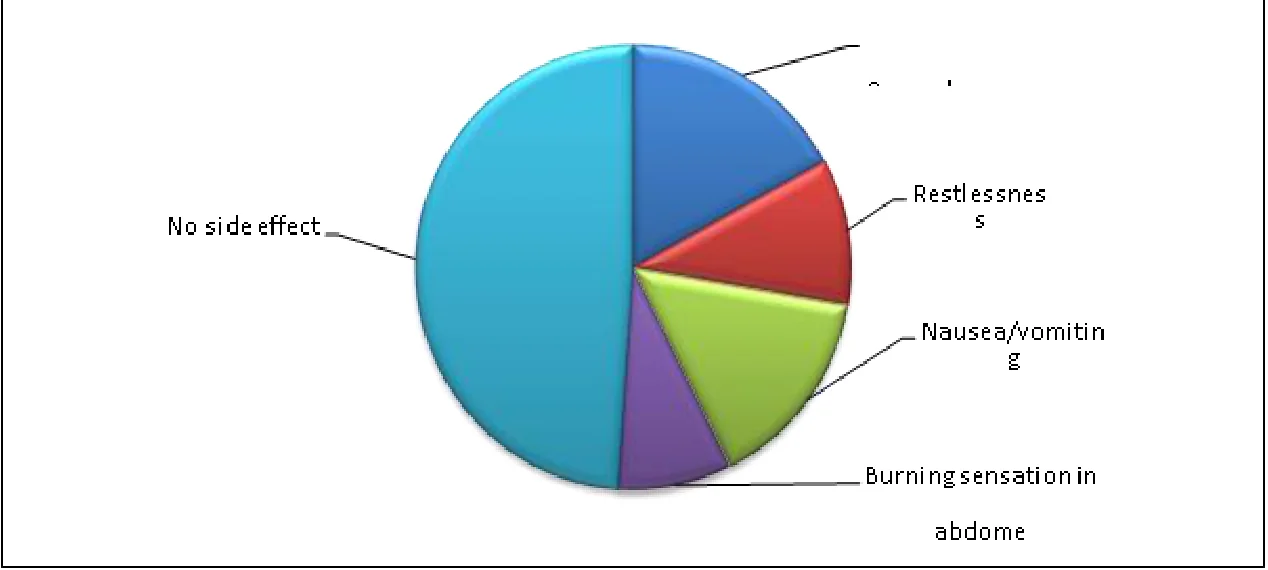
In our study alcohol consumption was the second most common reason for interruption of ATT, as reported by 23% of patients. W. M. Jakubowiak et al reported that the second most common reason for stopping ATT was alcohol use (29.8%) [14].
The third most common reason for interruption of ATT was to feel better or relieved from symptoms of the disease. They considered themselves cured, as reported by 21.3% of patients. Sweta Gupta et al found that feeling early improvement from symptoms of the disease was the first reason for treatment interruption, reported by 30% of TB patients [8].
The next most common reason for treatment interruption was migration (8.5%) either from the native place or searching for new jobs. Kulkarni P et al reported that going to a native place (30.8%) was the first reason for stopping ATT [5].
We found that up to 6.4% of TB patients stopped taking ATT due to the reason of they did not consider themselves sick. Similar findings were also found by W. M. Jakubowiak et al in their study as the third most common reason for interrupting ATT. Reported by 25.3% of patients [14].
Another reason for interrupting the anti-tubercular drug TB patients is because they did not believe in the government hospital and wanted to complete their medication from other private hospitals reported by 6.4% of TB patients. K. Jaggarajamma et al also revealed the same facts [15]. 4.3% of TB patients stopped their medication in between the course because of co-morbidity or having another disease along with TB.
Limitations
The present study's main limitations were its small sample size and a lack of time. Most of the time, patients were not at home because they had to go to work, which made it difficult to trace the patients for interviews.
Recommendations:
Patients, their relatives, and the community are educated about tuberculosis utilizing IEC materials such as flex, posters, slogans, pamphlets, and so on.
Improving awareness about the disease and motivating the patients during treatment may improve adherence to ATT. Adherence to the ATT is a quite challenge when the patients are alcoholics hence special attention and motivation should be given to these patients for adherence to the treatment.
Regular counseling and monitoring should be given to the patients who are having side effects of drugs and co-infection with other diseases because they are more likely to stop the ATT in between the course.
Conclusion
The present study reveals that most of the patients heard about TB but there is a significant knowledge gap among the TB patients about the disease transmission, preventive measures of the disease, and the duration of the treatment. Misconceptions are also present among. Smear-negative tuberculosis patients did not consider themselves sick because most of them did not know about X-ray findings. Some of the tuberculosis patients had stopped their therapy during the first phase or after completing the first phase of treatment because most of them were not aware of the total duration of treatment. The present study also reveals that the most common regions for stopping ATT were side effects of anti-tubercular drugs, alcohol consumption, feeling better after a few months of treatment, migration of the patients to either the native place or searching for new work, having co-morbidity with other disease and accident. Some of the patients did not believe in the government facilities and wanted to complete their treatment at other private hospitals.
Ethical consideration
Ethical clearance for the study was obtained from the Institutional Ethical Committee (IEC) University of Hyderabad, Telangana.
Acknowledgment
Special thanks to Dr. M. Surya Durga Prasad, Assistant Professor, University of Hyderabad, for his support to research. Also, thanks to Dr. Satyanarayan Pandey (District Tuberculosis Officer), District Tuberculosis Center, Raipur, Chhattisgarh, for allowing data collecting. Special thanks to all who assisted in visiting interviewees' homes, and all study participants deserve recognition for their cooperation.
References
- World Health Organization. Global Tuberculosis Report World Health Organization; 2023. Available from: https://www.who.int/teams/global-tuberculosis-programme/tb-reports.
- Thomas BE, Thiruvengadam K, Vedhachalam C, Rao VG, Vijayachari P, Rajiv Y, V R, Bansal AK, Indira Krishna AK, Joseph A, Hussain T. Prevalence of pulmonary tuberculosis among the tribal populations in India. PLoS One. 2021 Jun 4;16(6): e0251519. [doi:10.1371/journal.pone.0251519]
- World Health Organization. An expanded DOTS framework for effective tuberculosis control. Int J Tuberc Lung Dis.. 2002;6:378-88. https://pubmed.ncbi.nlm.nih.gov/12019913/
- Directorate of Health & Family Welfare Government of Chhattisgarh. 2017 (2017). [Google Scholar]
- Kulkarni PY, Akarte SV, Mankeshwar RM, Bhawalkar JS, Banerjee A, Kulkarni AD. Non. Adherence of new pulmonary tuberculosis patients to anti. Tuberculosis treatment. Annals of medical and health sciences research. 2013 Apr 23;3(1):67-74. https://pubmed.ncbi.nlm.nih.gov/23634333/
- Bagchi S, Ambe G, Sathiakumar N. Determinants of poor adherence to anti-tuberculosis treatment in Mumbai, India. International journal of preventive medicine. 2010;1(4):223. https://www.ncbi.nlm.nih.gov/pmc/articles/PMC3075517/
- Mittal C, Gupta SC. Noncompliance to DOTS: How it can be decreased. Indian Journal of Community Medicine. 2011 Jan 1;36(1):27-30. https://www.ncbi.nlm.nih.gov/pmc/articles/PMC3104704/
- Gupta S, Behera D. Reasons for interruption of anti-tubercular treatment as reported by patients with tuberculosis admitted in a tertiary care institute. The Indian journal of tuberculosis. 2011 Jan 1;58(1):11-7. https://pubmed.ncbi.nlm.nih.gov/21434551/
- Das R, Baidya S. A study on knowledge of pulmonary tuberculosis and DOTS among pulmonary tuberculosis patients in west Tripura district, India. SAARC Journal of Tuberculosis, Lung Diseases and HIV/AIDS. 2015;12(1):1-7. https://www.nepjol.info/index.php/SAARCTB/article/view/15935
- Pramanik D, Ghosh JR. Knowledge and awareness of tuberculosis among pulmonary tuberculosis patients in a rural area of West Bengal. SAARC Journal of Tuberculosis, Lung Diseases and HIV/AIDS. 2015;12(2):13-9. https://www.nepjol.info/index.php/SAARCTB/article/view/15950
- Sollimana MA, Hassalia MA, Al-Haddada M, Hadida MM, Saleema F, Aljadheyc H. Assessment of knowledge towards tuberculosis among general population in North East Libya. Journal of Applied Pharmaceutical Science. 2012 Apr 30(Issue):24-30. https://japsonline.com/abstract.php?article_id=422&sts=2
- Chuncha SB. A Study to Assess the Knowledge and Attitude Regarding Tuberculosis and Its Prevention Among Adults in Selected Rural Area of Byahatti Phc with a View to Develop an Information Booklet (Master's thesis, Rajiv Gandhi University of Health Sciences (India)). https://www.researchgate.net/publication/276837647
- Mittal C, Gupta SC. Noncompliance to DOTS: How it can be decreased. Indian Journal of Community Medicine. 2011 Jan 1;36(1):27-30. https://www.ncbi.nlm.nih.gov/pmc/articles/PMC3104704/
- Jakubowiak WM, Bogorodskaya EM, Borisov SE, Danilova ID, Lomakina OB, Kourbatova EV. Social support and incentives programme for patients with tuberculosis: experience from the Russian Federation. The International Journal of Tuberculosis and Lung Disease. 2007 Nov 1;11(11):1210-5. https://pubmed.ncbi.nlm.nih.gov/17958983/
- Jaggarajamma K, Sudha G, Chandrasekaran V, Nirupa C, Thomas A, Santha T, Muniyandi M, Narayanan PR. Reasons for non-compliance among patients treated under Revised National Tuberculosis Control Programme (RNTCP), Tiruvallur district, south India. Indian Journal of tuberculosis. 2007;54(3):130-5. [doi:10.5005/jp/books/10992_63]

Published
Article metrics
- Views
- 312
- Downloads
- 249
Based on this site's usage statistics.