Review Article Vol. 10 No. 1 (2026): International Journal of Health Systems and Implementation Research
Capacity building for Family Medicine in India to strengthen comprehensive primary care and district health systems
Capacity Building for Family Medicine
Downloads
Topics
Keywords:
- Family medicine; Health systems; India; Medical education; Primary health care.
Abstract
Background: India’s health system is attempting to expand comprehensive, life-course primary care through Ayushman Arogya Mandirs while also strengthening secondary care at community, sub-district, and district levels. However, the clinical workforce required to deliver continuity, comprehensiveness, gatekeeping, rational referrals, and integrated care across levels remains underdeveloped. Family Medicine has been recognised in Indian policy for decades and is explicitly supported in the National Health Policy 2017 and reflected in IPHS 2022, yet formal training capacity remains small. Methodology: A focused narrative review and policy analysis were undertaken using official Indian policy and programme documents, current public dashboards, WHO primary care guidance, and recent peer-reviewed studies on Family Medicine in India. Priority sources included the National Health Policy 2017, Indian Public Health Standards 2022, the Ayushman Arogya Mandir portal, the NBEMS accreditation portal, and the 2025 national survey of family physicians in India. Results: India had 186,188 functional Ayushman Arogya Mandirs as of 4 June 2026. These facilities are expected to deliver 12 comprehensive service packages, including NCD care, mental health, elderly and palliative care, and first-level emergency/trauma care. IPHS 2022 includes Family Medicine in CHC service and human resources for health configurations and recommends phased public-system deployment as numbers rise. Nonetheless, recent evidence indicates that in 2023, only 39 accredited private institutions offered DNB Family Medicine, only 110 DNB-FM seats were available nationally, and only seven government medical colleges offered MD Family Medicine. Surveyed family physicians in India worked across public and private sectors and across system levels, with substantial involvement in rural practice, emergency care, inpatient care, home visits, palliative care, and telemedicine. Conclusion: Family Medicine is therefore not a peripheral speciality add-on; it is the clinical architecture needed for India’s comprehensive primary care platform and district health-system redesign to function efficiently. A national capacity-building strategy should combine undergraduate exposure, MD/DNB expansion, faculty development, in-service GP upskilling, structured deployment at CHC/FRU/SDH/DH levels, digital training, accreditation reform, financing incentives, and outcome-oriented monitoring
Full text
This web version was prepared from the published PDF, which is the version of record. Please cite and quote from the PDF.
Introduction
India’s current primary-care reform effort is unusually ambitious in scale. The official Ayushman Arogya Mandir platform reported 186,188 functional facilities by 4 June 2026, intended to provide universal, free, comprehensive primary care close to communities. The program is designed around 12 expanded service packages. It includes non-communicable diseases, oral/eye/ENT care, elderly and palliative care, mental health, and first-level care for emergencies and trauma. This life-course, people-centred orientation closely mirrors the framing of National Health Policy 2017 and the WHO position that primary health care is the programmatic engine for universal health coverage, SDG 3, and health-system resilience [1,3,4].
The challenge is that infrastructure alone does not guarantee integrated clinical care. National Health Policy 2017 calls for comprehensive primary care, primary-level gatekeeping in a phased manner, continuity of care, stronger district and sub-district secondary care, digital linkages between levels, and explicit expansion of MD Family Medicine/General Practice and continuing education for general practitioners. IPHS 2022 similarly builds a care pyramid in which CHCs and FRUs are expected to manage emergency triage, resuscitation, stabilisation, referral, and a broad range of clinical services, while also incorporating Family Medicine into CHC service and HRH configurations [1,2].
Recent evidence suggests that the health system need is clear, but the training pipeline is not. The 2025 national survey of Indian family physicians found that recognised formal training capacity remained very limited in 2023: only 39 accredited private institutions offered DNB-Family Medicine, only 110 DNB-FM seats were available nationally, and only 7 government medical colleges offered MD-Family Medicine; overall, Family Medicine accounted for just over 1% of accredited postgraduate seats. Yet the same survey demonstrated that trained family physicians are already performing roles that map directly to India’s unmet needs: rural practice, primary care, emergency care, inpatient continuity, palliative care, home visits, and telemedicine [5].
These realities make Family Medicine a health-system design question rather than a speciality turf question. If Ayushman Arogya Mandirs, CHCs, FRUs, SDHs, and DHs are to function as a coordinated clinical network rather than as disconnected physical facilities, India requires a larger cadre of broadly skilled clinicians trained for first-contact care, multimorbidity, continuity, referral stewardship, team-based work, emergency stabilisation, and community orientation. This article, therefore, examines how Family Medicine capacity can be built in India across education, service deployment, career pathways, quality assurance, digital systems, financing, and governance [1-6].
Methods
A focused narrative review and policy analysis were undertaken between May and June 2026. Sources were selected purposively for policy salience and implementation relevance. Priority documents were official Indian sources: National Health Policy 2017, Indian Public Health Standards 2022 for CHCs, the Ayushman Arogya Mandir official portal/dashboard, the NBEMS accredited-seats portal, and the ABDM official portal. These were supplemented by WHO primary health care guidance and peer-reviewed literature on Family Medicine in India, especially the 2023 qualitative study on the field’s emergence and the 2025 national cross-sectional survey of family physicians. The synthesis was organised around eight capacity-building domains: undergraduate exposure; MD/DNB expansion; faculty development; service deployment; career pathways; quality and accreditation; CPD/upskilling for practising GPs; telemedicine and digital training; implementation research and monitoring; financing and incentives; and governance. This is a public-document review with no human participants or primary data collection.
Results and Findings
Education and Training Capacity
Family Medicine in India has evolved slowly and unevenly. The qualitative study on its emergence shows that implementation since the 1980s depended heavily on pioneering clinicians, supportive institutions, professional associations, and sustained advocacy. At the same time, barriers included weak government support, poor societal awareness of the discipline, and tension with organ-based specialities. The 2025 survey confirms that these historical constraints continue to shape the present. Most training remains concentrated in southern states, especially Tamil Nadu, Karnataka, and Kerala, and many doctors seeking Family Medicine competencies still rely on part-time, blended, or distance pathways that NMC or NBEMS does not formally recognize [5,6].
The capacity numbers are stark. In 2023, recognised postgraduate Family Medicine capacity consisted of only 39 accredited private DNB-FM institutions, 110 DNB-FM seats, and 7 government MD-FM programs. Even if these numbers have grown somewhat since 2023, the public evidence base still indicates a very small field relative to overall postgraduate training. By contrast, the NBEMS portal currently lists 18,373 accredited seats across DNB/DrNB/FNB/diploma pathways overall, demonstrating that the national postgraduate platform is large enough for Family Medicine’s share to expand substantially if policy signals change [5,11].
For practising MBBS doctors, the need is not only for new residencies but also for structured re-training and upskilling. National Health Policy 2017 explicitly recommends “a large number of distance and continuing education options for general practitioners in both the private and the public sectors,” precisely to enable local management of the large majority of cases and reduce unnecessary referrals. The 2025 survey provides empirical support for this direction: 39.0% of respondents had completed part-time, distance, or blended Family Medicine training, and many reported a long interval between MBBS graduation and postgraduate Family Medicine education, indicating mid-career demand for reskilling rather than only for fresh postgraduate entry [1,5].
Undergraduate exposure is the missing upstream lever. The survey authors note that role models and teachers are required if students are to consider Family Medicine as a serious career track, and the study found that many family physicians already occupy teaching roles and train non-physician providers. This makes faculty development doubly important: it determines not only the size of MD/DNB programs, but also the visibility of Family Medicine as a legitimate academic discipline in undergraduate education and internship [5,6].
Service Deployment across CHC, FRU, SDH, and DH
The current Indian policy strongly supports the service case for Family Medicine. National Health Policy 2017 calls for a phased primary-level gatekeeping mechanism backed by effective feedback and follow-up, and it explicitly states that most secondary care should be available at the district level, with basic secondary care such as caesarean section and neonatal care available at least at the sub-divisional level. It further expects specialist-type skills to be currently available within districts and, in part, at the sub-district level through stronger district-and sub-district-level hospitals [1].
IPHS 2022 operationalises this logic for CHCs and FRUs. The CHC guideline includes Family Medicine in service listings, includes a Physician/Family Medicine Specialist in the HRH matrix, recommends phased public-system deployment of family medicine physicians as their numbers increase, and details emergency triage, resuscitation, stabilisation, referral, and 24x7 emergency functioning. It also defines infrastructure and workflow expectations linking emergency care, OT, diagnostics, and referral pathways [2].
The 2025 survey suggests that Indian family physicians are already practising in ways that fit these roles. In that study, 88.9% provided outpatient Family Medicine, 68.2% provided hospital inpatient care, 55.8% emergency services, 61.7% palliative care, 66.0% home visits, and 84.2% telemedicine. Family physicians in rural areas were more likely to offer minor office-based surgery, splinting/casting, and vaginal delivery. Respondents worked across all tiers of the health system, from primary care to tertiary hospitals and academic institutions [5].
These data matter for deployment design. At the CHC/FRU level, family physicians can anchor outpatient continuity clinics, inpatient oversight, NCD and multimorbidity management, palliative care, emergency stabilisation, referral decisions, and clinical mentoring of medical officers and non-physician teams. At the SDH/DH level, they can operate at the primary-secondary interface: managing broad-spectrum medicine, coordinating complex discharges and back-referrals, supporting trauma stabilisation and undifferentiated emergency care, and integrating speciality input through teleconsultation and shared care. This is fully consistent with NHP 2017’s view that teleconsultation should link medical colleges with district and sub-district hospitals for specialist consultation [1,2,3].
Career Pathways in the Public and Private Sectors
One of the most important practical findings from the 2025 survey is that Family Medicine in India is already a dual-sector speciality. Among respondents, 62.1% worked in the private sector alone, 21.2% in the government sector alone, and 16.7% in both sectors. This means that Family Medicine expansion cannot be planned only as a public-service staffing reform. A viable national strategy must create pathways in government CHCs, FRUs, SDHs and DHs. Still, it must also recognise private-sector outpatient practice, hospitals, mission institutions, and mixed public-private careers as legitimate employment destinations [5].
This duality is strategically advantageous. The private sector can absorb graduates quickly, support continuity clinics, and serve as a training base where accredited, especially NBEMS-linked, hospitals are available. The public sector can use Family Medicine to address rural and district shortages, referral overload, service fragmentation, and the absence of clinicians trained for whole-person continuity. But it also means pay scales, promotion criteria, designation structures, and academic recognition must be harmonised enough that graduates are not systematically pushed away from public service [1,5,6].
Quality Assurance, Digital Capacity, Financing, and Governance
IPHS 2022 does not treat human resources in isolation. It embeds capacity building, quality assurance, governance, and monitoring within facility standards.
It requires induction and specialised training of teams, strengthens laboratory quality systems, and explicitly positions IPHS implementation as a route toward NQAS certification. National Health Policy 2017 similarly calls for periodic quality measurement and certification of public hospitals. Family Medicine capacity building should therefore be tied to quality standards, referral governance, and measurable service outputs from the outset rather than treated solely as an educational exercise [1,2].
Digital capacity is already an enabling asset. National Health Policy 2017 recommends tele-education, tele-CME, and tele-consultations through the National Knowledge Network, and specifically advocates teleconsultation linkages between tertiary institutions and district/sub-district hospitals. The Arogya Mandir platform itself foregrounds teleconsultation, and the 2025 Family Medicine survey found that 84.2% of respondents used telemedicine. India’s broader digital-health strategy under the Ayushman Bharat Digital Mission provides an additional platform for longitudinal records, referral tracking, and remote learning [1,3,5,12].
Financing signals exist, but are not yet sufficiently targeted to Family Medicine. National Health Policy 2017 supports financial and non-financial incentives for underserved areas, district-hospital strengthening, more postgraduate seats, and medical education embedded in real service environments. A Family Medicine strategy can therefore be financed through a combination of NHM/PM-ABHIM workforce support, state in-service PG sponsorship, district-hospital DNB expansion, faculty-development grants, and performance-linked facility funding tied to IPHS/NQAS, continuity, and rational referral indicators [1,2].
| Intervention | Main bottleneck addressed | Feasibility | Cost implication | Time horizon | Lead agencies | Suggested indicators |
|---|---|---|---|---|---|---|
| Structured UG exposure in MBBS and internship | Low visibility of Family Medicine; weak career pipeline | High | Low–Moderate | 1–2 years | NMC, medical colleges, and states | Number of colleges with Family Medicine postings, internship slots, student feedback, and proportion choosing FM |
| Expand MD-FM in government medical colleges | Extremely small university-based training capacity | Medium | Moderate–High | 2–5 years | NMC, states, MoHFW | Number of MD-FM departments; seats sanctioned and filled; graduates/year |
| Expand DNB-FM and Diploma FM through NBEMS | Slow scale-up through conventional university channels | High | Moderate | 1–4 years | NBEMS states accredited hospitals | Seats sanctioned; accreditation sites; occupancy rates; pass rates |
| National faculty development and mentoring network | Lack of trained faculty and examiners | Medium | Moderate | 1–3 years | NMC, NBEMS, MoHFW, academic hubs | Faculty trained; mentor hubs; departments with minimum faculty norms |
| Modular upskilling for practising GPs | Large existing MBBS workforce without structured FM re-training | High | Low–Moderate | 1–3 years | MoHFW, NIHFW, NIHFW/NHSRC, and medical colleges | Enrolment and completion rates; competency sign-off; change in referral patterns |
| Deploy FM posts at CHC/FRU first, then SDH/DH | Service platform lacks broad-spectrum specialists | Medium | Moderate–High | 2–6 years | States, NHM, MoHFW | Posts sanctioned/filled; vacancy rates; district distribution; retention after 3 years |
| Link FM deployment to the IPHS/NQAS quality agenda | HR expansion not tied to outcomes or standards | High | Low | 1–3 years | MoHFW states, quality cells | IPHS compliance; NQAS attainment; referral completeness; patient experience scores |
| Digital learning and tele-mentoring | Geographic concentration of expertise | High | Low–Moderate | 1–2 years | MoHFW, ABDM, NBEMS, NMC | Tele-CME sessions; mentor contacts; tele consult utilization; digital case logs |
| Implementation research and national FM dashboard | Weak policy feedback and poor visibility of progress | Medium | Low | 1–2 years | MoHFW, NHSRC, states, and academic units | Annual dashboard publication; research outputs; district performance review cycles |
| Incentives and career pathways in public and private sectors | Attrition, maldistribution, and low perceived value of FM | Medium | Moderate | 1–5 years | MoHFW states that private hospital networks | Rural retention; promotions; dual-sector appointments; proportion in public service |
Source: Author synthesis based on policy documents, public dashboards, and Indian Family Medicine studies.
| Domain | Indicator | Data source | Frequency | Illustrative target by 2030 |
|---|---|---|---|---|
| Training capacity | FM PG seats sanctioned and filled | NMC/NBEMS administrative data | Annual | ≥3-fold increase from 2023 baseline |
| Faculty | Colleges/hospitals meeting minimum FM faculty norms | NMC/NBEMS accreditation reports | Annual | All active FM programs are compliant |
| Service deployment | FM posts filled at CHC/FRU/SDH/DH | State HRMIS, NHM | Quarterly | ≥80% of sanctioned posts filled |
| Rural retention | Proportion of FM graduates working at the rural/district level after 3 years | Alum tracking, state HRMIS | Annual | ≥50% |
| Care model | Share of FM clinicians running continuity clinics | Facility reports | Quarterly | Universal in FM-designated sites |
| Referral quality | Referral and back-referral completeness rate | HMIS/ABDM-linked records | Quarterly | ≥90% complete referral loop |
| Efficiency | Ambulatory-care-sensitive tertiary referrals per 10,000 population | HMIS, hospital MIS | Annual | Downward trend in sentinel districts |
| NCD outcomes | Proportion of registered hypertension/diabetes patients under control | AAM/NCD program records | Quarterly | State-specific improvement targets |
| Emergency care | The proportion of emergency presentations stabilised locally before referral. | CHC/SDH/DH emergency registers | Quarterly | Progressive increase |
| Quality | IPHS compliance and NQAS certification status | Quality cells, external assessment | Annual | All FM-designated facilities on the certification pathway |
| Digital capacity | Teleconsults, tele-CME sessions, and digital records utilisation | ABDM/e-platform data | Quarterly | Year-on-year increase |
| Teaching and research | FM publications, audits, QI projects, and teaching sessions | Institutional reports | Annual | Annual growth across states |
Source: Author synthesis
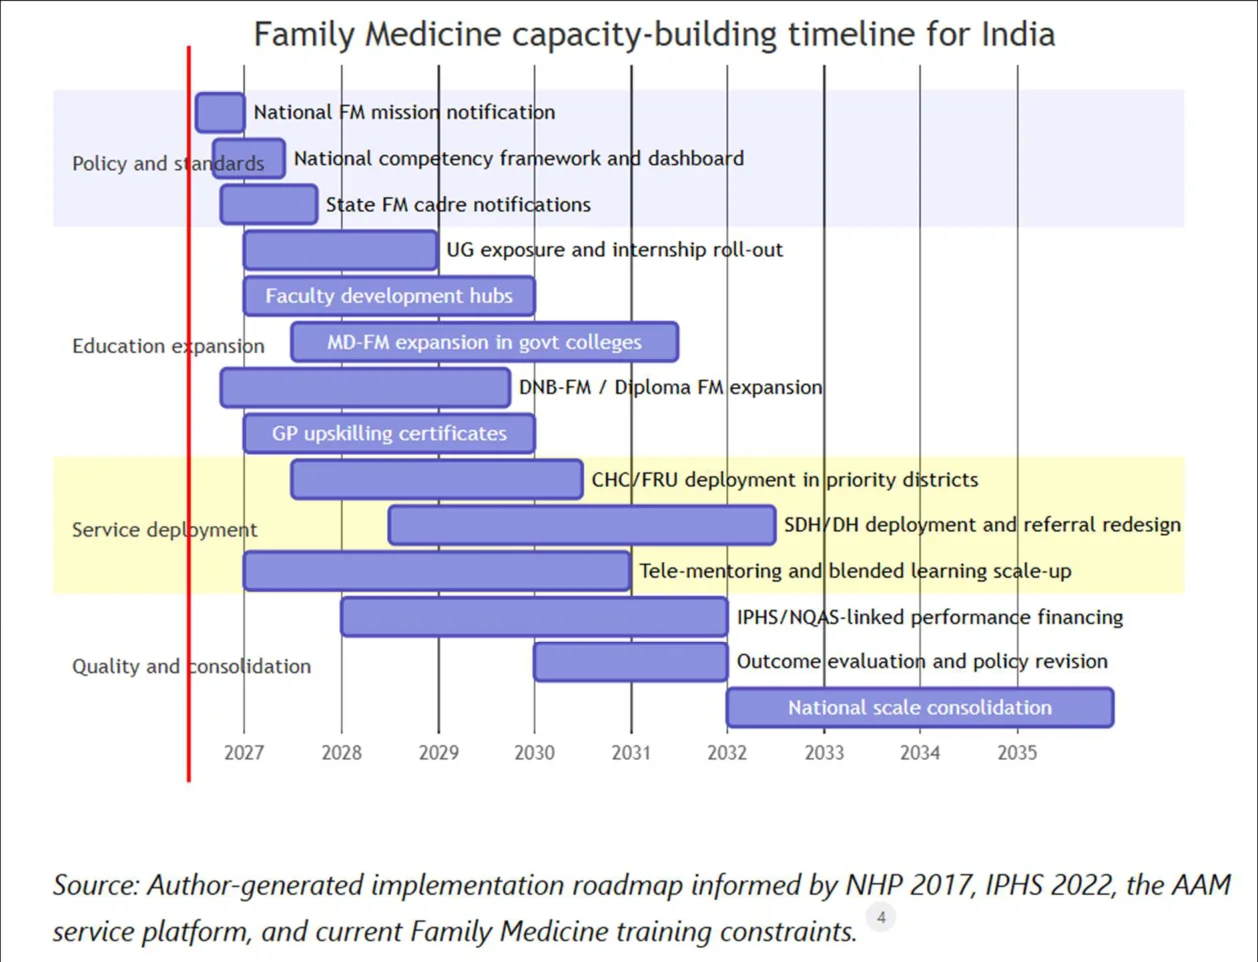
Discussion
The central analytical finding of this review is that Family Medicine is the missing clinical layer between India’s primary-care infrastructure and its desired service model. Ayushman Arogya Mandirs, CHCs, FRUs, SDHs, and DHs are now expected to deliver preventive, promotive, curative, rehabilitative, palliative, emergency, and chronic-care functions across the life course. Yet those functions require clinicians trained not only in biomedical knowledge, but also in continuity, coordination, community orientation, team-based care, referral stewardship, emergency stabilisation, and multimorbidity management. That is precisely the competency package that Family Medicine exists to provide [1-6].
The timing is favourable. India has already created a vast service platform through Ayushman Arogya Mandirs; National Health Policy 2017 provides explicit policy cover for Family Medicine expansion, GP continuing education, district-level skill development, and digital learning; IPHS 2022 has formally created normative space for Family Medicine at CHC/FRU level; and the NBEMS system has national reach that can be leveraged more aggressively for district-based training. The policy problem, therefore, is no longer whether Family Medicine fits the Indian health system. The problem is implementation speed, scale, and governance coherence [1-3,11].
A second important finding is that capacity building must be plural, not singular. It will fail if defined only as “open more MD seats.” India needs a layered strategy: undergraduate exposure to create demand; MD/DNB expansion for new entrants; faculty development to support departments and accreditation; modular re-training for practising GPs; service posts in CHC/FRU/SDH/DH settings; and public-private career pathways to retain talent. The survey data strongly support all of these layers because Indian family physicians already work across sectors and levels, and many have come into the discipline through mid-career routes [5,6].
A third finding is that district and sub-district hospitals are crucial. If Family Medicine is deployed only in primary outpatient settings, its health-system advantage will be artificially narrowed. NHP 2017 clearly places secondary care strengthening at district and sub-divisional levels and emphasises emergency access within the golden hour. Family physicians are well-suited to reduce pressure on tertiary hospitals by managing the “grey zone” between primary and speciality care: undifferentiated illness, short-stay admissions, chronic-disease decompensation, geriatrics, palliative care, discharge planning, referral screening, and trauma or emergency stabilisation before transfer [1,2,5].
The policy risk of inaction is not merely that Family Medicine remains small. The larger risk is that India becomes infrastructure-rich but clinically fragmented: many facilities, many schemes, but inadequate continuity, weak gatekeeping, avoidable referrals, and poor integration across levels. Family Medicine expansion should therefore be seen as core health-system engineering for SDG 3, UHC, and the broader ambition of Viksit Bharat through a life-course model of care [1,3,4].
Recommendations and Actionable Roadmap
Policy actions for MoHFW
MoHFW should launch a National Family Medicine Capacity-Building Initiative under NHM/PM-ABHIM with five concurrent workstreams: training expansion, deployment, quality and accreditation, digital learning, and monitoring. Family Medicine posts should be notified first for CHCs/FRUs in high-referral or specialist-deficient districts, then extended to SDHs and DHs as a defined pyramidal referral model. The ministry should also create a national dashboard tracking seats, graduates, sanctioned posts, filled posts, rural deployment, referral metrics, and quality indicators. These actions sit squarely within NHP 2017 and IPHS 2022 [1,2].
Policy actions for NMC
NMC should ensure meaningful undergraduate exposure to Family Medicine through longitudinal community placements, continuity clinics, Family Adoption Programme-linked reflection, and internship rotations in AAM/PHC/CHC settings. For postgraduate scale-up, NMC should require any medical college seeking new PG recognition in major clinical disciplines to show a time-bound plan to initiate MD Family Medicine or a formally structured Family Medicine department/unit. NMC should also define faculty norms, clarify academic equivalence pathways, and standardise competency-based curricular expectations around continuity, community orientation, referrals, emergency care, mentoring of teams, and digital health. These steps are consistent with NHP 2017’s call to revise undergraduate and postgraduate curricula to reflect changing health-system needs [1,5,6].
Policy actions for NBEMS
NBEMS is the fastest practical route to short-and medium-term scale. It should expand DNB Family Medicine and Diploma in Family Medicine seats in mission hospitals, district hospitals, and strong secondary-care institutions, especially where service volumes support training, but formal university PG structures are absent. A cluster-based mentor model can link each new DNB site to one experienced Family Medicine department. The existing NBEMS national seat platform demonstrates that large-scale accredited expansion is feasible [5,11].
Policy actions for States
States should create a formal Family Medicine specialist cadre with sanctioned posts at CHC/FRU/SDH/DH levels, pay protection for in-service doctors entering FM training, rural and difficult-area incentives, and career ladders linked to clinical leadership, teaching, quality improvement, and district mentoring. States should reserve a proportion of in-service PG sponsorship specifically for Family Medicine and align postings with district needs, not ad hoc vacancies. Over time, Family Medicine should become one of the preferred specialist tracks for district strengthening, emergency stabilisation, and continuity-led chronic care [1,2,5].
Policy actions for medical colleges and teaching hospitals
Medical colleges should establish Family Medicine departments or units with continuity clinics, district-linked rotations, and interprofessional teaching. Faculty development should include train-the-trainer programs, teaching-skills workshops, digital pedagogy, rural mentoring networks, and joint appointments across medical college and district facilities. District and sub-district hospitals should be treated as teaching service hubs, not only as service sites [1,6].
Recommended competency domains for MD and DNB Family Medicine
- A nationally harmonised competency framework should cover:
- First-contact assessment and longitudinal comprehensive care
- Undifferentiated symptom management and diagnostic reasoning
- NCDs, multimorbidity, polypharmacy, and continuity planning
- RMNCH+A, adolescent health, and reproductive health
- Child health, adult medicine, and healthy ageing
- Mental health, substance use, counselling, and psychosocial care
- Palliative, rehabilitative, disability, and home-based care
- Emergency triage, stabilisation, trauma first response, and referral
- Essential office procedures and context-appropriate obstetric/newborn skills
- Community-oriented primary care and public-health integration
- Team leadership, teaching, supervision, and mentoring of non-physician cadres
- Quality improvement, clinical governance, informatics, telemedicine, and ethics
These domains are directly supported by the breadth of Arogya Mandir service packages, CHC/FRU expectations under IPHS, and the documented practice profile of Indian family physicians [1,3,5].
Illustrative curriculum elements for MD and DNB Family Medicine
A practical 3-year residency model should include: continuity clinic across all semesters; rotations in AAM/PHC/UPHC, CHC/FRU, SDH/DH, medicine, paediatrics, obstetrics and normal delivery, emergency and trauma stabilisation, psychiatry/mental health, palliative care, community health, geriatrics, and elective skills relevant to the local context. Trainees should complete logbooks in outpatient continuity encounters, inpatient co-management, emergency stabilisation, referral/back-referral, teleconsultation, audit/QI cycles, home visits, and team teaching. Assessment should blend workplace-based assessment, case-based discussion, OSCEs, reflective portfolios, and service-improvement projects.
Recommended structure for short upskilling courses for Practicing GPs
A 6–12-month modular blended certificate for practicing MBBS doctors should include:
- Management of common undifferentiated presentations in outpatient and inclusive emergency settings;
- NCD screening, treatment initiation, follow-up, and control;
- Common mental health conditions and substance-use disorders;
- Geriatric review, palliative care, and home-based care;
- Maternal, newborn, and reproductive-health red flags;
- Rational prescribing and antimicrobial stewardship;
- Emergency triage, trauma first response, stabilisation, and referral;
- Documentation, telemedicine, ABHA-enabled records, and referral communication;
- Teamwork and supervision of CHOs, nurses, ANMs, and allied cadres.
The course should use self-learning modules, virtual case discussions, district skill labs, supervised practice days, and competency sign-off by accredited mentors. NHP 2017 explicitly supports this kind of distance and continuing education pathway [1,5].
Conclusion
India has moved decisively to expand the platform for comprehensive primary care. The next decisive move must be to build the clinical workforce architecture that allows that platform to perform. Family Medicine is uniquely positioned to anchor life-course, people-centred care at the front line while simultaneously strengthening the primary-secondary interface at CHC, FRU, SDH, and DH levels. The evidence now available from policy, standards, and Indian practice indicates that Family Medicine expansion should no longer be treated as optional. It should be treated as a time-bound implementation priority for health-system strengthening. Without a robust cadre of trained family physicians, Ayushman Arogya Mandirs and district-system reforms risk being impressive in physical scale but fragmented in clinical function. With such a cadre, India can improve continuity, rational referrals, team performance, local problem-solving, and access to comprehensive care closer to home [1-6].
Ethics approval
Ethics approval and consent to participate: Not applicable. This manuscript is a narrative review and policy analysis based on publicly available documents and published research.
Consent for Publication
Not applicable.
Availability of data and materials
No new dataset was generated. All evidence is drawn from public policy documents, public dashboards, and published literature.
Funding
No specific funding was used for this manuscript.
Competing Interests
None declared.
AI-use Declaration
Generative AI was used to support literature discovery, source organisation, synthesis, and language drafting for this manuscript. All final decisions regarding source selection, factual verification against original documents, interpretation, recommendations, and manuscript approval remain the responsibility of the human authors.
References
- Ministry of Health and Family Welfare, Government of India. National Health Policy 2017. New Delhi: MoHFW; 2017. [Google Scholar]
- Ministry of Health and Family Welfare, Government of India. Indian Public Health Standards 2022: Community Health Centre. New Delhi: MoHFW; 2022. [Google Scholar]
- Ministry of Health and Family Welfare, Government of India. Ayushman Arogya Mandir official portal and live report card. New Delhi: MoHFW; accessed 2026 Jun 4. [Google Scholar]
- World Health Organisation. Primary health care. Geneva: WHO; 2025. [Google Scholar]
- Gupta A, Kumar R, Prasad R, Abraham S, Nedungalaparambil NM, Krueger P, et al. The landscape of family medicine in India – A cross-sectional survey study. PLOS Glob Public Health. 2025;5(1):e0004107. [doi:10.1371/journal.pgph.0004107]
- Gupta A, Prasad R, Abraham S, Nedungalaparambil NM, Bhattacharyya O, Landes M, et al. The emergence of family medicine in India – A qualitative descriptive study. PLOS Glob Public Health. 2023;3(5):e0001848. [Google Scholar]
- Kumar R. National Medical Commission Act 2019: white paper on accelerated implementation of family medicine training programs towards strengthening of primary healthcare in India. J Family Med Prim Care. 2020;9(1):1-6. [doi:10.4103/jfmpc.jfmpc_942_19]
- Rahman SMF, Angeline RP, David KV, Christopher P. Role of family medicine education in India’s step toward universal health coverage. J Family Med Prim Care. 2014;3(3):180-182. [doi:10.4103/2249-4863.141594]
- Roshni M., MD, Family Medicine – Calicut experience: history is made here. J Family Med Prim Care. 2016;5(2):238-241. [doi:10.4103/2249-4863.192370]
- Velavan J. “The refer less resolve more” initiative: a five-year experience from CMC Vellore, India. J Family Med Prim Care. 2012;1(1):3-6. [doi:10.4103/2249-4863.94439]
- National Board of Examinations in Medical Sciences. NBEMS Accredited Seats. New Delhi: NBEMS; accessed 2026 Jun 4. [Google Scholar]
- National Health Authority. Ayushman Bharat Digital Mission: official website. New Delhi: NHA; accessed 2026 Jun 4. [Google Scholar]

Published
Article metrics
- Views
- 131
- Downloads
- 69
Based on this site's usage statistics.
Issue
Section
How to Cite
License
Copyright (c) 2026 Suneela Garg, K Madan Gopal, Arjun Kumar Harda Jakasania, Subodh Gupta, Aditi Aikat, Mohan Kubendra

This work is licensed under a Creative Commons Attribution 4.0 International License.
More in this topic: Health workforce
Short Review · 2024
The Growing Burden: Workload on Community Health Officers