Original Article Vol. 5 No. 2 (2021): International J Health Systems and Implementation Research
Health Care Seeking Behaviour and Utilization of Health Services by Kalingalinga Compound Residents aged between 16years and 60 years in Lusaka City, Zambia
Health Care Seeking and Utilisation by Kalingalinga Residents
Downloads
Topics
Keywords:
- Healthcare Seeking Behaviour; Healthcare Utilisation; Health workers
Abstract
Health seeking behaviour encompasses activities undertaken to maintain good health, to prevent ill health, as well as dealing with any departure from a good state of health. This study set out to better understand the health seeking behaviour and utilization of health services of the residents in Kalingalinga Compound of Lusaka. The study was guided by the Social cognitive theory. The Social Cognitive Theory (SCT) started as the Social Learning Theory (SLT) in the 1960s by Albert Bandura. This study employed a cross-sectional design and identified the socio-demographic and health service-based factors that influence HSB among the residents of study area. Convenience sampling method was used to pick the required sample. 160 subjects were requested to participate in this survey. Interview guides and questionnaires were used to obtain the data from the participants. The quantitative data was coded and analysed using the latest SPSS version for descriptive statistics. Descriptive statistics including frequencies and percentages were used for data analysis. Pearson’s correlation was computed to find the relationships between different variables. In addition, probability plot was done to show and predict the factors which highly contribute to health seeking behaviour. Thematic Analysis was done for qualitative data. This study established that some respondents' characteristics such as level, household size, occupation and monthly income significantly affected the health seeking behaviour among some Kalingalinga residents. Providing good services, affordability of such services and proximity were considered the most important service characteristics associated with the seeking health seeking behaviour in both public and private healthcare facilities. Study recommends actions to improve the access to healthcare services and quality of care at the health facilities, improve the availability of medicines in public clinics. It is hoped that the introduction of National Health Insurance Scheme in Zambia will provide financial protection for households with lower socioeconomic status in order to encourage use of appropriate healthcare sources during illness episodes.
Full text
This web version was prepared from the published PDF, which is the version of record. Please cite and quote from the PDF.
Introduction
Health seeking behaviour encompasses activities undertaken to maintain good health, to prevent ill health, as well as dealing with any departure from a good state of health. In this paper, healthcare seeking behaviour is defined as consulting a qualified medical professional or seeking healthcare at a health facility such as private clinics, public health centres, and faith based facility during illness episodes or any situation requiring medical attention. Utilisation of health services is a measure of the relationship between service capacity and service output. The service capacity is usually defined as the need of the total population in the catchment area. Health service coverage can be defined as a concept expressing the extent of interaction between the service (provided by the health facility) and the people for whom it is intended (in this case those in Kalingalinga Compound).
Expanded access to healthcare is now well-recognised as critical to achieving better health outcomes and economic development [1]. Health services in Zambia are provided by three main players, namely the government, the church missionaries (or faith based facilities) and private-for-profit providers. Public health facilities are the main choice of healthcare for the majority of Zambians. Several national surveys show that over 80% of individuals who sought formal healthcare after falling ill had visited a public health facility [2].
The Government of Zambia abolished user fees on outpatient primary healthcare services, firstly in 2006 in rural areas, and extended the policy to urban areas in 2012. The goal of this policy was to increase utilisation and access to health services in both rural and urban primary healthcare facilities [2]. Zambia has currently introduced National Health Insurance Scheme as one of the health financing strategies, to assist in ensuring a sustainable, predictable and dedicated financing for the health sector whilst at the same time provide financial risk protection for those who may not manage to pay. Quality of care is a high priority of the Zambian Ministry of Health, as can be concluded from the mission statement as to provide all Zambians with equity of access to cost-effective quality health care as close to the family as possible [3]. The Government of Zambia under the Ministry of Health has increased the number of health facilities throughout the country in recent years. However, there are still disparities in certain communities in accessing health services.
Kalingalinga Compound is a low-income, high-density settlement east of the city of Lusaka District. It has an estimated population of between 45,000 to 50, 000 [4]. There has been a lot of infrastructure development and many students studying at the University of Zambia and CHRESO University rent houses from there as Boarding houses. It has a government health facility known as Kalingalinga Clinic, one Private clinic (Comfort Medical Care) and one faith based health facility run by the Roman Catholics known as Our Lady’s Hospice. Residents in this compound access any of these facilities when they feel unwell.
Strategic policy formation in all health care systems should be based on information relating to health promoting, seeking and utilization behaviour and the factors determining these behaviours. This high use is attributed mostly to issues of acceptability such as easy access, shorter waiting time, longer or flexible opening hours, better availability of staff and drugs, better attitude and more confidentiality in socially stigmatized diseases. Also whether medicine is provided by the health care facility or has to be bought from the chemists has an effect.
Studies have attempted to describe factors that significantly affect health seeking behaviour during illness episodes [5]. A variety of factors have been identified as the leading causes of poor utilization of primary health care services: including poor socio-economic status, lack of physical accessibility, cultural beliefs and perceptions, low literacy level of the mothers and large family size [6]. The factors can be classified as cultural beliefs, socio-demographic status, women’s autonomy, economic conditions, physical and financial accessibility, and disease pattern and health service issues [7, 8].
A key determinant for health seeking behaviour is the organisation of the health care system [8]. In many health systems, particularly in developing countries such as Uganda, illiteracy, and poverty, under funding of the health sector, inadequate water and poor sanitation facilities have a big impact on health indicators [9]. A comprehensive health care system has to focus on people who are the poorest. A more coordinated effort in designing behavioural health promotion campaigns through inter-sectoral collaboration must focusing more on disadvantaged segments of the population (that is, women, children and elderly would be step towards improvement).
Statement of the Problem
The under-utilization of the health services in public sector has been almost a universal phenomenon in developing countries [10]. In Zambia, the public health sector by and large has been underused due to insufficient focus on prevention and promotion of health. Despite a notable increase in utilisation of public health services following the removal of user fees and now the introduction of National Health Insurance Scheme still a number of people do not access health facilities. Some people are reported to die in homes and bodies taken to the mortuaries as Bought in Dead (BID). For example, some evidence has shown that the impact of user fees on removing barriers to access, on healthcare utilisation, and on illness related healthcare spending among households, remain unclear [11]. Furthermore, studies have shown that even when user fees have been abolished, individuals and households still incur costs when they visit health facilities [12]. Therefore, this study sought to assess the health care seeking behaviour and utilization of health services in Kalingalinga Compound in Lusaka and identify the socio-demographic and health service-based factors that influence HSB among the residents of Kalingalinga Compound.
Purpose of the study
This study set out to better understand the health seeking behaviour and utilization of health services of the residents in Kalingalinga Compound of Lusaka.
Research Objectives
From the purpose of the study, the following specific objectives are framed to answer the above purpose, namely:-
- To assess the health seeking behaviour and utilization of health services among the residents in Kalingalinga Compound.
- To investigate the factors affecting the health seeking behaviour and utilization of health services of the residents of the study area.
- To come up with measures of increasing health seeking behaviour and utilization of services by the residents of the study area.
Theoretical underpinning and selected literature
The study was guided by the Social cognitive theory. The Social Cognitive Theory (SCT) started as the Social Learning Theory (SLT) in the 1960s by Albert Bandura. It developed into the SCT in 1986 and posits that learning occurs in a social context with a dynamic and reciprocal interaction of the person, environment, and behavior. The unique feature of SCT is the emphasis on social influence and its emphasis on external and internal social reinforcement. SCT considers the unique way in which individuals acquire and maintain behavior, while also considering the social environment in which individuals perform the behavior. The theory takes into account a person's past experiences, which factor into whether behavioural action will occur. These past experiences influences reinforcements, expectations, and expectancies, all of which shape whether a person will engage in a specific behavior and the reasons why a person engages in that behavior. Many theories of behavior used in health promotion do not consider maintenance of behavior, but rather focus on initiating behavior. This is unfortunate as maintenance of behavior, and not just initiation of behavior, is the true goal in public health. The goal of SCT is to explain how people regulate their behavior through control and reinforcement to achieve goal-directed behavior that can be maintained over time. The first five constructs were developed as part of the SLT; the construct of self-efficacy was added when the theory evolved into SCT [13].
A study by Kuuire et al. as cited in [14] showed that patients in Ghana who are poor were less likely to seek health care. Several other contemporary studies [15]; [16] and [17] on health care seeking behaviours have been conducted in Zimbabwe. These studies have reported that religion, distance to health care facility, health care worker attitudes towards patients and work, the availability and affordability of medication, patients’ knowledge about their conditions were associated with delays in seeking health care services. Similarly, this study equally investigated the factors affecting the health seeking behaviour and utilization of health services of the residents of Kalingalinga Compound. However, unlike the aforementioned studies, this study will come up with measures of increasing health seeking behaviour and utilization of services by the residents of Kalingalinga Compound.
Good health care seeking behaviour practices among Kalingalinga residents could potentially reduce the morbidity and mortality rates. Additionally, public health interventions need to be informed by the health care seeking behaviour among patients. However, there are no studies which have determined health care seeking behaviours among Kalingalinga residents according to the researchers knowledge and the local literature reviewed. Therefore the main objective of this study was to better understand the health seeking behaviour and utilization of health services of the residents in Kalingalinga Compound of Lusaka.
According to WHO, health seeking behaviour is part of a wider concept, health behaviour [18]. While little has been written specifically on health behaviour in relation to Kalingalinga residents, there is an extensive literature on health behaviour in general. When people wish to seek help, they may choose to do so from a wide range of available service providers. In most countries, there is often a mixed economy of care patients who choose between private and public, or more often in developing countries between private and public allopathic care, traditional healers and pharmacists.
The tendency of patients to shop around for care is another issue that is only poorly understood. There is some anecdotal information about this but very little has been published on the subject. In many developing countries only a minority of patients go to health facilities, and those that do have frequently consulted other practitioners previously. A large number of patients are thought to consult pharmacists when they have symptoms of ailments obtaining over-the-counter antibiotics. In Kinshasa, Zaire, 57% of 1200 respondents participating in a survey had signs and symptoms suggestive of ailments in the previous year, but only 32% had visited an official health care facility. In contrast, in the UK 92% of 104 residents reported that they would visit a nearest clinic if they thought they had an illness, and only 1 of 193 women reported using non-prescribed antibiotics. A population study in Zimbabwe of knowledge of and attitudes to antimicrobial agents suggested considerable self-medication with antibiotics when any disease was suspected. Respondents reported sharing antibiotics with friends [19].
Evidences show that socio-economic status, geographic settings, cultural issues, service quality, health system policy and procedures are among the factors affecting health-seeking behavior of the community [19]. Individuals who fail to get health information found to have lower health seeking behavior. However, individuals having higher health seeking behavior could better prevent disease and promote health. Healthcare-seeking behavior is a multifaceted effect and needs an appropriate investigation in order to provide knowledge that may help with the formulation of health care policies and programs. Thus, this study was done to assess the health seeking behaviour and utilization of health services among the residents in Kalingalinga Compound. The study investigated the factors affecting the health seeking behaviour and utilization of health services of the residents of Kalingalinga Compound.
Many evidences suggest that addressing health seeking behavior pave ways for appropriate utilization of health care services. A study by Ayanto tried to measure health-seeking behavior in multidimensional approaches to improve specific health behavior change to prevent disease and promote health [19]. Ayanto’s study showed that majority (85.4%) of 257 participants had low level of health-seeking behaviour [19]. The extent of health-seeking behavior of this study was remarkably low when compared to different parts of the world. This finding was consistent with findings reported for mothers’ health care seeking behavior for child health illness in Dera district, North Shewa zone in Oromiya regional state of Ethiopia. In any case, this finding implies that significant behavioural interventions are needed to improve health-seeking behavior so that increase health service utilization coverage in the community. About 93.6% participants in Ayanto’s study took actions and seek medical help when got ill, which is more than reported in South Africa, 76.5% [20]. Data from Ayanto’s study further showed that 40.3% of participants primarily chose private clinics when they seek medical help. This study sought to establish if this is also the case in Kalingalinga compound.
Methodology
This study employed a cross-sectional design to assess the health care seeking behaviour and utilization of health services in Kalingalinga Compound in Lusaka and identify the socio-demographic and health service-based factors that influence HSB among the residents of Kalingalinga Compound. This study was conducted from 29th March to 9th April 2021. Study approval was sought from relevant authorities within the health sector. This study encompassed indigenous male and female residents aged between 16 years and 60 years of Kalingalinga Compound as well as some health personnel at the selected health center. According to Zambia Statistical Agency, the median age of people in Zambia is 17.6 years. The distribution of age group is 0-14 years (45.74% children), 15-24 years (20.03% early working age), 25-54 years (28.96% prime working age), 55-64 years (3.01% mature working age), 65 years and over (2.27% elderly). Participation was eligible to grownups that are able to read and write in English, Nyanja and Bemba and have given their written informed consent. People below 16 years old, and those who disagreed to participate in this study were excluded. As of 2013, the study area comprised 25,000 to 30,000 residents; a very poor area, it borders the wealthier townships of Mtendere and Kabulonga and many of its occupants are poor people who were discouraged from settling in Lusaka and moved as squatters to outlying regions of the city. Currently, the population of Kalingalinga approximately stands at 39139 residents.
Convenience sampling method was used to pick the required sample from the residents of Kalingalinga compound. The aforementioned sampling method aims to obtain information from participants who are easily accessible to the researcher. The sample size was considered based on the confidence level of 95% and 5% of margin error. By using the common design effect of 2, the required sample size was 150. Additional 10 % was added to the sample in case of missing and dropping of data, resulting in a total of 155 subjects. For the purpose of the study, 160 subjects were requested to participate in this survey.
Interview guides and questionnaires were used to obtain the data from the participants. The questions were developed based on the previous literature. The questionnaire consisted of three parts mainly to evaluate the health seeking behaviour and utilization of health services in Lusaka city. The first part obtained the demographic data of the participants, including age, gender, ethnicity, education level, monthly income and the presence of chronic diseases. The second part evaluated the medicine taking behavior among the respondents. The third part focused on seeking medical attention at a clinic or hospital. The questionnaire was translated into Bemba and Nyanja by a qualified linguistic translator to make it easy for the participants to answer. Thereafter, the questionnaire was piloted to 10 subjects to ensure the clarity of the questions.
A self-administered questionnaire and semi-structured interview was used to obtain the data from all participants in this survey. The researchers explained the aim of the study prior to data collection and signed consent form was obtained from all participants before involving them in the survey. Household areas were targeted in this survey. The researchers hoped that the majority of the participants responded at the same time of distributing the questionnaires, while some of them responded later and handed the questionnaires back to the researchers in the following days. The questionnaire was completed within 10-15 minutes. The respondents were given sufficient time to complete the questionnaires before they were collected. The interviews were equally done within 15 minutes.
The quantitative data was coded and analysed using the latest SPSS version for descriptive statistics. Descriptive statistics including frequencies and percentages were used for data analysis. Pearson’s correlation was computed to find the relationships between different variables. In addition, probability plot was done to show and predict the factors which highly contribute to medicine seeking behaviour. The p-value of <0.05 with a confidence level of 95% was considered.
Thematic Analysis was used to analyse qualitative data. Thematic Analysis is a method for identifying, analyzing and reporting patterns within data [26]. The researcher opted to use thematic analysis because it provided a highly flexible approach that can be modified for the needs of many studies, providing a rich and detailed, yet complex account of data [24]. Firstly, qualitative data from semi-structured interviews were transliterated from audio recordings into text. The researchers further read and familiarized with the data, having ideas about what is in the data and what is interesting about them. Initial codes were then generated deductively based on the pilot study, prior research, and theoretical framework. Codes were first fit into a pre-existing coding framework to provide detailed analysis of aspects of the data the researcher that is most interested in exploring. The researcher then sorted and collated all the potentially relevant coded data extracts into themes.
Findings
Of 114 participants, 58% were females (Table1). Eighty two percent had sought some medical attention when they were unwell (Table 2). Seventy six percent had sought the care from public facility ( Table 3).
| Frequency | Percent | Valid Percent | Cumulative Percent | ||
|---|---|---|---|---|---|
| Valid | Male | 48 | 42.1 | 42.1 | 42.1 |
| Female | 66 | 57.9 | 57.9 | 100.0 | |
| Total | 114 | 100.0 | 100.0 | ||
| Frequency | Percent | Valid Percent | Cumulative Percent | ||
|---|---|---|---|---|---|
| Valid | Yes | 93 | 81.6 | 81.6 | 81.6 |
| No | 15 | 13.2 | 13.2 | 94.7 | |
| 4.00 | 6 | 5.3 | 5.3 | 100.0 | |
| Total | 114 | 100.0 | 100.0 | ||
Source: Field data, 2021
| Frequency | Percent | Valid Percent | Cumulative Percent | ||
|---|---|---|---|---|---|
| Valid | Public | 87 | 76.3 | 76.3 | 76.3 |
| Private | 27 | 23.7 | 23.7 | 100.0 | |
| Total | 114 | 100.0 | 100.0 | ||
Source: Field data, 2021
The participants cited numerous reasons with regards to why they opt to go public clinics. One of the participants reported that “public clinics are cheaper as compared to private clinics”.
Similarly, another participant echoed that “the services in public clinics are good, affordable and some are free”. Contrarily, some participants indicated that they don’t go public clinics because “some public health personnel are rude, sarcastic and they don’t give proper attention to patients”. Affordability of services in public clinics was the important reason for selecting health provider among respondents who completed only basic education. On the contrary, affordability was the second least popular reason for selecting health provider among respondents who completed tertiary education. 65% of the respondents cited proximity as their reason for selecting public healthcare provider while 11% of the respondents cited politeness of health provider as the main reason for their choice of healthcare provider.
Respondents who had sought healthcare at private clinics or hospitals were asked to state reasons for selecting the health provider. With regards to the most important service factor affecting respondents' choice of healthcare provider, the majority of respondents cited good services provided by the provider as the most important reason for their patronage of such provider. This was followed by proximity, prompt attention and readily available drugs. Politeness and courtesy among health workers was least considered a factor in selecting healthcare provider.
| Frequency | Percent | Valid Percent | Cumulative Percent | ||
|---|---|---|---|---|---|
| Valid | Yes | 63 | 55.3 | 55.3 | 55.3 |
| No | 51 | 44.7 | 44.7 | 100.0 | |
| Total | 114 | 100.0 | 100.0 | ||
Source: Field data, 2021
As regards satisfaction with the services received, 55.3% (63) indicated that they were satisfied with the services received. 44.7% indicated that they were not satisfied with the services they received at the clinics or hospitals (Table 4).
| Frequency | Percent | Valid Percent | Cumulative Percent | ||
|---|---|---|---|---|---|
| Valid | Yes | 63 | 55.3 | 55.3 | 55.3 |
| No | 51 | 44.7 | 44.7 | 44.7.7 | |
| Total | 114 | 100.0 | 100.0 | ||
Source: Field data, 2021
The majority of study participants (55.3%) indicated that they treated their health problems based on the physician’s advice. 47.7% of the respondents indicated that they did not treat their health problems based on the physician’s advice (Table 5).
| Frequency | Percent | Valid Percent | Cumulative Percent | ||
|---|---|---|---|---|---|
| Valid | Yes | 42 | 36.8 | 36.8 | 36.8 |
| No | 69 | 60.5 | 60.5 | 97.4 | |
| 3.00 | 3 | 2.6 | 2.6 | 100.0 | |
| Total | 114 | 100.0 | 100.0 | ||
Source: Field data, 2021
36.8%% of the respondents indicated that they treated their health problems based on past experience with similar illness. However, the majority of respondents (60.5%) indicated that they did not treat their health problems based on past experience with similar illness (Table 6).
| Frequency | Percent | Valid Percent | Cumulative Percent | ||
|---|---|---|---|---|---|
| Valid | Yes | 27 | 23.7 | 23.7 | 23.7 |
| No | 84 | 73.7 | 73.7 | 97.4 | |
| 3.00 | 3 | 2.6 | 2.6 | 100.0 | |
| Total | 114 | 100.0 | 100.0 | ||
Source: Field data, 2021
Table 7 is indicative of the fact that in 73.7% of the cases, treatment of current illness was not based on the advice of the relatives, friends and media. Nonetheless, 23.7% indicated that they treated their health problems based on the advice they received from relatives, friends and media.
| Frequency | Percent | Valid Percent | Cumulative Percent | ||
|---|---|---|---|---|---|
| Valid | Once | 39 | 34.2 | 34.2 | 34.2 |
| Twice | 18 | 15.8 | 15.8 | 50.0 | |
| Three | 12 | 10.5 | 10.5 | 60.5 | |
| More than three times | 27 | 23.7 | 23.7 | 84.2 | |
| None | 15 | 13.2 | 13.2 | 97.4 | |
| 11.00 | 3 | 2.6 | 2.6 | 100.0 | |
| Total | 114 | 100.0 | 100.0 | ||
Source: Field data, 2021
When asked to state how many times they self-medicated in the last three months, 34.2% of the respondents indicated that they self-medicated once, 15.8% indicated once, 10.5% indicated thrice, 23.7% indicated more than three times and 13.2% indicated that they never self-medicated. These statistics are clearly indicative of the fact that the majority of respondents self-medicated at least once in the last three (3) months (Table 8).
A Pearson’s correlation was further done to establish if there is a significant correlation between the monthly income and choice of healthcare provider. This was guided by both the null and alternative hypotheses which were stated as follows:
H0 – There is a significant correlation between the monthly income and choice of healthcare provider.
H1 – There is no significant correlation between the monthly income and choice of healthcare provider.
Interpretation of results: Since the calculated r value of 0.049 is less than the critical value of 0.05 at the chosen level of significance, the null hypothesis will be accepted while the alternative hypothesis will be rejected (Table 9).
| Monthly income | Public or Public | ||
|---|---|---|---|
| Monthly income | Pearson Correlation | 1 | .049 |
| Sig. (2-tailed) | .606 | ||
| N | 114 | 114 | |
| Public or Public | Pearson Correlation | .049 | 1 |
| Sig. (2-tailed) | .606 | ||
| N | 114 | 114 | |
*. Correlation is significant at the 0.05 level (2-tailed). Source: Field data, 2021
There is a positive and significant correlation between the monthly income and choice of healthcare provider.
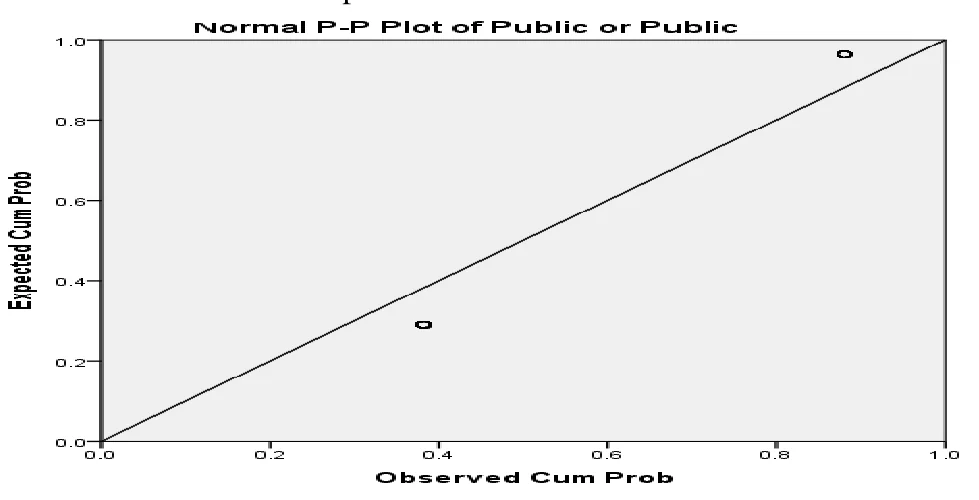
The results of the Pearson’s correlation were supported by the P-P plot (probability–probability plot) which equally showed that there is a close relationship between the monthly income and choice of healthcare provider. The P-P plot is tabularised in the figure below:
Another Pearson’s correlation was done to establish if there is a significant correlation between the level of education and seeking medical attention. This was guided by both the null and alternative hypotheses which were stated as follows:
H0 – There is a significant correlation between the level of education and seeking medical attention.
H1 – There is no significant correlation between the level of education and seeking medical attention.
| Educational level | Seek medical attention | ||
|---|---|---|---|
| Educational level | Pearson Correlation | 1 | -.221* |
| Sig. (2-tailed) | .018 | ||
| N | 114 | 114 | |
| Seek medical attention | Pearson Correlation | -.221* | 1 |
| Sig. (2-tailed) | .018 | ||
| N | 114 | 114 | |
*. Correlation is significant at the 0.05 level (2-tailed). Source: Field data, 2021
Interpretation of results: Since the calculated r value of 0.018 is less than the critical value of 0.05 at the chosen level of significance, the null hypothesis will be accepted while the alternative hypothesis will be rejected ( Table10).
There is a positive and significant correlation between the level of education and seeking medical attention.
Discussion
Health care Utilisation requires gaining entry into the health-care system, getting access to sites of care where patients can receive needed services, and finding providers who meet the needs of patients and with whom patients can develop a relationship based on mutual communication and trust [21]. Health care providers note that timely access to health care is important inasmuch as it might enable patients and physicians to prevent illness, control acute episodes, or manage chronic conditions, any of which could avoid exacerbation or complication of health conditions [22]. In these times of COVID–19, early utilisation of health services can help reduce fatalities. This study set out to better understand the health seeking behaviour and utilization of health services of the residents in Kalingalinga Compound of Lusaka. People use health-care services to diagnose, cure, or ameliorate disease or injury; to improve or maintain function; or to obtain information about their health status and prognosis. The respondents in this study reported that they normally seek medical attention from private or public health care institutions. This is in line with Onwujekwe who reported that most people seek medical attention either in private or public clinics [23]. The majority of respondents in these studies used the hospital or clinic as the first source of treatment. In general, the majority of the respondents believed that provision of good services was the most important reason for their choice of health provider.
Health-care utilization is determined by the need for care, by whether people know that they need care, by whether they want to obtain care, and by whether care can be accessed. The need for health-care services to improve or maintain health are major determinants of health-care utilization. Many factors affect health-care utilization independently of need and are reflected in differences, some of which are remediable, among population groups. The study reports affordability of services as the most important factor. This concurs with other Nigerian studies investigating factors influential to choice of provider among out of pocket. For example, Omotoso discovered that people with relatively lower incomes consider affordability as most important alongwith the closeness to their residence (proximity) [24]. This study further revealed that the likelihood of seeking appropriate healthcare was significantly influenced by income and the level of education. This further affirms that underutilization of private health services especially by the poor and disadvantaged remains a problem in some residential areas in Lusaka even though there is a huge unmet need for health care.
Unlike in some previous studies, women in this study were found to be as likely to have appropriate health seeking behaviour as men. This is in agreement with Omotoso who found out that women overall have higher health-care utilization than men [24]. This may indicate that females are aware of the importance of appropriate treatment service and its sources. One possible explanation for this could be that they have enough access to information due to their constant exposure to sources of information from relatives, physicians and social media. They also have enough information from friends that enables them to make decisions regarding health seeking healthcare in time of sickness and do not totally depend on the physician’s advice.
Health-care utilization can be appropriate or inappropriate, of high or low quality, and of high or low cost. In this study, inappropriate health-seeking behaviour was observed among participants from larger family sizes and with low level of education. This might be due to the fact that those who had larger family members bared more family responsibilities and experienced severe socioeconomic hardships, which prevented them from visiting appropriate private and public healthcare facilities. This finding corresponds with the findings done in Rwanda by Manzi in 2014 [25]. During the Covid – 19 period, this study found that some residents from Kalingalinga avoided going to the public clinics which were mostly crowded fearing to contract COVID–19 virus. This accounted for 34.2% who preferred to self – medication.
A key determinant for health seeking behaviour is the organisation of the health care system. Many patients’ desire is that when they go the health facility, they need to be attended to early. In this study, looking at the factors that affected access to health facilities, many respondants suggested that affordability of the services is the greatest measure especially among the poor while for the rich, they cited quick service as the best measure. In this case, the study proposes that a health facility should charge economical rates and there must be enough health workers at each point to attend to patients. Some of the points of reference are; reception, nurses’ desk, consultation, laboratory and pharmacy.
Apart from the above, the study also found out that many respondents cited that in public health facilities, patients are just given prescription to go buy medicine as compared to private clinics. This discourages many patients to seek health services having in mind that they will not get the medicine. In order to overcome this, health facilities should have enough and necessary medicine to give to clients. Proximity was also a measure that came out in the study. Participants proposed that it is important that health facilities are close to the people. Some people from the East part of Kalingalinga felt that the clinic is far away from their residences. This was why they opted going to the Hospice and other private clinics which were nearby. Ministry of Health need to increase the number of health facilities throughout the country.
The last but not least measure proposed by respondents is good communication by the health care providers. Respondents sated that most health care providers form public health centres do not treat patients well. The language used is rough with no empathy. It might be important that health care providers are trained in communication skills so as to help attend to patients with empathy.
Conclusion
Data related to all research questions were collected using the questionnaires and the interview guides. This study established that some respondents' characteristics such as level, household size, occupation and monthly income were significantly affected the health seeking behaviour among some Kalingalinga residents. Providing good services, affordability of such services and proximity were considered the most important service characteristics in seeking health seeking behaviour in both public and private healthcare facilities. Thus, policy formulation and implementation by public and private health care providers should be directed towards improving access to healthcare services. This can be achieved by increasing the number of health facilities in Kalingalinga compound. The quality of care provided at health facilities also requires attention as mentoring, supportive supervision and other measures could be embarked upon in order improve quality of care and health service provision. Issues relating to affordability of such health services can be addressed by lowering the cost that is attached to certain services. Lowering the cost of certain services can significantly enhance accessibility. Indisputably, affordability of such services and proximity can increase health care seeking behaviour and utilization of health services.
The study recommends that policy formulation and implementation should be directed towards improving access to healthcare services. The quality of care provided at health facilities also requires attention. Issues concerning availability of medicines in public clinics need to be addressed. It is hoped that the introduction of National Health Insurance Scheme in Zambia will provide financial protection for households with lower socioeconomic status in order to encourage use of appropriate healthcare sources during illness episodes.
References
- WHO. (2010) Health systems financing: the path to universal coverage. World Health Report. Geneva: WHO. [Google Scholar]
- Masiye, F, Chitah BM, McIntyre, D. (2010). From targeted exemptions to user fee abolition: Experience from rural Zambia. Soc Sci Med; 71:735-750. [Google Scholar]
- MoH (1992). National Health Policies and Strategies (Health Reforms), October 1992. [Google Scholar]
- World Health Organization. (2000). World Health report 2000. Health systems: improving performance. Geneva. [Google Scholar]
- LCC. (2018). Lusaka City State of Environment Outlook Report. Lusaka City Council, Lusaka. [Google Scholar]
- Katung, P.Y. (2001). Socio-economic factors responsible for poor utilization of PHC services in rural community in Nigeria. Niger J Med; 10: 28–29. [Google Scholar]
- Nyamongo, I. K. (2002). Health care switching behaviour of malaria patients in a Kenyan rural community. Soc Sci Med; 54: 377–386. [doi:10.1016/s0277-9536(01)00036-3]
- Ahmed, S.M, Adams, A.M. Chowdhury, M. Bhuiya, A. (2003). Changing health seeking behavior in Matlab: do development interventions matter? Health Policy Plan 2003; 18: 306–315. [Google Scholar]
- Ukwaja, K.N, Alobu, I, Nweke C.O, Onyenwe, E.C. (2013). Healthcare-seeking behaviour, treatment delays and its determinants among pulmonary tuberculosis patients in rural Nigeria: a cross-sectional study. BMC health services research; 13(1):25. [Google Scholar]
- Gotsadze, G. Bennett, S. Ranson, K. Gzirishvili, D. (2005). Health care-seeking behaviour and out-of-pocket payments in Tbilisi, Georgia. Health policy and planning; 20(4):232–242. [doi:10.1093/heapol/czi029]
- Shaikh, B.T and Hatcher, J. (2005). Health seeking behaviour and health service utilization in Pakistan: challenging the policy makers. J Public Health (oxf); 1:49–54. [doi:10.1093/pubmed/fdh207]
- Wayne, L.M. (2019). Behavioural Change Models: The Social Cognitive Theory. Boston: Boston University School of Public Health. [Google Scholar]
- Masiiwa A, et al. (2016). The health care seeking behaviours of patients diagnosed with oral and maxillofacial tumours. Harare.62 (9–12):71–7. [Google Scholar]
- Marume A, et al. (2018). Social capital, health-seeking behavior and quality of life among refugees in Zimbabwe: a cross-sectional study. Int J Migr Health Soc Care. 2018; 14 (4):377–86. [doi:10.1108/ijmhsc-04-2017-0017]
- Chadoka, M. (2017). Maternal health-seeking behaviour and under-five mortality in Zimbabwe. J Biosoc Sci. 2017; 49 (3):408–21. [Google Scholar]
- Ayanto, S. (2018). Health-seeking behavior and associated factors among community in Southern Ethiopia: Community based cross-sectional study guided by Health belief model. Hosanna: Hosanna College of Health Sciences. [Google Scholar]
- USAID (2010). Evaluation of Africa’s health in 2010. [Google Scholar]
- AHRQ (Agency for Healthcare Research and Quality). (2009) National Healthcare Quality and Disparities Reports. Rockville, MD: AHRQ. [doi:10.4135/9781412971942.n14]
- National Center for Health Statistics (NCHS). (2016) With chartbook on long-term trends in health. Hyattsville (MD): National Center for Health Statistics (US); 2017b. Health, United States. [Google Scholar]
- Onwujekwe, O. Onoka, C. Uzochukwu, B. Hanson, K. (2011). Constraints to universal coverage: inequities in health service use and expenditures for different health conditions and providers. International journal for equity in health; 10(1):50. [doi:10.1186/1475-9276-10-50]
- Omotoso, D. (2010). Health seeking behaviour among the rural dwellers in Ekiti State, Nigeria. African Research Review. 4 (2). [doi:10.4314/afrrev.v4i2.58296]
- Manzi, A. (2014). Assessing predictors of delayed antenatal care visits in Rwanda: a secondary analysis of Rwanda demographic and health survey. BMC pregnancy and childbirth. 2014; 14 (1):290. [doi:10.1186/1471-2393-14-290]
- Braun, V. & Clarke, V. (2006). Using thematic analysis in psychology. Qualitative Research in Psychology, 3, 77-101. [doi:10.1191/1478088706qp063oa]

Published
Article metrics
- Views
- 968
- Downloads
- 741
Based on this site's usage statistics.