Original Article Vol. 4 No. 2 (2020): International J Health Systems and Implementation Research
Geospatial Clustering of Stillbirth Incidence in Chandigarh – North India
Stillbirth Geospatial Clustering in India
Downloads
Topics
Keywords:
- GIS
- geospatial
- stillbirth
Abstract
Introduction: Stillbirth is a highly sensitive indicator of antenatal care. It reflects the strength of public health and primary health care in a country. Globally, India leads in terms of stillbirth burden; while it lags in achieving perinatal mortality goals. However, very less research has been done on stillbirths in the country. India aims to reduce the stillbirth rate to single digit from the current rate of 23 per 1000 live births by 2025. To achieve this, understanding stillbirth epidemiology in the country is imperative. In this paper, we discuss the social risk factors for stillbirth, especially - place of residence, with the help of geospatial mapping. Methods: We analysed the place of occurrence of stillbirth in Chandigarh Union Territory (UT) from 1st July 2013 to 30th June 2014 using QGIS Mapping. Data on stillbirth were collected from various health institutions and community health workers of Chandigarh, for the reference period. Results: A total of 259 stillbirths were recorded in this period, with the stillbirth rate of 16 per 1000 live births. From the slum areas of Chandigarh UT 69% of stillbirths were reported, whereas only 31% occurred in the other sectors of Chandigarh UT. Nearly half of the stillbirths occurred in the top 5 slums of Chandigarh. Top three slums of stillbirth occurrence located in the eastern part of Chandigarh. Conclusion: Socio-economic status plays a major role in stillbirth occurrence. Both long-term and short-term public health policies should be adopted by identifying these areas in every town or district.
Full text
This web version was prepared from the published PDF, which is the version of record. Please cite and quote from the PDF.
Introduction
Every year, about 2.65 million pregnancies result in stillbirths, globally [1]. Unfortunately, about 98% of third-trimester stillbirths occur in low- and middle-income countries such as India [1]. However, 90% of the stillbirth research is conducted in the developed world, while only 10% of it is conducted in the developing and underdeveloped world [1–3]. Hence, better information on the extent of stillbirths from low- and middle-income countries such as India are required for better planning of prevention programmes [1, 2, 4].
At present India is the topmost global contributor of stillbirth in absolute numbers [4, 5]. Stillbirths constitute a major part of perinatal deaths, yet remain largely invisible [6, 7]. India has bee unable to make progress towards the set targets in reducing the perinatal morality in the past [6, 7]. Unfortunately, in India, research is giving less importance to this important issue. This may be because, research on stillbirth needs a wide range of population-based coverage, robust methodology, more commitment and support of local government authorities to conduct the study [8]. At present, in India, any research related stillbirth is considered important for the National Health Programmes and the Indian public health system. We conducted a study on stillbirths in a northern part of India and aimed to discuss the relationship between place of residence of mother and stillbirth occurrence.
Methods
This study was conducted in Chandigarh, a Union Territory (UT) located in northern India. Chandigarh has a population of 10,55,450, as per 2011 census. The study was conducted from 1st July 2013 to 30st June 2014. Data regarding stillbirths with the residential address of Chandigarh were collected from the records maintained at medical colleges, hospitals, Birth and Death Registration Department, civil dispensaries and registers maintained by Auxiliary Nurses Midwives (ANMs) independently. Duplicates were removed and a final list was prepared. As per the World Health Organization (WHO) stillbirth is defined as, “late foetal death >=28 completed weeks of gestation”, which is an internationally accepted definition for epidemiological studies [4]. Here, foetal length and weight are not taken into consideration as it is not feasible at middle- and low- income country setting [4, 5, 9]. The study was approved by the Institute Ethics and Research Board. Four field staff were recruited and trained to carry out the study. Data entry and analysis: Data were entered in Microsoft Office Excel sheet and analysed using SPSS Version 22. QGIS Version 2.18.16 was used to represent the stillbirth mapping of Chandigarh [10, 11].
Results
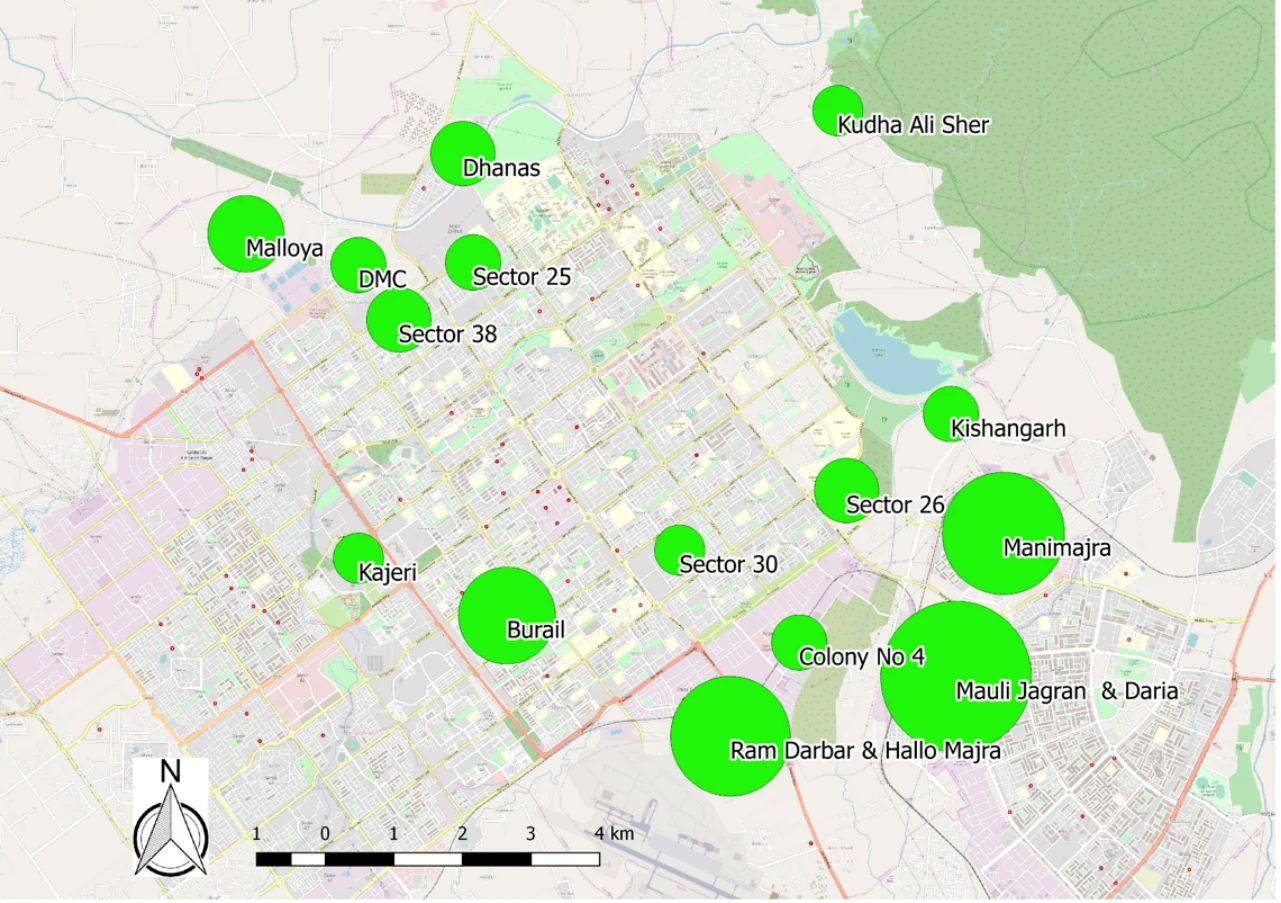
The main finding in our study was that 69% of the stillbirths occurred in the periphery and inner slum areas of Chandigarh UT and 46% of the stillbirths occurred in the top 5 slums or unorganized sectors of Chandigarh UT. The top 3 slums of stillbirth occurrence are located in the eastern part of the UT. Figure 1 shows QGIS mapping of stillbirth occurrence and the top 15 places of stillbirth occurrence is shown in Table 1. During the study period of one year, 259 stillbirths were recorded from Chandigarh UT. Estimated stillbirth rate in Chandigarh UT was 16 per 1000 livebirths.
| S. No | Area | N=259 n(%) |
|---|---|---|
| 1 | Mauli Jagran & Daria | 38(15) |
| 2 | Mani Majra | 26(10) |
| 3 | Ram Dharbar & Hallo Majra | 25(10) |
| 4 | Burail | 17(07) |
| 5 | Malloya | 11(04) |
| 6 | Sector 26 | 8(03) |
| 7 | Sector 38 | 8(03) |
| 8 | Dhanas | 8(03) |
| 9 | Sector 25 | 6(02) |
| 10 | Colony Number 4 | 6(02) |
| 11 | Dadu Majra Colony | 6(02) |
| 12 | Kishangarh | 6(02) |
| 13 | Sector 30 | 5(02) |
| 14 | Kajeri | 5(02) |
| 15 | Kudha Ali Sher | 5(02) |
| Total of 15 areas | 180(69) | |
| Other areas | 79(31) | |
| Total Stillbirths | 259 |
Discussion
To the best of our knowledge, this is the first study from India that represents the stillbirth mapping using QGIS mapping to depict ‘where stillbirths are occurring’ and stresses upon the importance of socio-economic conditions to prevent stillbirth. Main finding in our study was that nearly 70% of stillbirths occurred in the slums/unorganized sectors of Chandigarh, and among these nearly half occurred in the first three slums/unorganized sectors of Chandigarh. Chandigarh is a well-planned city designed by a French architect in 1966, which spreads around114 square kilometres [12]. At the time of planning, historical villages were left without disturbing their existing village structure, whereas rest of the area were divided into sectors, with proper roads, green parks, cycle paths and shopping complexes [12, 13]. Over the years, due to the strict adherence of town planning rules by the administration, most of the planned areas were undisturbed by the unauthorized buildings and encroachments, whereas the villages located within and in the periphery of Chandigarh slowly turned into slums. Migration from other states is considered as one of the main reason for this transformation [13]. In our study, almost all the stillbirth cases occurred in the periphery of Chandigarh — Burail and Kajeri slums, and sector numbers 25, 26, 30 and 38. Burail and Kajeri are historical villages of Chandigarh UT. Parts of few sectors also (sector 25, 26, 30 and 38) slowly turned into slums. Sector 25, 26 and 38 thus have an extension with slum areas. Even though government data from the year 1998 suggests 13 slums in Chandigarh, Rao et al have identified 17 main slums and 44 sub-slums in and around Chandigarh [13]. Although stillbirth is associated with many maternal and foetal factors, our study shows the importance of place of residence of women. Nearly 70% of the cases occurred only in these 15 slums/unorganized sectors, whereas only 30% of the cases occurred in rest of the sectors. In our case control analysis of this data which is published elsewhere, place of residence was not a significant factor because we selected both cases and controls from the same locality [8]. Hence, in this paper we are reporting place of residence as a descriptive. A survey covering 9 states of India, revealed that rural residence, female illiteracy, low socio economic status, lower caste, minority religion and the women not having paid employment, are factors associated with stillbirth [14]. A study from Nepal also revealed that rural residence and illiteracy are risk factors for stillbirth [15]. Another study from Iran has shown that a better place of residence plays a positive role in preventing stillbirths [16]. Studies from Australia and Norway revealed that the risk of stillbirth is more among migrants, especially when the years since migration are less [17, 18]. We estimated the stillbirth rate as 16 per 1000 livebirths. Government reports however show lower estimates (sample registration system (SRS) – 5 per 1000 live births in 2013); on the other hand independent global estimates of stillbirth in India were around 23 per 1000 live births [5, 19]. Also, a wide range of variation in stillbirth rate (12.5 to 26.48) has been reported across various states of India [20–24].
India has already missed the Millennium Developmental Goal (MDG) perinatal and neonatal mortality reduction targets of 2015 [6, 7]. As a positive move, an understanding the burden of stillbirths, India has taken many steps in the recent years. In the recent National Health Policy 2017, India has set a target of reducing the stillbirth rate from the present 23 per 1000 live births to single digit (<10 per 1000) by the year 2025 [7]. In this light, India also launched the ‘India Newborn Action Plan (INAP)’ to achieve the set targets [6, 25]. On the research front, to achieve the above targets, we need to have a multi-level surveillance system and further evidence, such as government-based surveillance systems and independent surveillance systems to support public health. Another notable move by Indian government is identifying fifty surveillance sites all over India and releasing a common guideline for stillbirth surveillance for India [26], though the output and publications are awaited.
This study is an important study from public health point of view. It stresses on following public health interventions in order to prevent stillbirths. First, as a long-term policy change, area of residence plays a very important role in stillbirth occurrence. By improving the socio-economic conditions of people, maternal and child health will be improved. Second, these identified high-risk areas could be managed with targeted interventions to prevent stillbirths.
Limitations
Our study has the following few limitations. First, we were not able to calculate the stillbirth rate for each slum, as their population are not readily available. This would have given us additional valuable information, adding strength to our study. Second, QGIS mapping could be further improved if we could collect the exact GIS coordinates (Global Information System) at house-hold level. These limitations will be overcome in the future stillbirth studies. Nevertheless, stillbirth is an important, independent, and highly sensitive indicator of maternal health care. More studies like this will unveil the risk factors and their management with regards to this important indicator. Existing policies should be implemented actively and newer policies should be brought in so that we are able to achieve the target of single digit stillbirth by 2025.
Conclusion
Nearly 70% of the stillbirths occur in the slum areas of Chandigarh. Public health system should concentrate on these hotspots to bring down stillbirth rates to single digit.
References
- Frøen JF, Gordijn SJ, Abdel-Aleem H et al. (2009) Making stillbirths count, making numbers talk - Issues in data collection for stillbirths. BMC Pregnancy and Childbirth 9 (1): 58. doi: https://doi.org/10.1186/1471-2393-9-58.
- Doyal L (2004) Gender and the 10/90 gap in health research. Bulletin of the World Health Organization 82 (3): 162. [Google Scholar]
- Aminu M, Unkels R, Mdegela M et al. (2014) Causes of and factors associated with stillbirth in low- and middle-income countries: a systematic literature review. BJOG : an international journal of obstetrics and gynaecology 121 Suppl 4 141–53. doi: https://doi.org/10.1111/1471-0528.12995.
- Lawn JE, Blencowe H, Pattinson R et al. (2011) Stillbirths: Where? When? Why? How to make the data count? Lancet (London, England) 377 (9775): 1448–63. doi: https://doi.org/10.1016/S0140-6736(10)62187-3.
- Blencowe H, Cousens S, Jassir FB et al. (2016) National, regional, and worldwide estimates of stillbirth rates in 2015, with trends from 2000: a systematic analysis. The Lancet Global health 4 (2): e98–e108. doi: https://doi.org/10.1016/S2214-109X(15)00275-2.
- Ministry of Helath and Family Welfare G of I (2014) India Newborn Action Plan. http://www.newbornwhocc.org/INAP_Final.pdf. (2014)Accessed: September 2019.
- Ministry of Helath and Family Welfare - Government of India (2018) National Health Policy 2017. https://mohfw.gov.in/sites/default/files/9147562941489753121.pdf. (2018)Accessed: December 2019.
- Newtonraj A, Kaur M, Gupta M, Kumar R (2017) Level, causes, and risk factors of stillbirth: a population-based case control study from Chandigarh, India. BMC pregnancy and childbirth 17 (1): 371. doi: https://doi.org/10.1186/s12884-017-1557-4.
- Lawn JE, Blencowe H, Waiswa P et al. (2016) Stillbirths: Rates, risk factors, and acceleration towards 2030. The Lancet 387 (10018): 587–603. doi: https://doi.org/10.1016/S0140-6736(15)00837-5.
- QGIS Group (2019) QGIS - The Leading Opensource Desktop GIS. https://qgis.org/en/site/. (2019)Accessed: August 2019.
- IBM corporation (1989) IBM SPSS Statistics, India. https://www.ibm.com/in-en/analytics/spss-statistics-software. (1989)Accessed: October 2019.
- Chandigarh Administration Chandigarh - the city beatiful. http://chandigarh.gov.in/knowchd_general.htm. Accessed: April 2020.
- Rao BT, Thakur JS (2007) Vulnerability assessment in slums of union territory, Chandigarh. Indian Journal of Community Medicine 32 (3): 189. [doi:10.4103/0970-0218.36824]
- Altijani N, Carson C, Choudhury SS et al. (2018) No Title. 8 (11): e022583. doi: https://doi.org/10.1136/bmjopen-2018-022583.
- Bhusal M, Gautam N, Lim A, Tongkumchum P (2019) Factors Associated With Stillbirth Among Pregnant Women in Nepal. Journal of preventive medicine and public health = Yebang Uihakhoe chi 52 (3): 154–160. doi: https://doi.org/10.3961/jpmph.18.270.
- Tesema GA, Gezie LD, Nigatu SG (2020) Trends of stillbirth among reproductive-age women in Ethiopia based on Ethiopian demographic and health surveys: a multivariate decomposition analysis. BMC pregnancy and childbirth 20 (1): 193. doi: https://doi.org/10.1186/s12884-020-02880-5.
- Mozooni M, Preen DB, Pennell CE (2020) The influence of acculturation on the risk of stillbirth in migrant women residing in Western Australia. PloS one 15 (4): e0231106. doi: https://doi.org/10.1371/journal.pone.0231106.
- Vik ES, Aasheim V, Schytt E et al. (2019) Stillbirth in relation to maternal country of birth and other migration related factors: a population-based study in Norway. BMC pregnancy and childbirth 19 (1): 5. doi: https://doi.org/10.1186/s12884-018-2140-3.
- Office of the Registrar General and Census Commissioner I SRS Statistical Report 2017. http://www.censusindia.gov.in/vital_statistics/SRS_Reports_2017.html. Accessed: September 2019.
- Doke PP, Karantaki MV, Deshpande SR (2012) Adverse pregnancy outcomes in rural Maharashtra, India (2008-09): a retrospective cohort study. BMC public health 12 (1): 543. doi: https://doi.org/10.1186/1471-2458-12-543.
- More NS, Bapat U, Das S et al. (2012) Community mobilization in Mumbai slums to improve perinatal care and outcomes: a cluster randomized controlled trial. PLoS medicine 9 (7): e1001257. doi: https://doi.org/10.1371/journal.pmed.1001257.
- Mony PK, Varghese B, Thomas T (2015) Estimation of perinatal mortality rate for institutional births in Rajasthan state, India, using capture-recapture technique. BMJ open 5 (3): e005966. doi: https://doi.org/10.1136/bmjopen-2014-005966.
- Kochar PS, Dandona R, Kumar GA, Dandona L (2014) Population-based estimates of still birth, induced abortion and miscarriage in the Indian state of Bihar. BMC pregnancy and childbirth 14 (1): 413. doi: https://doi.org/10.1186/s12884-014-0413-z.
- Bapat U, Alcock G, More NS et al. (2012) Stillbirths and newborn deaths in slum settlements in Mumbai, India: a prospective verbal autopsy study. BMC pregnancy and childbirth 12 (1): 39. doi: https://doi.org/10.1186/1471-2393-12-39.
- Mason E, McDougall L, Lawn JE et al. (2014) From evidence to action to deliver a healthy start for the next generation. Lancet (London, England) 384 (9941): 455–67. doi: https://doi.org/10.1016/S0140-6736(14)60750-9.
- Ministry of Health and Family Welfare - Government of India Operational Guidelines for Establishing Sentinel Stillbirth Surveillance System. https://www.nhm.gov.in/images/pdf/programmes/RBSK/Operational_Guidelines/Operational_Guidelines_for_establishing_Sentinel_Stillbirth_Surveillance_System.pdf. Accessed: December 2019.

Published
Article metrics
- Views
- 1,152
- Downloads
- 800
Based on this site's usage statistics.