Original Article Vol. 9 No. 1 (2025): International Journal of Health Systems and Implementation Research
Magnitude of Anaemia and Micro-nutritional Deficiencies (Iron, Folate, and Vitamin B12) among Outpatient Clinic Patients at a Rural Village-level Health Post in Haryana: An Exploratory Study
Micro-nutritional Deficiencies at a Health Post in Haryana
Downloads
Topics
Keywords:
- Anaemia, Micronutrient deficiencies, Outpatients, Rural health post
Abstract
Background: Anaemia is a significant public health challenge globally. In India, the prevalence rates exceed 50% among women of reproductive age and children. Objective: This cross-sectional study aimed to estimate the prevalence of anaemia and associated nutritional deficiencies (iron, folate, and vitamin B12) among individuals attending an outpatient clinic in Kheri, Haryana. Methods: A total of 90 participants aged above nine years were enrolled, and blood samples were analyzed for haemoglobin levels and relevant nutritional biomarkers. Results: The prevalence of anaemia was 72.2%, with higher rates observed among females (77%) compared to males (50%); 51% of participants had vitamin B12 deficiency, 36% had folate deficiency, and 24% had ferritin deficiency. Among anaemic individuals, 74% had coexisting deficiencies in one or more nutrients. Logistic regression analysis revealed significant associations between anaemia and ferritin deficiency (adjusted OR: 11.22, p < 0.05) and a protective effect of vitamin B12 sufficiency. Additionally, dietary patterns such as high tea consumption with meals and limited intake of fruits and green leafy vegetables contributed to poor nutritional status. Conclusion: These findings underscore the need for targeted interventions to address nutritional deficiencies, particularly vitamin B12 and folate, alongside iron supplementation to reduce the prevalence of anaemia. Comprehensive public health strategies emphasizing dietary education and enhanced access to nutritional supplements are essential to mitigate the burden of anaemia and its broader health implications.
Full text
This web version was prepared from the published PDF, which is the version of record. Please cite and quote from the PDF.
Introduction
Anaemia is a major public health problem prevalent globally in both developing and developed countries. It is a condition characterized by either a lower red blood cell (RBC) count or decreased haemoglobin concentration [1]. Anaemia can cause a variety of symptoms such as fatigue, weakness, dizziness, cold skin and feet, palpitations, heart failure, pulmonary oedema, and depression, and it also affects the cognitive and physical development of children [2]. In children, it impacts physical and cognitive growth, leads to various infections, and delays the onset of menarche. It also harms pregnancy outcomes, increased risk of morbidity, and decreased employment productivity, raising both health and financial issues. A study carried out in Northeast India found that anaemia can lead to preterm deliveries, with infants born at a low birth weight [3]. Although anaemia can strike anyone at any age, gender, or place of residence, several studies have shown that women of reproductive age, pregnant women, and small children are particularly vulnerable to anaemia [4,5].
According to WHO estimates, 40% of children below 5 years of age, 37% of pregnant women, and 30% of women of reproductive age are anaemic worldwide [1]. In 2019, 50 million years of healthy lives were lost due to disability resulting from anaemia [1]. In India, the prevalence of anaemia is even higher: 53% of women of reproductive age and children under the age of 5 (WHO 2019 estimates) are anaemic. Various studies have been conducted across different regions of the country to find the prevalence of anaemia. One study, conducted in 16 districts across 11 states, found that 85% of pregnant women were anaemic, including 13% who were severely anaemic. Among adolescent girls, 90% were anaemic, with 7% classified as severely anaemic [6]. In Uttar Pradesh, 36% of mothers aged 18-49 years and 56% of children under the age of 5 years were found anaemic [7]. A study conducted in the southern part of India reported that 30% of women were anaemic and 48% were iron deficient [8]. Another study was conducted in Bihar among adolescent girls, where it was found that 50% of girls were anaemic, out of which 43.3% were mild, 3.3% were moderate, and 3.3% were severe anaemic [9]. There are various causes of anaemia, such as nutritional deficiencies (iron and vitamin deficiencies), and most of these are either due to poor dietary intake, poor absorption of diet or inadequate education related to diet. The predominant deficiencies in nutritional deficiencies are of iron, vitamin B12, and folate levels [10]. A study conducted to find the determinants of anaemia highlighted that ferritin is the strongest predictor of haemoglobin. It is also seen that iron deficiency anaemia in pregnancy leads to poor mental development in the child, which could be avoided by proper supplementation [11]. A study found that maternal vitamin B12 deficiency, insufficiency and impaired vitamin B12 status predicted a two-fold increase in the risk of neonatal vitamin B12 deficiency at birth [12]. Further research has shown that an imbalance in the maternal micronutrients with an increasing ratio of folate to vitamin B12 was associated with an increase in plasma homocysteine, lowering of neonatal birth weight, birth length, head circumference and chest circumference [13]. In addition to nutritional deficiencies, other causes of anaemia include infections, inflammation, haemoglobinopathies, chronic disease and gynaecological and obstetric conditions [14]. In nutritional deficiency, in Southeast Asia, Iron Deficiency Anaemia was found in 50% or more of pregnant women, while folic acid deficiency may range from 30 to 50% [15]. A systematic review revealed that the prevalence of iron deficiency, vitamin B12 deficiency, and folate deficiency is 54%, 53%, and 37%, respectively. Iron deficiency was highest among pregnant women [16]. A study conducted in Hyderabad among urban elderly found that 20% of the enrolled people were anaemic and 5.45%, 9.1% and 42.3% were anaemic due to deficiencies of iron, folate and vitamin B12, respectively [17]. Another study done in Southern India reported that 63.2% of women and 40.8% of neonates had vitamin B12 deficiency [12]. It was observed that vitamin B12 levels were higher in women than in men and higher among vegetarians. [18]. An interesting observation was found in children aged 6-18 years living in high-altitude regions of India: a low prevalence of vitamin B12 and folate deficiencies was found among them. A recent study published in 2023 observed that the prevalence of B12 and FA deficiency was higher among adolescents (31.0% and 35.6%, respectively) compared to school-age children (17.3% and 27.6%) and preschool children (13.8% and 22.8%). The prevalence of both B12 and FA deficiencies was significantly higher by 8% and 5%, respectively, in adolescent boys compared to girls [19].
In our recent study, we compared different methods of haemoglobin estimation [20]. This study was done with the objective to correlate the prevalence of anaemia with the types of nutritional deficiencies (ferritin, vitamin B-12 and folate) among the anaemic population residing at the health post in Kheri.
Methodology
Study Area
This cross-sectional study was conducted at the health post, Kheri, which is a field practice area of the Department of Community Medicine and School of Public Health, PGIMER, Chandigarh. It caters services to two villages – Kheri and Badona Kalan, situated in the district of Panchkula, Haryana, India.
Study Population
All individuals who came to the clinic above 9 years of age during the study period and provided informed consent to participate were considered.
Sample Size and Sample Strategy
By considering anaemia prevalence 60% and precision 10%, the sample size came out to be 90. This study included 90 participants visiting the outpatient department from May 2021 to July 2021.
Data collection tools.
Initially, participants were provided information about the study in their local language (Hindi/Punjabi). Those who gave informed consent and volunteered to participate in the study were enrolled. A semi-structured questionnaire was used to collect information related to socio-demographic characteristics, dietary habits, medical history, symptoms of anaemia, and menstruation details (from females only) from the participants. The questionnaire was filled by the investigator by asking verbally from the participants. After that, blood samples were collected from the willing participants.
Sample collection and processing
Firstly, a 4 ml blood sample was drawn from the antecubital vein via syringe, and 2 ml of that blood was transferred into a vacutainer containing an anticoagulant (EDTA), from which haemoglobin concentration was measured using the direct cyanmethemoglobin method. The haemoglobin estimation was performed at the laboratory of the health post, Kheri, and quality control was ensured by the Public Health Laboratory, PGIMER, Chandigarh.
Equation 1: Calculation for Haemoglobin Value
Calculation of haemoglobin value (g/dl) = (O.D. of the test / O.D. of the standard) × Conc. of the standard solution
The remaining 2 ml of the blood sample was transferred to a plain vacutainer (without anticoagulant). This sample was left in the vacutainer to form a clot, which was then centrifuged for serum separation. The serum was stored at -20ºC for further investigation of serum ferritin, vitamin B12 and folate levels. The serum was sent to the Department of Biochemistry for estimating serum ferritin, vitamin B12 and folate levels using the Cobas 6000, which is based on the principle of electrochemiluminescence (ECL).
Ethical consideration:
Ethical clearance was taken from the Intramural Ethics Committee of the Post Graduate Institute of Medical Education and Research (PGIMER), Chandigarh, vide letter no. NK/7130/MPH/233 dated May 15, 2021. The purpose of the study was to explain to all the participants or to their parents if the age of the participant was below 18 years.
Results
The study was conducted among 90 participants attending the OPD at the Health post, Kheri, during the period from May to July 2021. In our study population, 82 percent of the participants were females. 70 percent were married; the majority were Hindus, living in joint families. Two-thirds of the participants were unemployed, and three-fourths belonged to the middle socio-economic status (Table 1). The mean (SD) age of the participants was 43.77 (18.26) years. One-third of the study population were in the age group of 31-50, and 40 percent of the participants were above 50 years of age.
| Variables | n (%) |
|---|---|
| Age | 43.77±18.26 |
| Age Group | |
| Less than 30 years | 23 (25.6) |
| 31 to 50 years | 31 (34.44) |
| More than 50 years | 36 (40) |
| Gender | |
| Male | 16 (17.7) |
| Female | 74 (82.3) |
| Marital status | |
| Married | 63 (70.0) |
| Unmarried | 12 (13.3) |
| Widow | 15 (16.7) |
| Caste | |
| General | 38 (42.2) |
| OBC | 22 (24.54) |
| SC/ST | 30 (33.3) |
| Religion | |
| Hindu | 84 (93.4) |
| Muslim | 4 (4.4) |
| Sikh | 2 (2.2) |
| Educational Qualifications | |
| No formal education | 10 (11.1) |
| Primary Education | 30 (33.3) |
| Senior secondary | 21 (23.3) |
| Graduate or Postgraduate | 29 (32.3) |
| Employment status | |
| Employed | 18 (20.0) |
| Unemployed | 61 (67.7) |
| Student | 11 (12.2) |
| Type of family | |
| Nuclear | 28 (31.2) |
| Joint | 62 (68.8) |
| Socio-economic status | |
| Low | 20 (22.3) |
| Middle | 67 (74.4) |
| High | 3 (3.3) |
Most of the study population were vegetarian (86 percent), with 73 percent reporting the consumption of green leafy vegetables twice a week and 67% reporting daily milk consumption. One-third of participants consumed tea thrice daily. Nearly half of the study population reported consuming tea/milk with/after meals. Only 22 percent reported regular fresh fruit consumption. (Table 2).
| Variables | n (%) |
|---|---|
| Type of diet | |
| Vegetarian | 77 (85.5) |
| Non-Vegetarian | 8 (9) |
| Vegetarian with eggs | 5 (5.5) |
| Eating frequency | |
| 2 times a day | 15 (16.7) |
| 3 times a day | 75 (83.3) |
| Daily tea Intake | |
| Very Rare | 8 (8.8) |
| Once a day | 15 (16.6) |
| Twice a day | 37 (41.2) |
| Thrice/More frequently | 30 (33.4) |
| Tea/ Milk Consumption within half an hour of taking meals | |
| Yes | 46 (51.2) |
| No | 44 (48.8) |
| Jaggery Consumption | |
| Daily | 10 (11.2) |
| Two times a week | 15 (16.6) |
| Weekly | 12 (13.3) |
| Very Rare | 53 (58.8) |
| Fresh fruits Consumption | |
| Daily | 20 (22.2) |
| Two times a week | 26 (28.8) |
| Weekly | 25 (27.8) |
| Rarely | 19 (21.2) |
| Green leafy vegetables consumption | |
| Daily | 13 (14.4) |
| Two times a week | 66 (73.4) |
| Weekly | 9 (10) |
| Rarely | 2 (2.2) |
| Milk consumption | |
| Daily | 60 (66.7) |
| Two times a week | 3 (3.3) |
| Weekly | 5 (5.6) |
| Rarely | 22 (24.4) |
| Junk food consumption | |
| Two times a week | 24 (26.7) |
| Weekly | 2 (2.2) |
| Rarely | 64 (71.1) |
A history of iron supplementation (within the last 3 months) and Albendazole use (last 6 months) was reported by 13 percent of the study participants, the majority of whom were under 30 years of age (Table 3).
| Variables | Age Group | Total (N=90) | ||
|---|---|---|---|---|
| <30 years (N=23) | 31-50 years (N=31) | >50 years (N=36) | ||
| History of any chronic medical illness | 0 (0) | 14 (45.16) | 29 (80.5) | 43 (48) |
| History of taking any Medication | 5 (21.7) | 13 (41.9) | 28 (77.8) | 46 (51) |
| History of taking Iron supplement (within last 3 months) | 10 (43.5) | 1 (3.2) | 1 (2.7) | 12 (13.3) |
| History of taking Albendazole (last 6 months) | 8 (34.7) | 1 (3.2) | 3 (8.3) | 12 (13.3) |
| History of COVID- 19 Infection | 0 (0) | 0 (0) | 1 (2.7) | 1 (1.1) |
| History of COVID-19 vaccination | 3 (13.1) | 18 (58.1) | 29 (81) | 50 (55.5) |
| History of Blood loss from rectum due to piles etc. | 0 (0) | 3 (9.6) | 0 (0) | 3 (3.3) |
When asked about signs and symptoms, most participants across all age groups reported fatigue. The second most reported symptom was craving non-food substances (Pica) like chalk, soil, etc., in the age group less than 30 years, while swelling of the lower limbs was reported in the age group of 31-50 years old, and shortness of breath among the participants aged more than 50 years. (Table 4).
| Symptoms | Age Group | Total (N=90) | ||
|---|---|---|---|---|
| <30 years (N=23) | 31-50 years (N=31) | >50 years (N=36) | ||
| Fatigue | 15 (65.2) | 23 (74.2) | 32 (88.8) | 70 (77.7) |
| Craving to eat soil | 6 (26) | 4 (12.9) | 0 (0) | 10 (11.1) |
| Do not able to tolerate cold temperature | 0 (0) | 0 (0) | 1 (2.7) | 1 (1.1) |
| Loss of Appetite | 2 (8.7) | 0 (0) | 6 (16.7) | 8 (8.8) |
| Shortness of breath | 2 (8.7) | 5 (16) | 8 (22.2) | 15 (16.6) |
| Hair loss | 2 (8.7) | 4 (13) | 0 (0) | 6 (6.6) |
| Paleness | 2 (8.7) | 0 (0) | 0 (0) | 2 (2.2) |
| Cracks and ulcers in the mouth | 1 (4.3) | 5 (16) | 4 (11.11) | 10 (11.1) |
| Swelling in lower limbs | 2 (8.7) | 10 (32) | 3 (8.33) | 15 (16.6) |
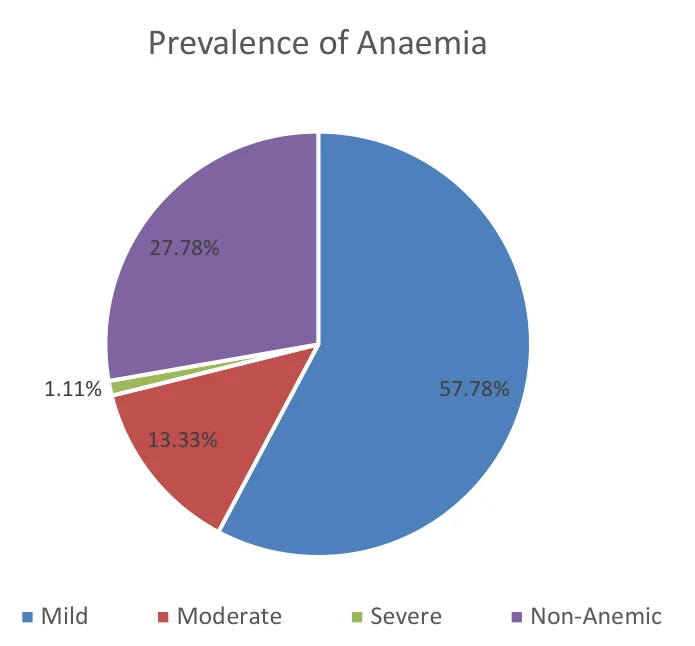
In our study, more than 3/4 of the study population are females, out of whom 88% have children. The majority of the women participant were severely anaemic (Figure 1). Every second participant was B-12 deficient (51%). B-12 deficiency was observed in both anaemic (43%) as well as reported having regular menstruation (Table 5). Using the Direct Cyanmethemoglobin method, the prevalence of anaemia was found to be 72%. There was a higher prevalence observed among the females (77%) than males (50%) (Table 6). The majority were mildly anaemic (58%).
| Variables | n (%) |
|---|---|
| Women having children (N=66) | |
| Yes | 58(87.8) |
| No | 8(12.1) |
| Regular Menstruation (N=40) | |
| Yes | 34(85) |
| No | 6(15) |
| Method for menstrual hygiene management (N=40) | |
| Sanitary Napkins | 36(90) |
| Cloth | 4(10) |
| Age at Menarche (years) (N=73) | 14.14±1.23 |
| Duration of cycle (days) (N=40) | 31.93±6.52 |
| Age at Menopause (years) (N=34) | 45.24±5.06 |
| Frequency of changing sanitary napkins/cloth in a day (N=40) | 2.53±0.75 |
| Anaemic Status | Male | Female | Total |
|---|---|---|---|
| Non-Anaemic | 8 (50) | 17 (22.98) | 25 (27.7) |
| Anaemic | 8 (50) | 57 (77.02) | 65 (72.2) |
| Total | 16 (100) | 74 (100) | 90 (100) |
About 36% of the participants were folate deficient, and 7% were ferritin deficient. Almost 5 percent of the population was deficient in all of three, namely ferritin, folate, and B-12; whereas 23% of the population was free from all the aforementioned three deficiencies (Table 7). Additionally, 7% were found to be deficient in both B-12 and ferritin, and 6% in folate, and ferritin, and all of them were anaemic.
| Anaemic (N=65) n (%) | Non-Anaemic (N=25) n (%) | Prevalence (N=90) n (%) | |
|---|---|---|---|
| Folate deficiency | 9 (13.8) | 3 (12) | 12 (13.3) |
| Ferritin deficiency | 6 (9.2) | 0 (0) | 6 (6.6) |
| B-12 deficiency | 12 (18.5) | 13 (52) | 25 (27.7) |
| Folate & Ferritin deficiency | 5 (7.7) | 0 (0) | 5 (5.5) |
| Ferritin & B-12 deficiency | 6 (9.2) | 0 (0) | 6 (6.6) |
| Folate & B-12 deficiency | 7 (10.78) | 4 (16) | 11 (12.2) |
| Folate, Ferritin & B-12 deficiency | 3 (4.62) | 1 (4) | 4 (4.4) |
| Not deficient in folate, ferritin and B-12 | 17 (26.1) | 4 (16) | 21 (23.3) |
| Total | 65 | 25 | 90 |
The odds of folate deficiency among participants of all ages, who were experiencing fatigue, were 1.38 times higher than among those without fatigue. When categorized into age groups, the odds were highest among participants <30 years old (OR 1.90), followed by those >50 years of age (OR 1.80) and those aged 31-50 years old (OR 1.06); however, none of them were statistically significant. The odds of ferritin deficiency among participants of all ages who were experiencing fatigue were 11% lower than those who were not experiencing fatigue. Similarly, the odds of vitamin B-12 deficiency among participants of all ages, who were experiencing fatigue, were 37% lesser than those who were not experiencing fatigue (Table 8).
| All | <30 years | 31-50 years | >50 years | |
|---|---|---|---|---|
| OR (95%CI) p value | OR (95%CI) p value | OR (95%CI) p value | OR (95%CI) p value | |
| Folate | ||||
| Normal | Reference | |||
| Deficient | 1.38 (0.47-4.06) 0.56 | 1.90 (0.31-11.69) 0.47 | 1.06 (0.16-6.92) 0.95 | 1.80 (0.16-20.14) 0.63 |
| Ferritin | ||||
| Normal | Reference | |||
| Deficient | 0.89 (0.28-2.84) 0.84 | 1.11 (0.18-6.75) 0.90 | 1.31 (0.20-8.45) 0.77 | NA |
| Vitamin B-12 | ||||
| Normal | Reference | |||
| Deficient | 0.63 (0.23-1.74) 0.37 | 1.20 (0.19-7.48) 0.84 | 0.76 (0.14-3.97) 0.75 | 0.26 (0.02-3.00) 0.24 |
The odds of folate deficiency among participants of all ages who were anaemic were 1.24 times higher than among non-anaemic participants; however, the results were not statistically significant (Table IX). The odds of ferritin deficiency among participants of all ages who were anaemic were 10.67 times higher than those who were non-anaemic, and the results were statistically significant. These odds were significant even after adjusting for folate and vitamin B-12 (Table IX). The odds of vitamin B-12 deficiency among participants of all ages who were anaemic were 71% lower than those who were non-anaemic, and the results were also statistically significant. These odds were significant even after adjusting for folate and ferritin (Table 9).
| All | <30 year | 31-50 year | >50 year | |||||
|---|---|---|---|---|---|---|---|---|
| OR (95% CI) p value | aOR (95% CI) p value | OR (95% CI) p value | aOR (95% CI) p value | OR (95% CI) p value | aOR (95% CI) p value | OR (95% CI) p value | aOR (95% CI) p value | |
| Folate | ||||||||
| Normal | Reference | |||||||
| Deficient | 1.24 (0.46-3.33) 0.66 | 1.04 (0.35-3.03) 0.94 | NA | NA | 3.73 (0.35-39.4) 0.24 | 2.61 (0.22-30.9) 0.45 | 0.30 (0.06-1.37) 0.10 | 0.31 (0.07-1.40) 0.12 |
| Ferritin | ||||||||
| Normal | Reference | |||||||
| Deficient | 10.67 (1.22-93.3) 0.007* | 11.22 (1.38-91.1) 0.02* | NA | NA | 4.57 (0.42-48.7) 0.16 | 4.78 (0.41-55.4) 0.21 | NA | NA |
| Vit- B12 | ||||||||
| Normal | Reference | |||||||
| Deficient | 0.29 (0.10-0.83) 0.01* | 0.29 (0.09-0.79) 0.01* | NA | NA | 0.13 (0.02-1.01) 0.02* | 0.13 (0.02-0.85) 0.03* | 0.40 (0.09-1.71) 0.20 | 0.47 (0.11-2.06) 0.31 |
*p-value < 0.05 denotes a significant impact on anemia
Discussion
Anaemia is a major public health problem in both developing and developed countries worldwide. The most prevalent cause of anaemia is iron deficiency, although other potential causes include malaria, parasitic infections, nutritional deficiencies, inflammation, chronic diseases, and haemoglobinopathies [21]. The most efficient technique for detecting anaemia is haemoglobin estimation. In our study, the prevalence of anaemia was found to be 72%; more than three-fourths of the participants are females, out of which 88% had children.
Although nearly 3/4ths of the study population were found to be anaemic, it is seen that only 13% of the population had consumed iron supplements in the past 3 months, indicating poor coverage of iron supplementation. However, it was observed that almost 45% of the population below 30 years had taken iron supplements during that period. (Table 3).
It was observed that nearly half the participants reported consuming tea or milk within half an hour of taking meals (Table 2). This is a major inhibitor of iron absorption from the diet. While almost 80% consumed green leafy vegetables at least twice a week, which may be the reason why ferritin deficiency is seen in only 25% of the study population.
A prospective, longitudinal, cross-sectional, hospital-based study conducted over a period of six months in rural areas of Haryana estimated haemoglobin levels in term pregnant women using antenatal or delivery services. Surprisingly, it reported a very high prevalence of anaemia—98% among the participants. This shows that females are more likely to have anaemia, which is consistent with our findings [22]. In 2019, the global prevalence of anaemia was estimated to be 22.8%; however, WHO reported the prevalence of 29.9% among women (15-49 years old) [23]. In India, NFHS-5 (2019-2021) reported the prevalence of anaemia in women (15-49 years old) and men (15-49 years old) to be 57% and 25%, respectively. Kalaivani K & Ramachandran P did a study to evaluate changes in the prevalence of anaemia across successive rounds of the National Family Health Survey (NFHS 2, 3, and 4). Trend analysis showed that the overall prevalence of anaemia in India increased in NFHS 3 (59%) compared to NFHS 2 (50%) and then declined in NFHS 4 (50%). A similar trend was observed in the state of Haryana, with anaemia prevalence 55% in NFHS 2, 71% in NFHS 3, and 55% in NFHS 4 [24]. A recent meta-analysis showed that the risk of maternal mortality decreases by 20% for every 1 g/dl increase in the haemoglobin concentration. This decline is continuous between Hb levels of 5 and 12 mg/dl, but it is not linear [25].
Micronutrients play a crucial role in the proper growth and development of the human body, especially during childhood and adolescence, and their deficiency adversely affects health, contributing to low productivity and a vicious cycle of malnutrition, underdevelopment, and poverty. Over one-fourth of the world's population suffers from micronutrient deficiencies, making it a significant public health concern. In India, several programmes and initiatives have been implemented to enhance the nutritional status and overall health of the population, yet a significant segment of the population continues to suffer from micronutrient deficiencies.
Hence, in addition to estimating anaemia, we also analysed blood samples for the deficiencies of folate, ferritin, and vitamin B-12 to ascertain the underlying cause of anaemia, as there are studies that support the fact that vitamin or mineral deficiencies do coexist in anaemic patients [26]. Studies have documented that folate, ferritin, and cobalamin deficiencies are among the major causes of nutritional anaemia. However, limited data are available on the prevalence of these deficiencies among adolescents in India. The present study was carried out to assess the magnitude of folate, ferritin, and cobalamin deficiencies.
In our study, among the anaemic population, approximately 74% of participants have a coexisting deficiency in at least one of the three, i.e., folate, ferritin, and vitamin B-12, or a combination thereof. The prevalence of folate, ferritin, and B-12 deficiencies is 36%, 24%, and 51%, respectively. A multicentre cross-sectional study conducted among urban school-going children and adolescents in ten cities of India reported that one or more micronutrient deficiencies are found in almost half of the school-going children in urban areas [27].
Hence, efforts must be made to combat these as a priority. Similarly, a community-based cross-sectional study conducted by Singh S et al. in a rural district of South India found a folate deficiency of 57%, a ferritin deficiency of 46% and a B-12 deficiency of 44% among women of childbearing age [28]. A school-based cross-sectional study conducted among adolescents aged 11 to 18 years in Delhi observed a prevalence of folate deficiency (40%) almost similar to our study (36%) but a high prevalence of ferritin deficiency (60%) as compared to our study (24%) [29]. This could be due to the adolescent population involved in their study. Surprisingly, a cross-sectional study conducted in northern Himalayan states by Bhardwaj A et al. found none of their participants were folate deficient, but 15% were ferritin deficient [30]. Such disparity in the prevalence of other nutritional deficiencies could be due to the differences in the populations studied. Literary evidence reported similar findings. Previous studies have reported an association of ferritin deficiency with fatigue and have suggested that improving ferritin status may decrease fatigue. [31, 32] However, in our study, we could not find any statistically significant association between fatigue and ferritin deficiency. This could be due to the smaller sample size. One of the limitations of our study is its small sample size, which may restrict the generalisability of the findings. The study was carried out to validate point-of-care testing for haemoglobin estimation and to explore these deficiencies. Additionally, while we focused on three key micronutrients (iron, vitamin B12, and folate), there may be other unmeasured deficiencies.
Our study also reported high level of vitamin B12 deficiency. This high prevalence of vitamin B12 deficiency may be because 85% of the study population were vegetarian. Notably, vitamin B12 deficiency was also detected in participants without anaemia, suggesting that vitamin B12 deficiency alone often does not manifest as anaemia. It appears to contribute to anaemia only when it coexists with other nutritional deficiencies. A community-based cross-sectional study in Northern Himalayan states by Bhardwaj A et al. reported vitamin B-12 deficiency among all the study participants [30].
Our study, along with previous literature, reported almost half of study participants as B-12 deficient. It has been suggested that vitamin B12 deficiency may coexist with iron deficiency, and, based on the available evidence – including our study findings – shows that vitamin B12 deficiency contributes significantly to the global burden of anaemia.
Conclusion
There is a high prevalence of anaemia (72.2%) among the study population. Among those who are anaemic, around 74% of participants have a coexisting deficiency in any of the three, i.e., folate, ferritin, and vitamin B-12, or a combination of the three. Around 51% of the study participants are found to be vitamin B-12 deficient, 36% are folate deficient, and 24% are ferritin deficient. Therefore, to reduce the high burden of anaemia, it is important to address vitamin B12 deficiency along with iron and folate deficiencies.
References
- WHO. Prevalence of anaemia in women of reproductive age (aged 15-49) (%) Location type Prevalence of anaemia in women of repro ... The Global Health Observatory. 2023;2023. [Google Scholar]
- H L, K S. Symptomatology of anaemia. Semin Oncol. 2001 Apr;28(2 Suppl 8):7–14. [Google Scholar]
- Bora R, Sable C, Wolfson J, Boro K, Rao R. Prevalence of anaemia in pregnant women and its effect on neonatal outcomes in Northeast India. J Matern Fetal Neonatal Med. 2014;27(9):887–91. [Google Scholar]
- Toteja GS, Singh P, Dhillon BS, Saxena BN, Ahmed FU, Singh RP, et al. Prevalence of anaemia among pregnant women and adolescent girls in 16 districts of India. Food Nutr Bull. 2006;27(4):311–5. [Google Scholar]
- Kumari R, Kumar Bharti R, Singh Kalpana, Sinha Archana, Kumar S, SaRan anand, et al. Prevalence of Iron Deficiency and Iron Deficiency Anaemia in Adolescent Girls in a Tertiary Care Hospital. Journal of Clinical and Diagnostic Research [Internet]. 2017 [cited 2024 Jun 4];11(8):4–06. [doi:10.7860/jcdr/2017/26163.10325]
- Toteja GS, Singh P, Dhillon BS, Saxena BN, Ahmed FU, Singh RP, et al. Prevalence of anaemia among pregnant women and adolescent girls in 16 districts of India. Food Nutr Bull. 2006;27(4):311–5. [Google Scholar]
- Larson LM, Thomas T, Kurpad A V, Martorell R, Hoddinott J, Adebiyi VO, et al. Predictors of anaemia in mothers and children in Uttar Pradesh, India. :1–14. [Google Scholar]
- Finkelstein JL, Kurpad A V., Bose B, Thomas T, Srinivasan K, Duggan C. Anaemia and iron deficiency in pregnancy and adverse perinatal outcomes in Southern India. Eur J Clin Nutr. 2020 Jan 1;74(1):112–25. [Google Scholar]
- Kumari R, Kumar Bharti R, Singh Kalpana, Sinha Archana, Kumar S, Saran anand, et al. Prevalence of Iron Deficiency and Iron Deficiency Anaemia in Adolescent Girls in a Tertiary Care Hospital. Journal of Clinical and Diagnostic Research. 2017;11(8):4–06. [doi:10.7860/jcdr/2017/26163.10325]
- Thomas D, Chandra J, Sharma S, Jain A, Pemde HK. Determinants of Nutritional Anaemia in Adolescents. Indian Pediatr. 2015;867. [Google Scholar]
- Chang S, Zeng L, Brouwer ID, Kok FJ, Yan H. Effect of Iron Deficiency Anaemia in Pregnancy on Child Mental Development in Rural China. Pediatrics. 2013 Mar 1;131(3):e755–63. [Google Scholar]
- Finkelstein JL, Fothergill A, Krisher JT, Thomas T, Kurpad AV, Dwarkanath P. Maternal vitamin B12 deficiency and perinatal outcomes in southern India. PLoS One. 2021 Apr 6;16(4):e0248145. [doi:10.1371/journal.pone.0248145]
- Gadgil M, Joshi K, Pandit A, Otiv S, Joshi R, Brenna JT, et al. Imbalance of folic acid and vitamin B12 is associated with birth outcome: an Indian pregnant women study. European Journal of Clinical Nutrition 2014 68:6. 2014 Jan 22;68(6):726–9. [doi:10.1038/ejcn.2013.289]
- Chaparro CM, Suchdev PS. Anaemia epidemiology, pathophysiology, and etiology in low-and middle-income countries HHS Public Access. 2019;1450(1):15–31. [Google Scholar]
- Seshadri S. Prevalence of micronutrient deficiency, particularly of iron, zinc and folic acid in pregnant women in South East Asia. British Journal of Nutrition. 2001 May;85(S2):S87–92. [doi:10.1079/bjn2000299]
- Venkatesh U, Sharma A, Ananthan VA, Subbiah P, Durga R. Priyadharshini (Vivekanandha Arts And ScieNce College For Women. J Nutr Sci. 2021;10(11). [Google Scholar]
- Vadakattu SS, Ponday LR, Nimmathota A, Nagalla B, Kondru DS, Undrajavarapu P, Banavath BR, Kommula SR, Punjal R, Palla S. Prevalence of nutritional anemia and hyperhomocysteinemia in urban elderly. Indian Journal of Clinical Biochemistry. 2019 Jul 1;34:330-5. [doi:10.1007/s12291-018-0756-8]
- Malik A, Trilok-Kumar G. Status of Vitamin B 12 among Healthy Adult and Elderly Population in India: A Review. J Nutr Sci Vitaminol. 2020;66:361–8. [Google Scholar]
- Shalini T, Pullakhandam R, Ghosh S, Kulkarni B, Rajkumar H, Sachdev HS, Kurpad AV, Reddy GB. Prevalence of vitamin B12 and folate deficiencies in Indian children and adolescents. Nutrients. 2023 Jul 3;15(13):3026. [doi:10.3390/nu15133026]
- Khurana R, Aggarwal AK, Thungapathra M, Sagar V. Comparison of indirect cyanmethaemoglobin method and TrueHb haemometer point of care test with direct cyanmethaemoglobin (gold standard) method for strengthening anaemia detection at primary health care level. J Family Med Prim Care [Internet]. 2024 Jun [cited 2024 Dec 16];13(6):2469. [Google Scholar]
- Anaemia [Internet]. [cited 2024 Aug 5]. Available from: https://www.who.int/health-topics/anaemia#tab=tab_1
- Mangla M, Singla D. Prevalence of anaemia among pregnant women in rural India: a longitudinal observational study. Int J Reprod Contracept Obstet Gynecol. 2016;3500–5. [doi:10.18203/2320-1770.ijrcog20163431]
- Gardner W, Kassebaum N. Global, Regional, and National Prevalence of Anemia and Its Causes in 204 Countries. :1990–2019. [Google Scholar]
- Kalaivani K, Ramachandran P. Time trends in prevalence of anaemia in pregnancy. Indian J Med Res. 2018 Mar 1;147(3):268. [doi:10.4103/ijmr.ijmr_1730_16]
- Stoltzfus RJ. Iron Deficiency: Global Prevalence and Consequences. Food Nutr Bull. 2003 Oct;24(4_suppl2):S99–103. [doi:10.1177/15648265030244s206]
- Bhargava S, Srivastava LM, Manocha A, Kankra M, Rawat S. Micronutrient Deficiencies and Anaemia in Urban India-Do We Need Food Fortification? Indian J Clin Biochem. 2022 Apr 1;37(2):149–58. [Google Scholar]
- Awasthi S, Kumar D, Mahdi AA, Agarwal GG, Pandey AK, Parveen H, et al. Prevalence of specific micronutrient deficiencies in urban school going children and adolescence of India: A multicenter cross-sectional study. PLoS One. 2022;17(5 May):1–15. [doi:10.1371/journal.pone.0267003]
- Singh S, Geddam JJ, Reddy GB, Pallepogula DR, Pant HB, Neogi SB, John N, Kolli SR, Doyle P, Kinra S, Ness A. Folate, vitamin B12, ferritin and haemoglobin levels among women of childbearing age from a rural district in South India. BMC nutrition. 2017 Dec;3:1-9. [doi:10.1186/s40795-017-0173-z]
- Kapil U, Bhadoria A. Prevalence of Folate, Ferritin and Cobalamin Deficiencies amongst Adolescent in India. J Family Med Prim Care. 2014;3(3):247. [doi:10.4103/2249-4863.141619]
- Bhardwaj A, Kumar D, Raina SK, Bansal P, Bhushan S, Chander V. Rapid assessment for coexistence of vitamin B12 and iron deficiency among adolescent males and females in Northern Himalayan state of India. Anemia. 2013;2013(1):959605. [Google Scholar]
- Neidlein S, Wirth R, Pourhassan M. Iron deficiency, fatigue and muscle strength and function in older hospitalized patients. Eur J Clin Nutr. 2021;75:456–63. [Google Scholar]
- Yokoi K, Konomi A. Iron deficiency without anaemia is a potential cause of fatigue: meta-analyses of randomised controlled trials and cross-sectional studies. Br J Nutr. 2017 May;117(10):1422–31. [doi:10.1017/s0007114517001349]

Published
Article metrics
- Views
- 643
- Downloads
- 243
Based on this site's usage statistics.